
Head and neck anatomy
Use anatomy to explain movement, sensation, infection spread and operative risk. Learn where a structure travels, what it supplies and what changes when it is injured; these three questions turn a labelled diagram into clinical understanding.
THE ANATOMY LAB / INTERACTIVE 3DExplore head and neck in 3D↗Quick revision summary
Bones, compartments and useful landmarks
The mandible comprises a body, rami, angles, coronoid processes and condylar processes. The mandibular foramen opens on the medial ramus; its canal contains the inferior alveolar neurovascular bundle. The mental foramen opens onto the lateral body, commonly in the premolar region, but position varies with anatomy and ridge resorption.
Cranial nerves: separate sensation, taste and movement
V1 passes through the superior orbital fissure and V2 through foramen rotundum; both are sensory. V3 passes through foramen ovale and is mixed. Its inferior alveolar branch supplies mandibular teeth and continues as mental and incisive branches; its mylohyoid branch leaves before canal entry.
Apply anatomy to an examination and surgical record
Map a sensory deficit by named territory and compare sides, using a consistent light-touch and other indicated sensory assessment. Record onset, functional effects, pain and change over time. Examine facial movement separately and assess tongue protrusion and lateral movement if indicated.
Common mistake
Do not confuse lingual nerve sensation, chorda tympani taste, facial nerve movement and hypoglossal tongue movement. Their fibres may travel together locally but their functions remain distinct.
Head and neck anatomy
Use anatomy to explain movement, sensation, infection spread and operative risk. Learn where a structure travels, what it supplies and what changes when it is injured; these three questions turn a labelled diagram into clinical understanding.
Bones, compartments and useful landmarks
The mandible comprises a body, rami, angles, coronoid processes and condylar processes. The mandibular foramen opens on the medial ramus; its canal contains the inferior alveolar neurovascular bundle. The mental foramen opens onto the lateral body, commonly in the premolar region, but position varies with anatomy and ridge resorption. A surface estimate cannot establish an individual implant or incision clearance.
The maxilla forms the upper alveolar process and much of the hard palate and surrounds the maxillary sinus. Posterior tooth roots may be close to the sinus floor, making this relationship relevant to extraction and odontogenic sinus disease. The infratemporal fossa lies deep to the ramus and contains pterygoid muscles, V3 branches, the maxillary artery and pterygoid venous plexus. The pterygopalatine fossa is a communicating neurovascular space posterior to the maxilla.
Trigeminal nerve & dental branches
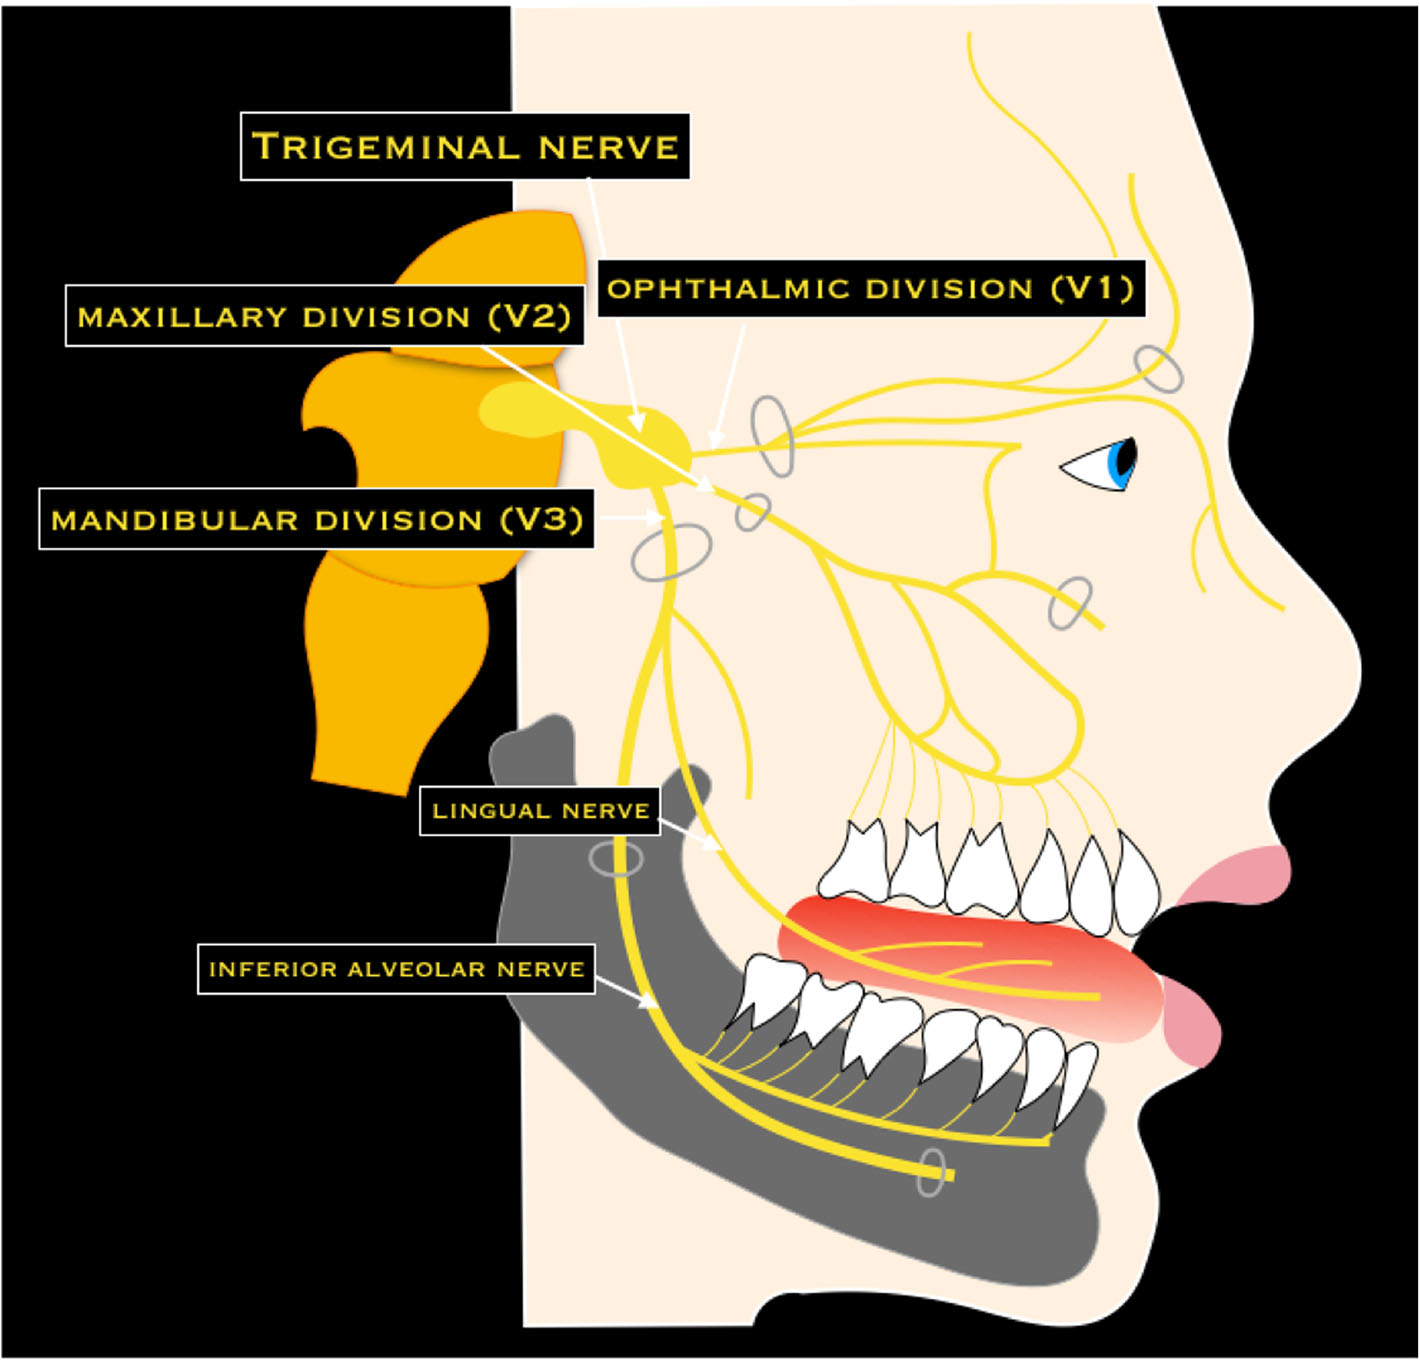
Trace V1, V2 and V3, then the lingual and inferior alveolar nerves. Connect each to the sensory examination after lower third-molar surgery. This is a branch overview, rather than an injection-placement diagram.
Trigeminal nerve & dental branches · Nicola Romano, Margherita Federici and Antonio Castaldi · CC BY 4.0. Original image; displayed at a responsive size. Original publication.
Mastication and the temporomandibular joint
Masseter runs from the zygomatic arch to the lateral ramus and angle and elevates the mandible. Temporalis passes deep to the zygomatic arch onto the coronoid process; it elevates, while posterior fibres assist retrusion. Medial pterygoid attaches to the medial angle and acts with masseter as a muscular sling. Lateral pterygoid attaches to the condylar neck and disc–capsule complex; coordinated activity contributes to protrusion, opening and excursions. All four receive motor supply from V3.
The TMJ is a paired synovial joint with a fibrocartilaginous disc. Opening combines rotation, chiefly in the lower compartment, with translation of the condyle–disc complex, chiefly in the upper compartment. Unilateral muscle activity produces lateral movements; the mandible is not a simple hinge. Restricted opening can arise from muscle, joint, infection or trauma, so local tenderness alone does not identify the mechanism.
Skull base & cranial foramina
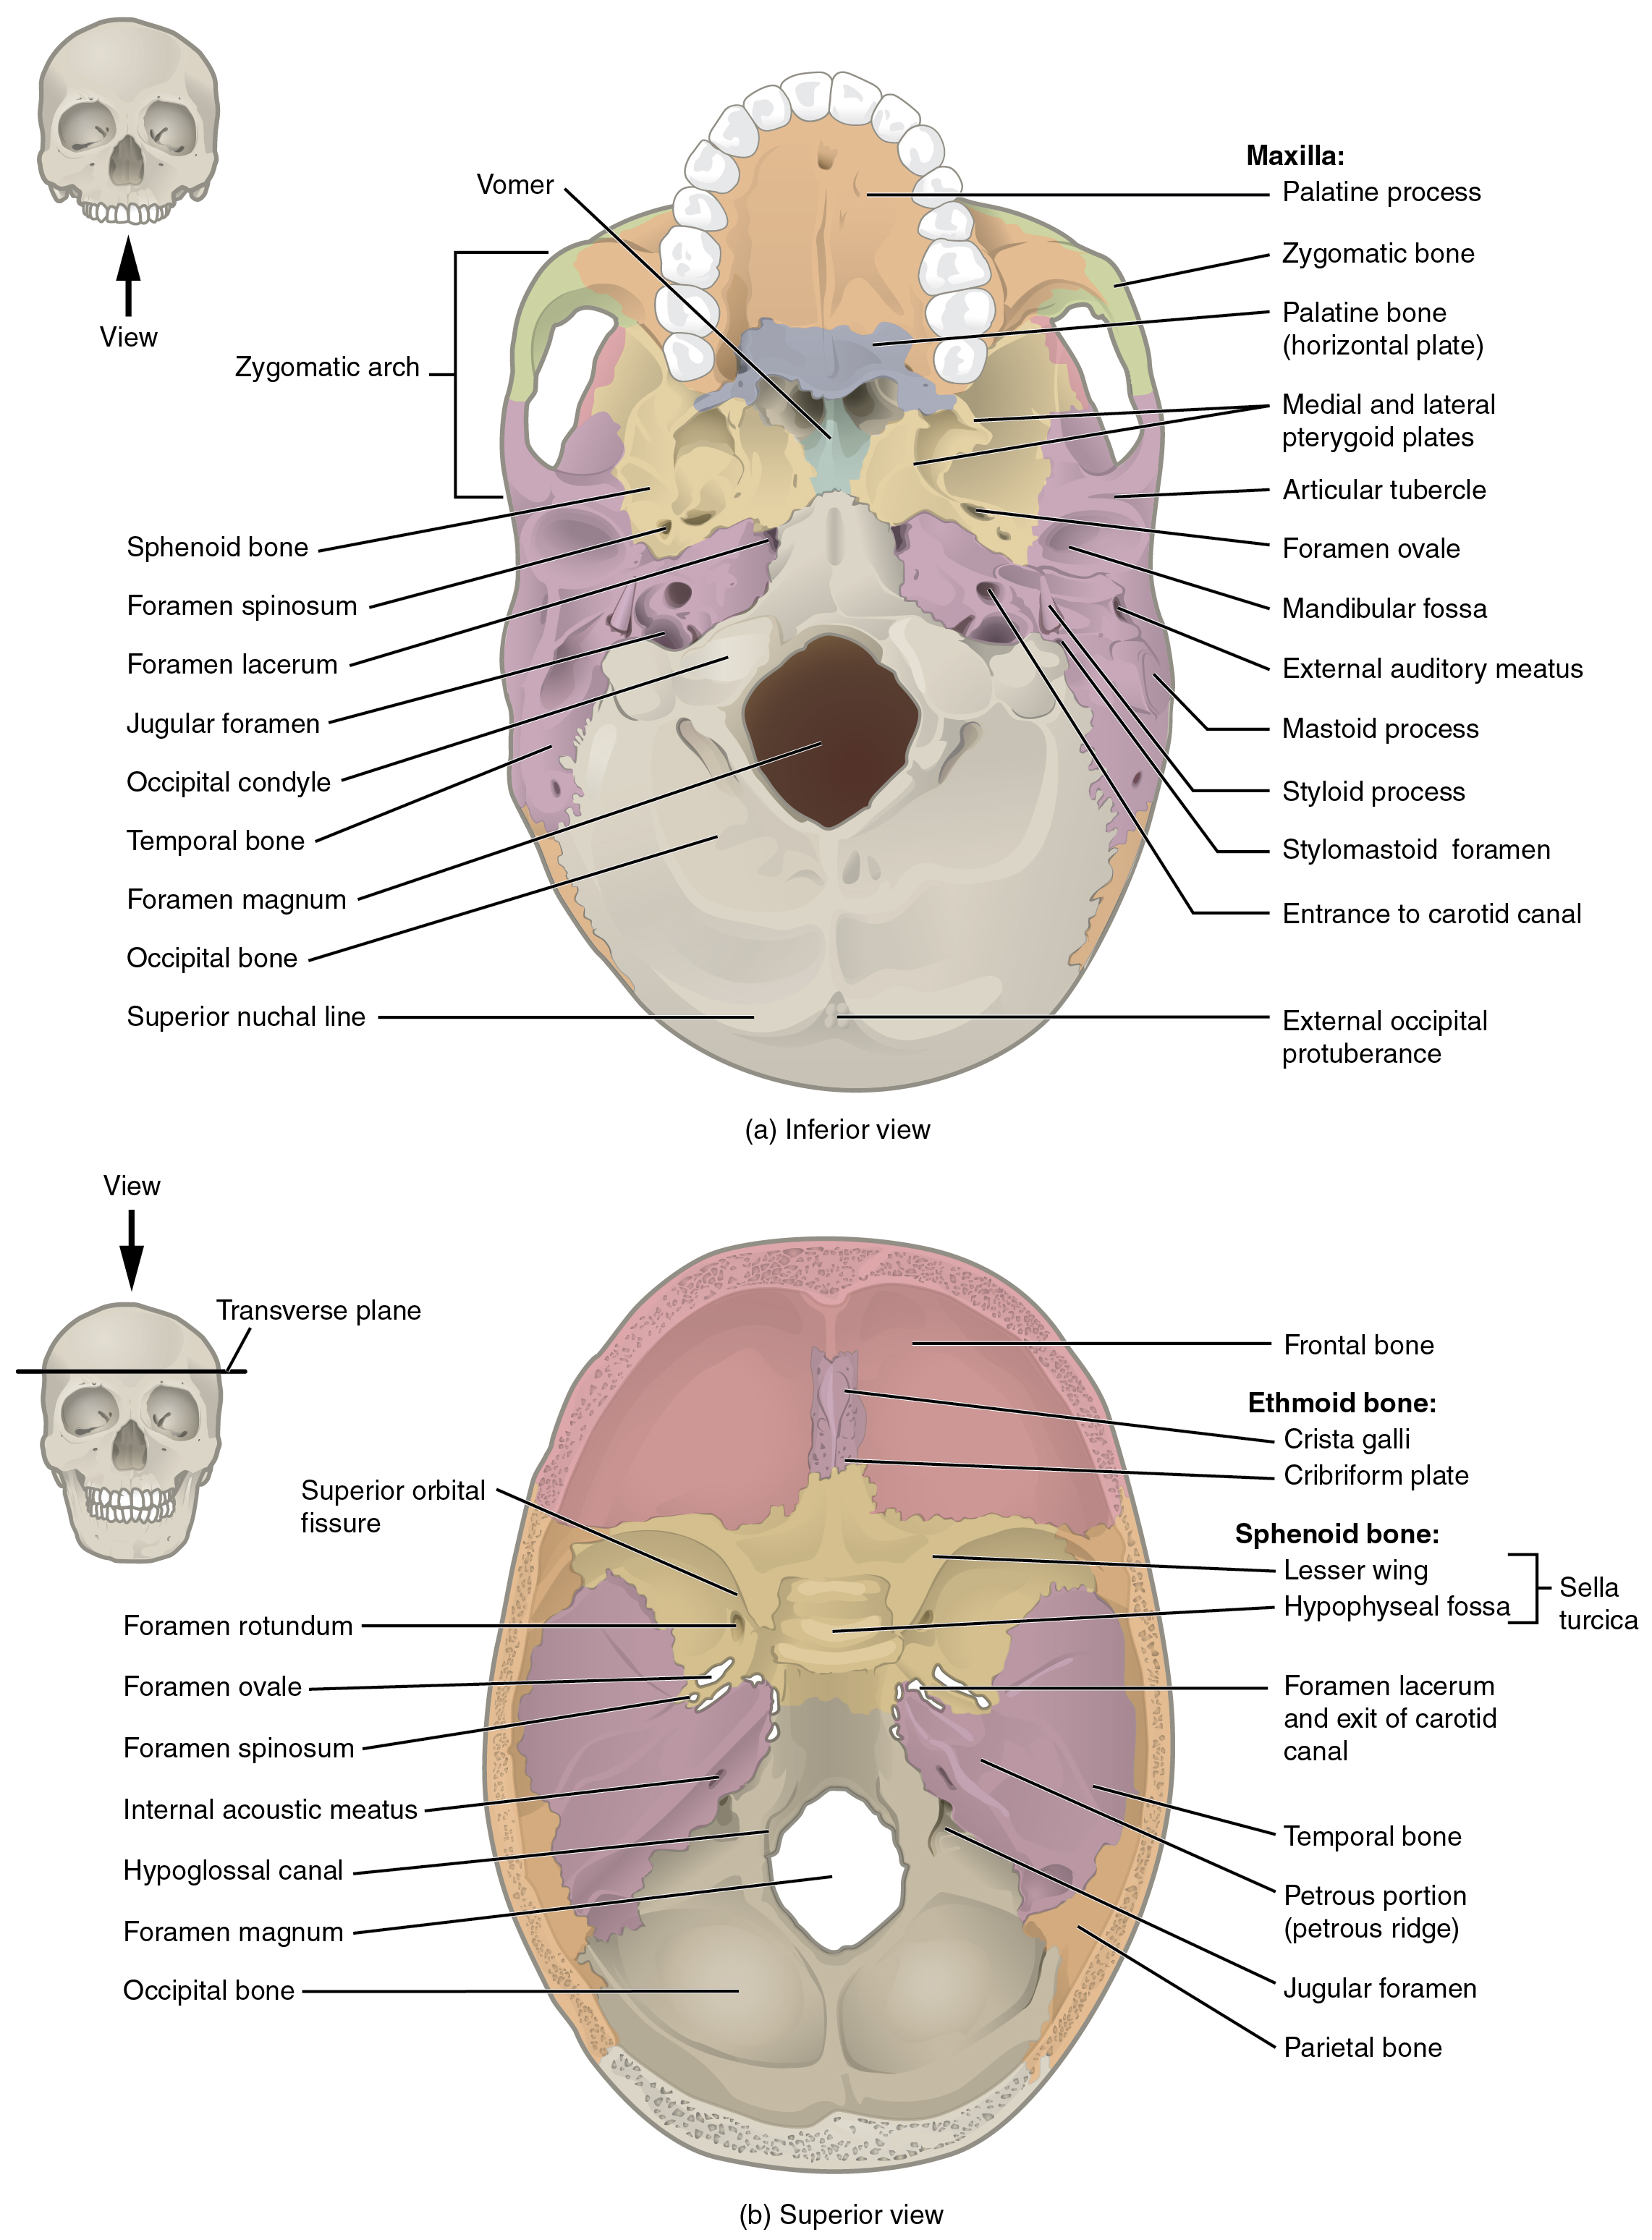
Find the superior orbital fissure, foramen rotundum and foramen ovale, and recall which trigeminal division uses each. Compare the palate, pterygoid plates and mandibular fossa in the inferior view.
Skull base & cranial foramina · OpenStax College · CC BY 3.0. Original image; displayed at a responsive size. Original publication.
The floor of mouth, suprahyoids and tongue
Mylohyoid forms a muscular diaphragm from the mylohyoid line to the hyoid and median raphe. Geniohyoid lies above it between the inferior genial tubercles and hyoid. Digastric has anterior and posterior bellies linked by an intermediate tendon tethered near the hyoid; stylohyoid runs from the styloid process towards the hyoid. With a stabilised mandible these muscles elevate the hyoid during swallowing; with a stabilised hyoid some assist mandibular depression.
Intrinsic tongue muscles change shape; genioglossus, hyoglossus and styloglossus change position. Most tongue motor supply is XII; palatoglossus receives vagal supply through the pharyngeal plexus. The lingual artery lies deep to hyoglossus, whereas the hypoglossal nerve and submandibular duct are superficial to it. The lingual nerve loops under the duct. These relations explain why floor-of-mouth surgery threatens several different functions.
| Muscle | Innervation | Main relationship |
|---|---|---|
| Mylohyoid and anterior digastric | Nerve to mylohyoid, from inferior alveolar nerve (V3) | First-arch muscles; form/support the oral floor |
| Posterior digastric and stylohyoid | Facial nerve (VII) | Second-arch muscles; elevate the hyoid |
| Geniohyoid | C1 fibres travelling with XII | Above mylohyoid; draws hyoid forwards |
| Intrinsic tongue, genioglossus, hyoglossus, styloglossus | Hypoglossal nerve (XII) | Tongue movement; distinguish from taste and touch |
Trigeminal divisions and facial sensory territories
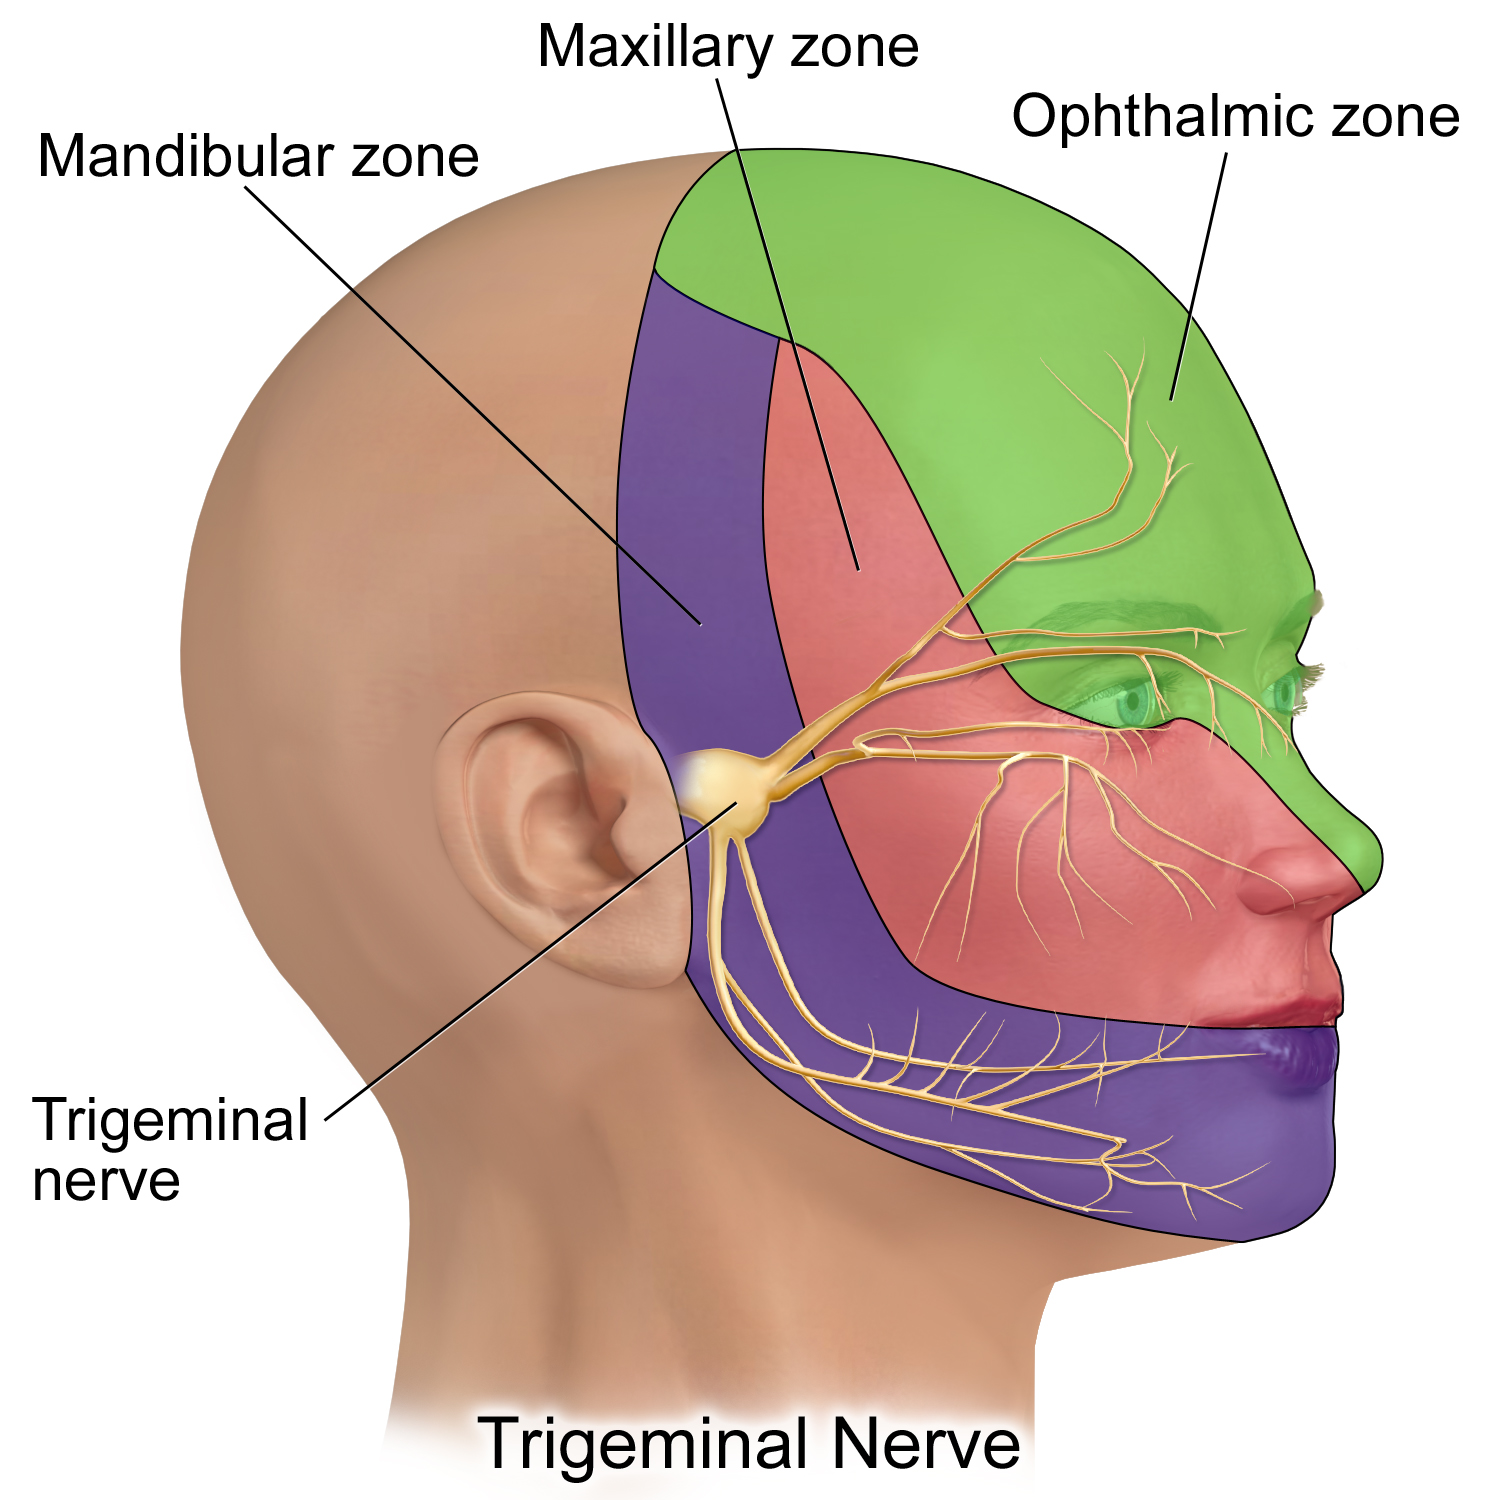
V1 is ophthalmic, V2 maxillary and V3 mandibular. This is a schematic sensory territory map, not a detailed map of every peripheral branch; V3 also carries motor fibres.
Trigeminal Nerve.png · BruceBlaus · CC BY-SA 4.0. None; reproduced without alteration.
Which division gives rise to the inferior alveolar and lingual nerves?
The mandibular division, V3. Distinguish lower lip/chin sensory change from altered tongue sensation.
Cranial nerves: separate sensation, taste and movement
V1 passes through the superior orbital fissure and V2 through foramen rotundum; both are sensory. V3 passes through foramen ovale and is mixed. Its inferior alveolar branch supplies mandibular teeth and continues as mental and incisive branches; its mylohyoid branch leaves before canal entry. The long buccal nerve supplies buccal mucosa and gingiva in the mandibular molar region, which an inferior alveolar block does not reliably anaesthetise.
The lingual nerve carries general sensation from the anterior two-thirds of the tongue. Chorda tympani fibres from VII join it, carrying taste and parasympathetic fibres to the submandibular ganglion. IX supplies general sensation and taste posteriorly. VII supplies facial expression, not facial skin sensation. XII controls most tongue movement. Consequently lower lip numbness, lower lip weakness and tongue deviation are distinct findings requiring different examinations.
Major salivary glands
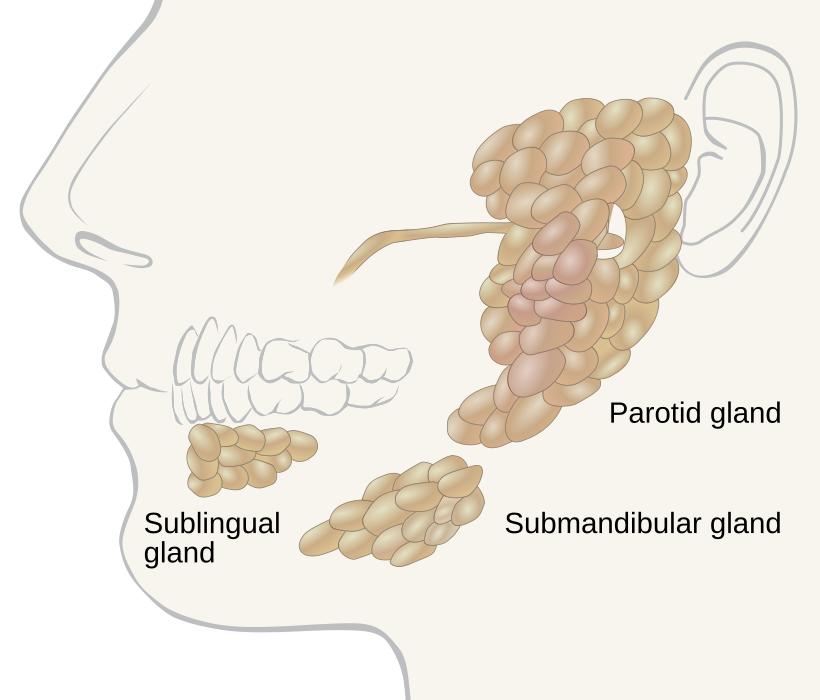
Locate the parotid, submandibular and sublingual glands. Use the gland distribution to relate swelling to the history; the diagram alone does not establish the cause of a mass.
Salivary glands labeled.svg · Goran tek-en, following request by and knowledge from Tom (LT) · CC BY-SA 4.0. None; reproduced without alteration.
Which major gland sits in the anterior floor of the mouth?
The sublingual gland. The submandibular duct also opens into the anterior floor of the mouth, near the lingual frenulum.
Arteries, veins and salivary pathways
The external carotid gives branches including facial, lingual and maxillary arteries. The facial artery crosses the mandibular lower border just anterior to masseter. The maxillary artery supplies deep facial structures and dental branches, including the inferior alveolar artery. Venous channels connect facial veins, the pterygoid plexus and intracranial venous systems; infections are assessed by their extent and systemic effect, not just the visible skin swelling.
The parotid duct crosses masseter, turns medially and pierces buccinator to open opposite the upper second molar. The facial nerve traverses the parotid but does not provide its secretomotor supply; parotid parasympathetic fibres originate from IX and relay in the otic ganglion. The submandibular gland wraps around the posterior mylohyoid border and drains at the sublingual caruncle. Meal-related swelling suggests investigating obstruction along this pathway.
Temporomandibular joint anatomy
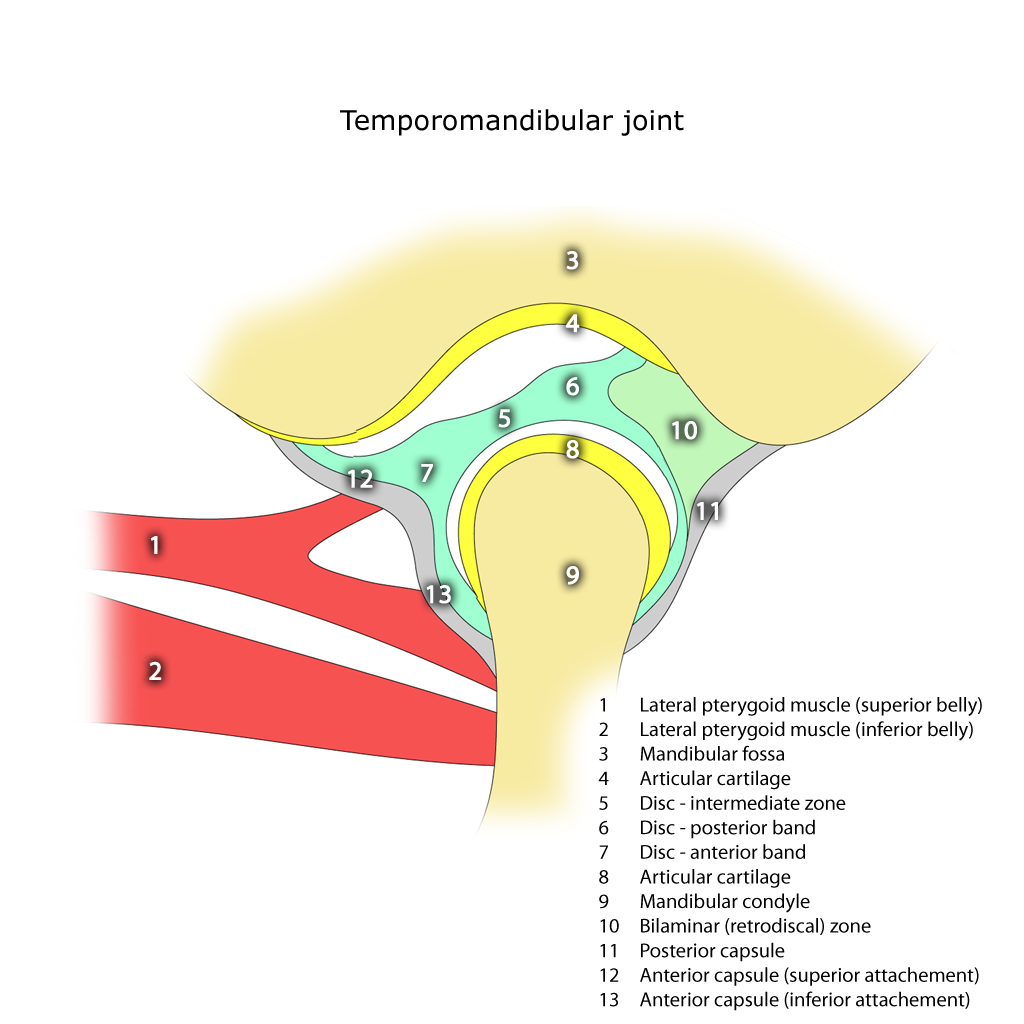
Identify the mandibular condyle, articular disc, articular eminence and mandibular fossa. The disc separates the upper and lower joint compartments.
Temporomandibular joint.png · Frank Gaillard · CC BY-SA 3.0. None; reproduced without alteration.
In which compartment does the main translational movement occur?
The superior compartment. Rotation predominantly occurs in the inferior compartment; normal opening combines both movements.
Lymphatic drainage and fascial spaces
Submental nodes receive drainage from structures including the central lower lip, chin and anterior floor of mouth; many other oral structures drain to submandibular nodes and then deep cervical chains. The tongue has extensive communicating lymphatics, and central or posterior lesions may drain bilaterally. A neck examination therefore follows the drainage pattern without assuming a midline lesion has only one relevant side.
Mylohyoid separates sublingual and submandibular spaces, which communicate posteriorly. The relation of an infected root apex to the muscle attachment helps explain the initial route of spread. Masticator-space involvement can produce trismus; deeper neck spaces can threaten swallowing and the airway and communicate towards the mediastinum. The site of swelling is evidence about spread, not a substitute for assessing physiological compromise.
Adult mandible: labelled lateral anatomy
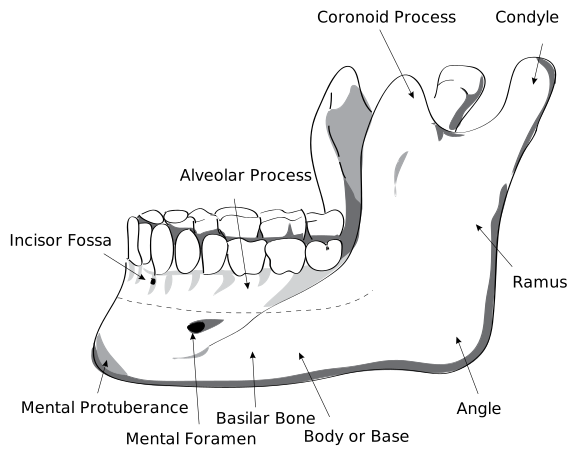
Locate the body, ramus, angle, condylar process, coronoid process and mental foramen. Use the labels to distinguish the two superior processes and the landmarks relevant to local anaesthesia and surgery.
HumanMandibleLeft.svg · Djexplo · CC0. None; reproduced without alteration.
Which nerve emerges through the mental foramen?
The mental nerve, a terminal branch of the inferior alveolar nerve, supplying the lower lip and chin.
Apply anatomy to an examination and surgical record
Map a sensory deficit by named territory and compare sides, using a consistent light-touch and other indicated sensory assessment. Record onset, functional effects, pain and change over time. Examine facial movement separately and assess tongue protrusion and lateral movement if indicated. A peripheral distribution supports localisation, but a spreading deficit or additional neurological signs may indicate a more proximal problem.
Root position, nerve course, vessel position and anatomical variation determine operative risk together with the intended technique. Imaging should answer a specific anatomical question. Consent and postoperative documentation become clearer when they name the relevant structure and possible deficit rather than using the single phrase “nerve damage”.
Suprahyoid and infrahyoid muscles
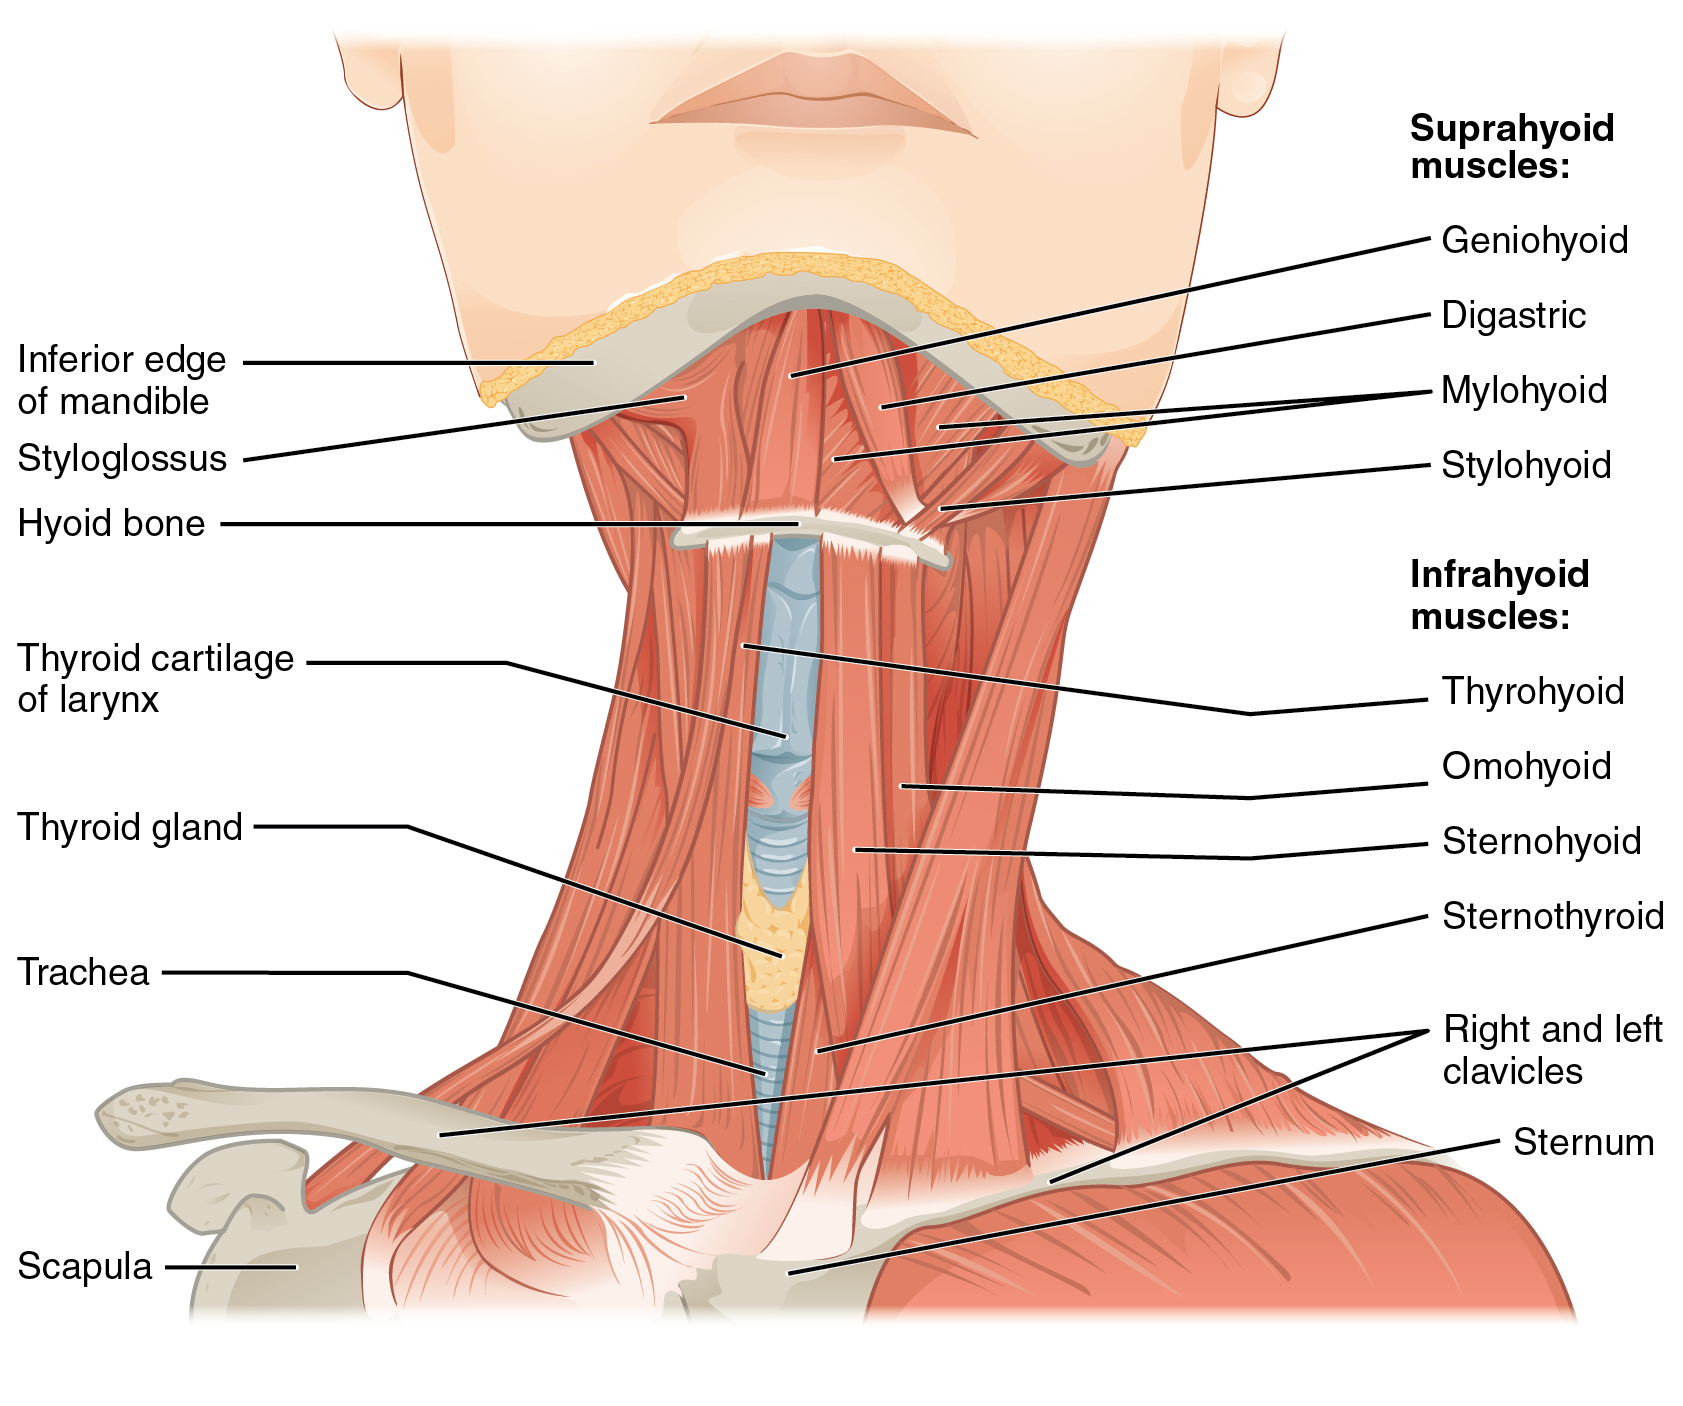
Locate the hyoid, then the four suprahyoid muscles. The mylohyoid forms the muscular floor of the mouth; the geniohyoid lies above it. Relate these muscles to swallowing, mandibular depression and the sublingual–submandibular boundary. The figure shows selected layers exposed for teaching.
1110 Muscle of the Anterior Neck.jpg · OpenStax · CC BY 4.0. None; original image reproduced without alteration.
Which muscle forms the main muscular floor of the mouth?
Mylohyoid. Geniohyoid lies superior to it; the anterior belly of digastric lies inferior to it.
Extrinsic tongue muscles and surface landmarks
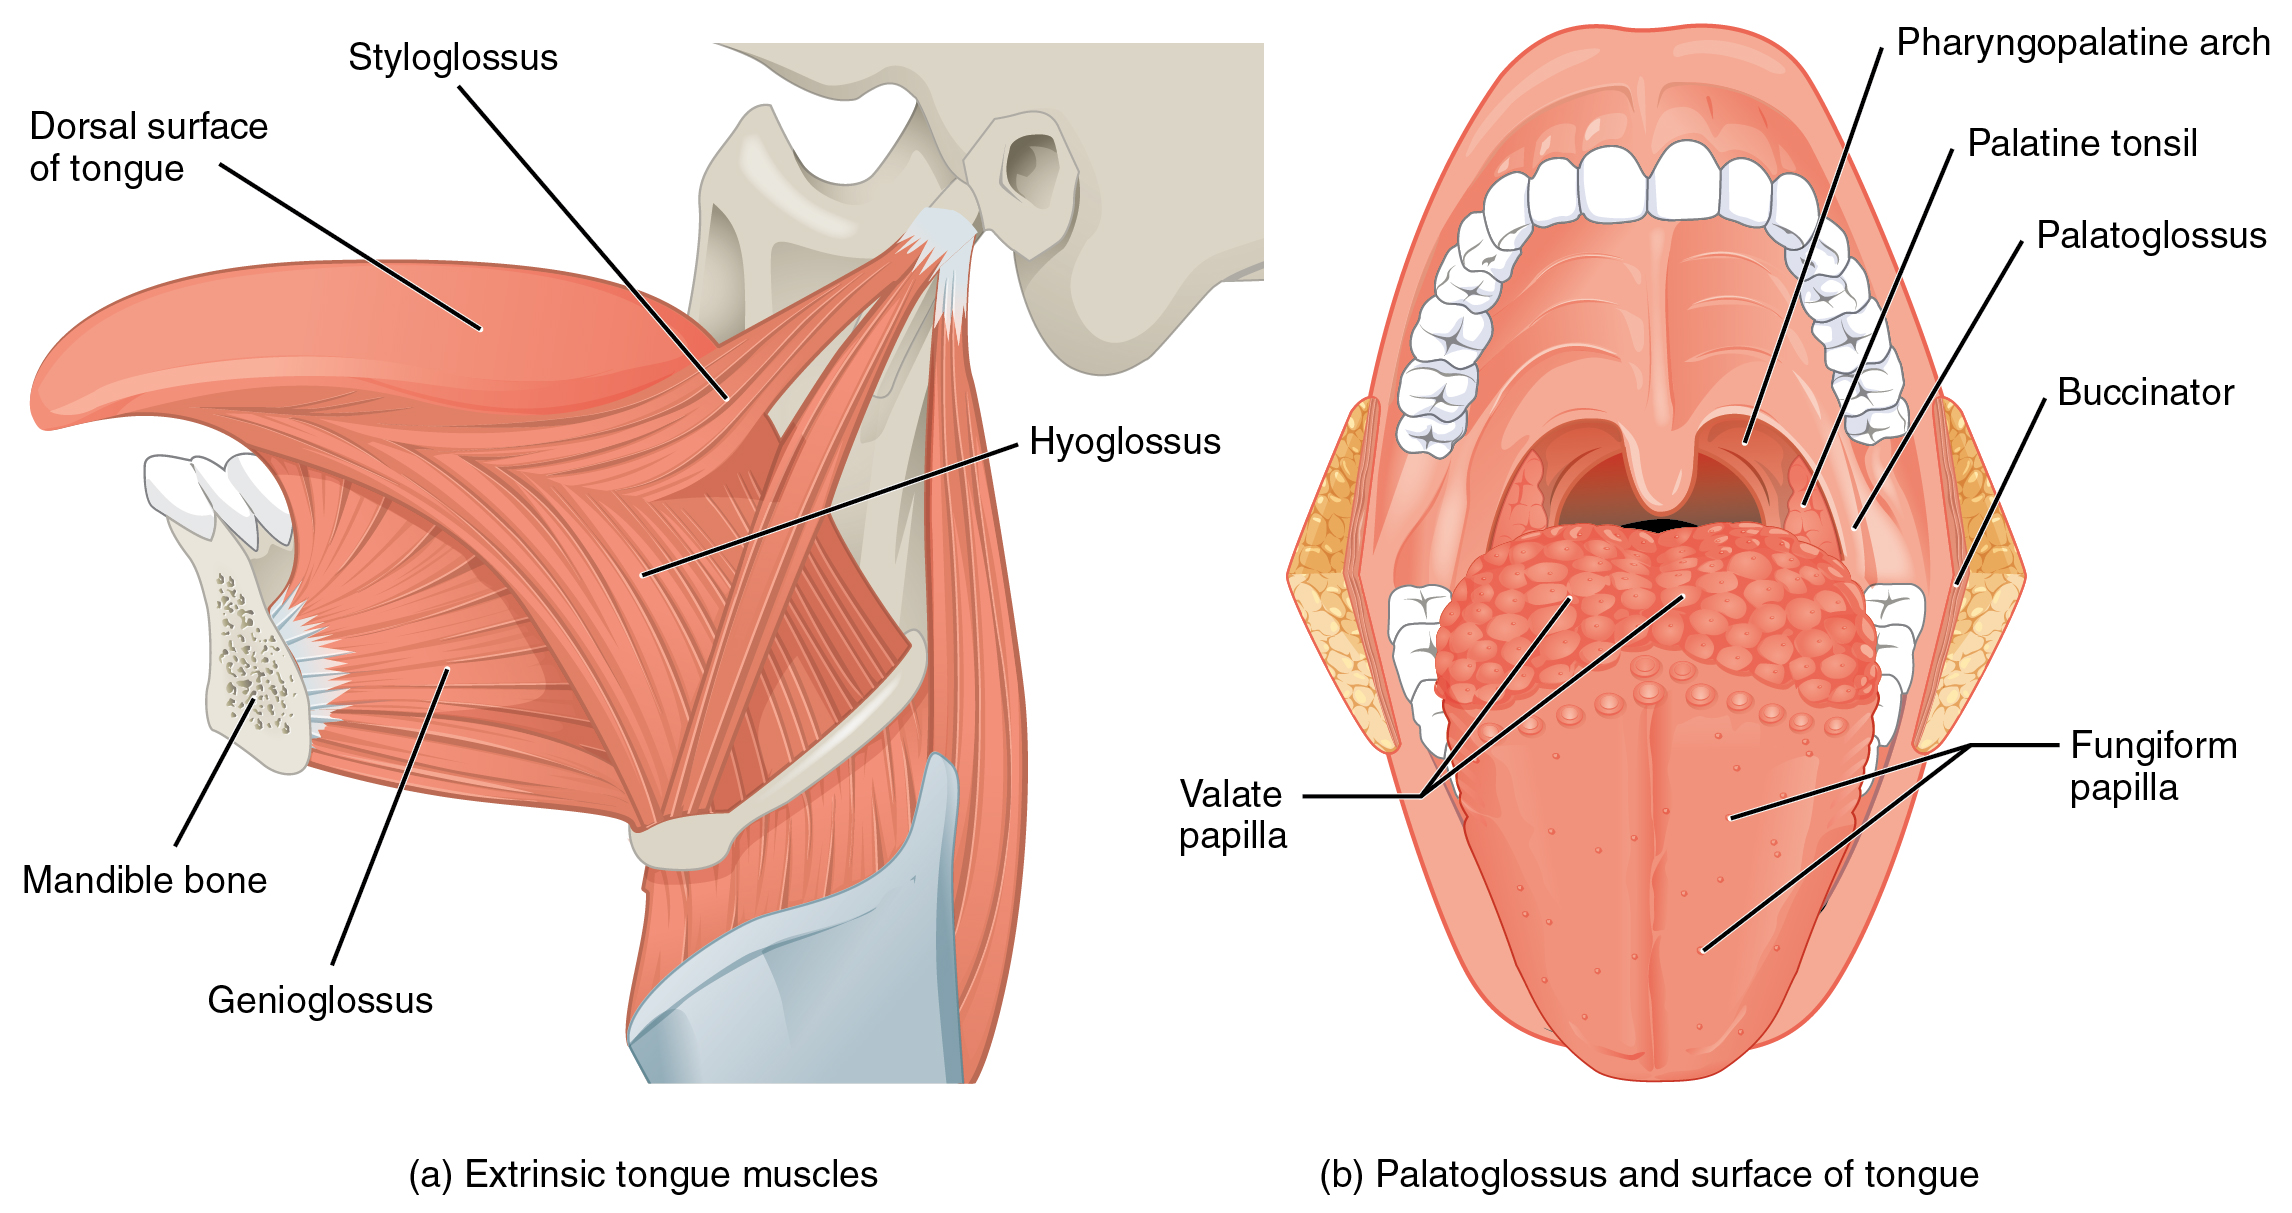
Follow genioglossus from the mandible, hyoglossus from the hyoid and styloglossus from the styloid region. The second view shows palatoglossus and tongue surface landmarks. “Pharyngopalatine arch” is the palatopharyngeal arch; “valate” in the original refers to vallate papillae.
1109 Muscles that Move the Tongue.jpg · OpenStax · CC BY 3.0. None; original image reproduced without alteration.
Which extrinsic tongue muscle is the exception to hypoglossal motor supply?
Palatoglossus, which is supplied through the pharyngeal plexus by the vagus nerve. The other extrinsic tongue muscles receive hypoglossal supply.
The four muscles of mastication
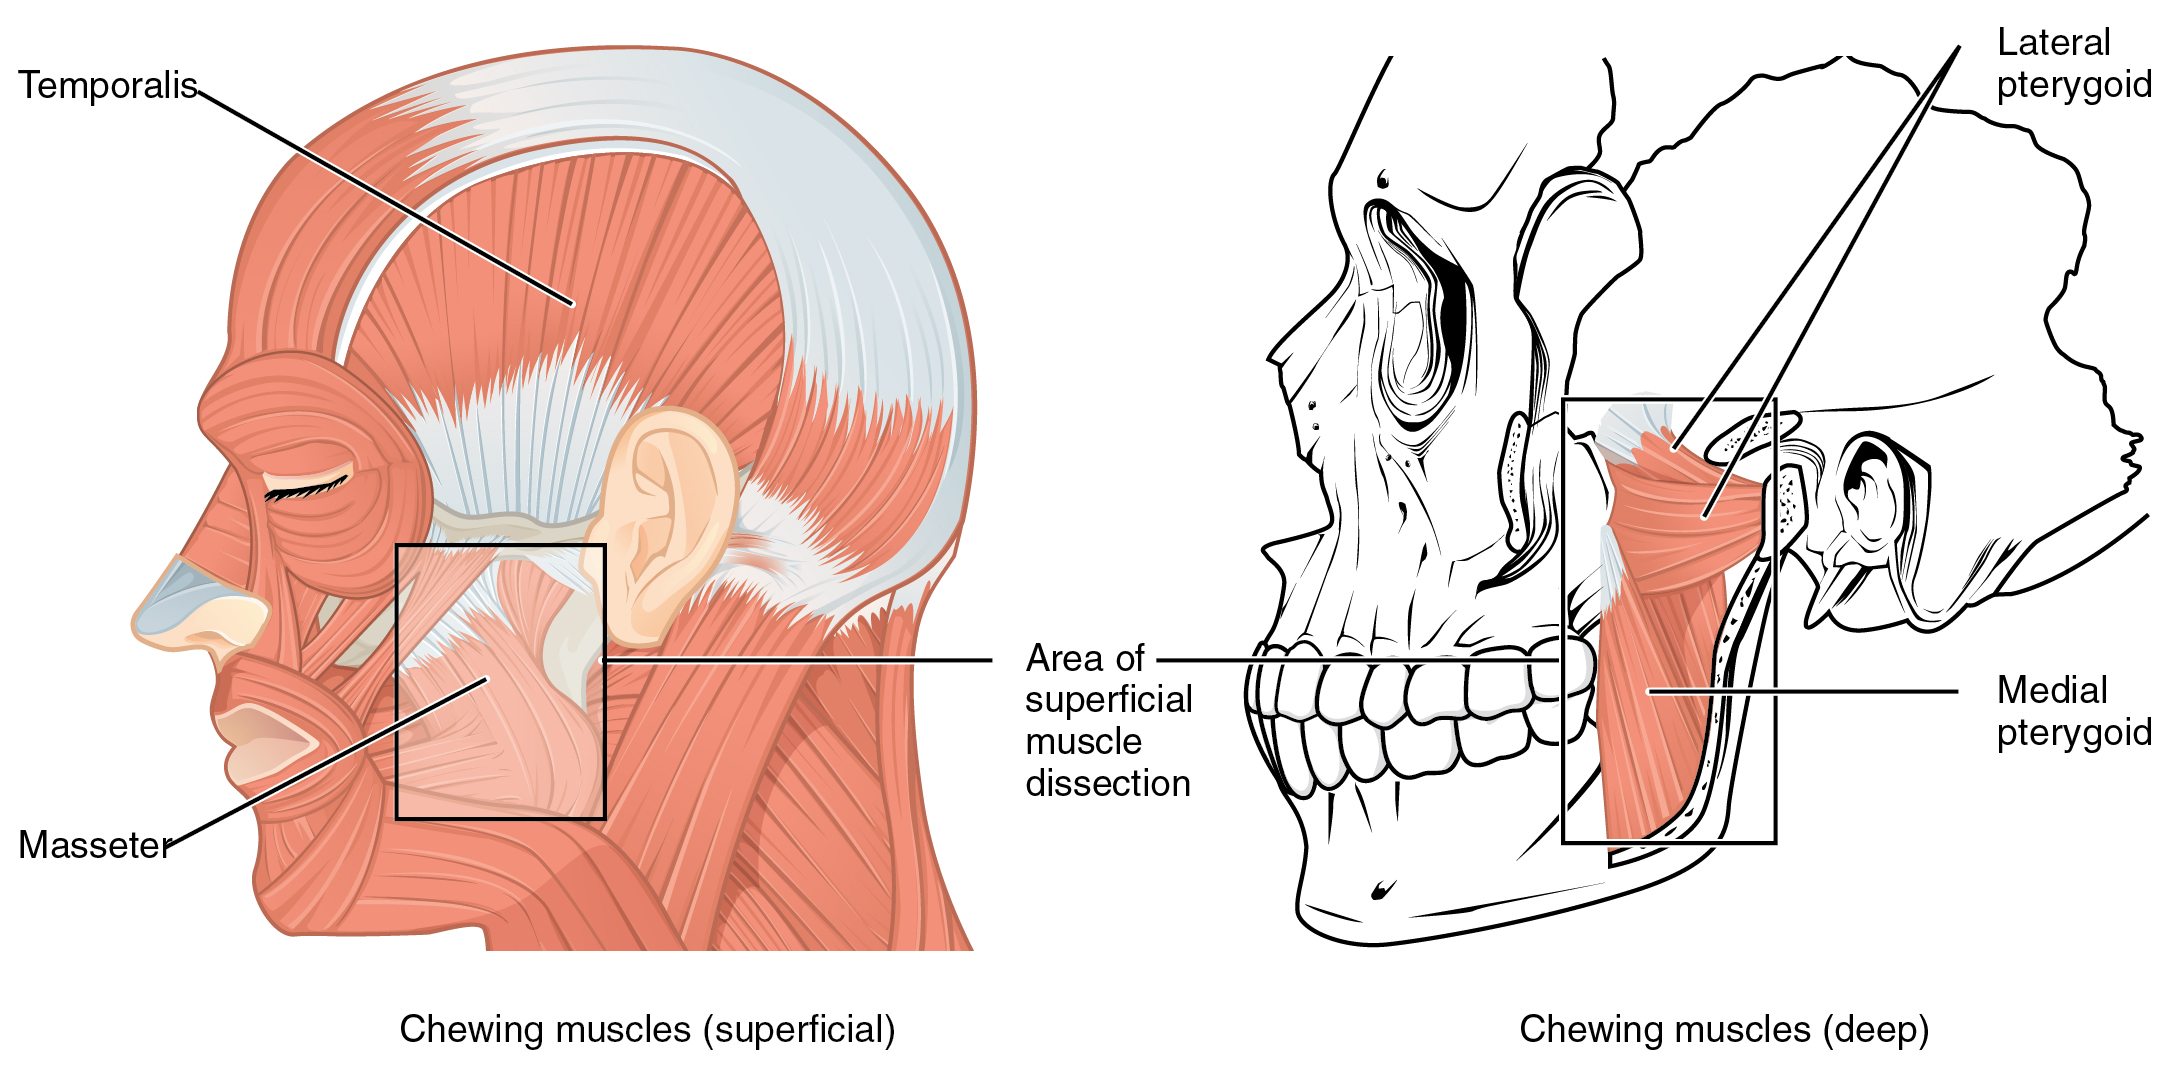
Identify temporalis and masseter in the superficial view, then both pterygoid muscles in the deeper view. Use the lines of pull to explain mandibular elevation, protrusion and side-to-side movement. All four receive motor supply from the mandibular division of the trigeminal nerve.
1108 Muscle that Move the Lower Jaw.jpg · OpenStax · CC BY 4.0. None; original image reproduced without alteration.
Which division of the trigeminal nerve supplies the muscles of mastication?
The mandibular division, V3. Do not confuse this with the facial nerve supply to the muscles of facial expression.
Soft-palate and pharyngeal muscles: posterior view
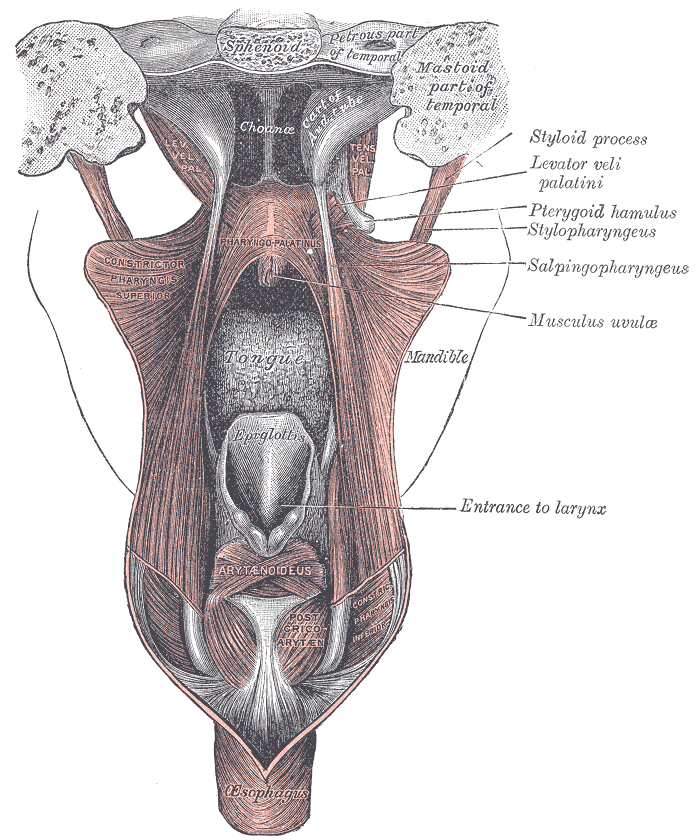
Find levator veli palatini and the tensor tendon turning around the pterygoid hamulus. This posterior view also shows the pharyngeal wall and laryngeal entrance. The historical label “pharyngo-palatinus” denotes palatopharyngeus.
Gray1028.png · Henry Vandyke Carter; reproduced in Gray’s Anatomy (1918), plate 1028 · Public domain. None; original image reproduced without alteration.
Which soft-palate muscle has mandibular nerve supply?
Tensor veli palatini, supplied by V3 through the nerve to medial pterygoid. The other principal palatal muscles receive vagal supply through the pharyngeal plexus.
Tongue muscle architecture in coronal section
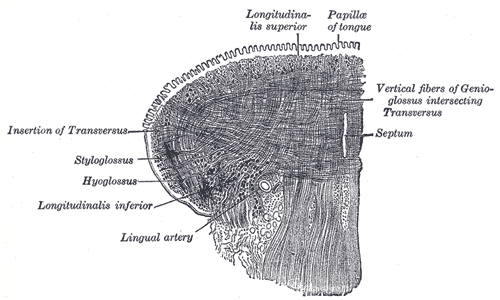
Trace the longitudinal and transverse fibres around the lingual septum. The original also labels vertical fibres of genioglossus, an extrinsic muscle; this is not a diagram of intrinsic muscles alone. Intrinsic fibres principally change tongue shape, while extrinsic muscles reposition it.
Gray1020.png · Henry Vandyke Carter; reproduced in Gray’s Anatomy (1918), plate 1020 · Public domain. None; original image reproduced without alteration.
How do intrinsic and extrinsic tongue muscles differ functionally?
Intrinsic muscles primarily change tongue shape. Extrinsic muscles primarily move the tongue as a whole; coordinated movements recruit both groups.
Cranial nerves at the base of the brain
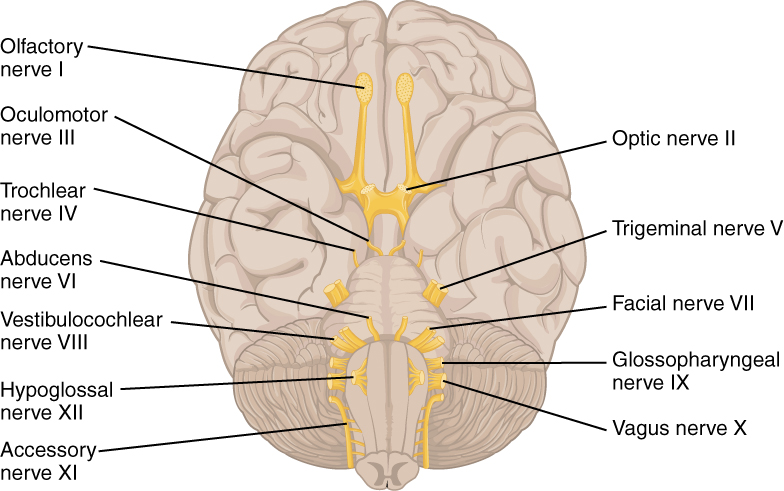
Orientate the inferior brain surface, then locate V, VII, IX, X and XII. Connect them to facial sensation and mastication, facial expression, swallowing and palatal function, and tongue movement. This is a brain-surface overview, rather than a map of the skull foramina.
1320 The Cranial Nerves.jpg · OpenStax · CC BY 4.0. None; original image reproduced without alteration.
Which cranial nerve principally controls tongue movement?
The hypoglossal nerve, XII. Palatoglossus is the exception among the tongue muscles and is supplied through the vagus nerve.
Maxillary and mandibular dental nerve branches
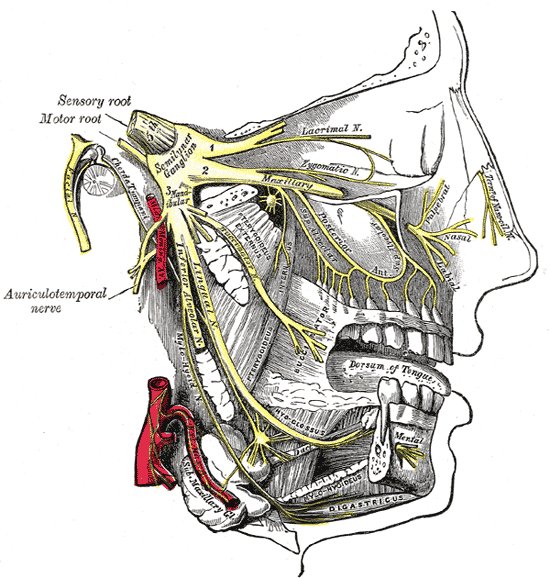
Follow V2 toward the upper teeth and V3 toward the lingual and inferior alveolar nerves. The original terms “inferior dental” and “submaxillary ganglion” correspond to inferior alveolar nerve and submandibular ganglion. This shows anatomy; it does not specify a safe needle trajectory.
Gray778.png · Henry Vandyke Carter; reproduced in Gray’s Anatomy (1918), plate 778 · Public domain. None; original image reproduced without alteration.
Which nerve continues through the mental foramen?
The mental branch of the inferior alveolar nerve, providing sensation to the lower lip and chin. The incisive branch continues within the mandible.
Mandibular body fracture: follow the cortex
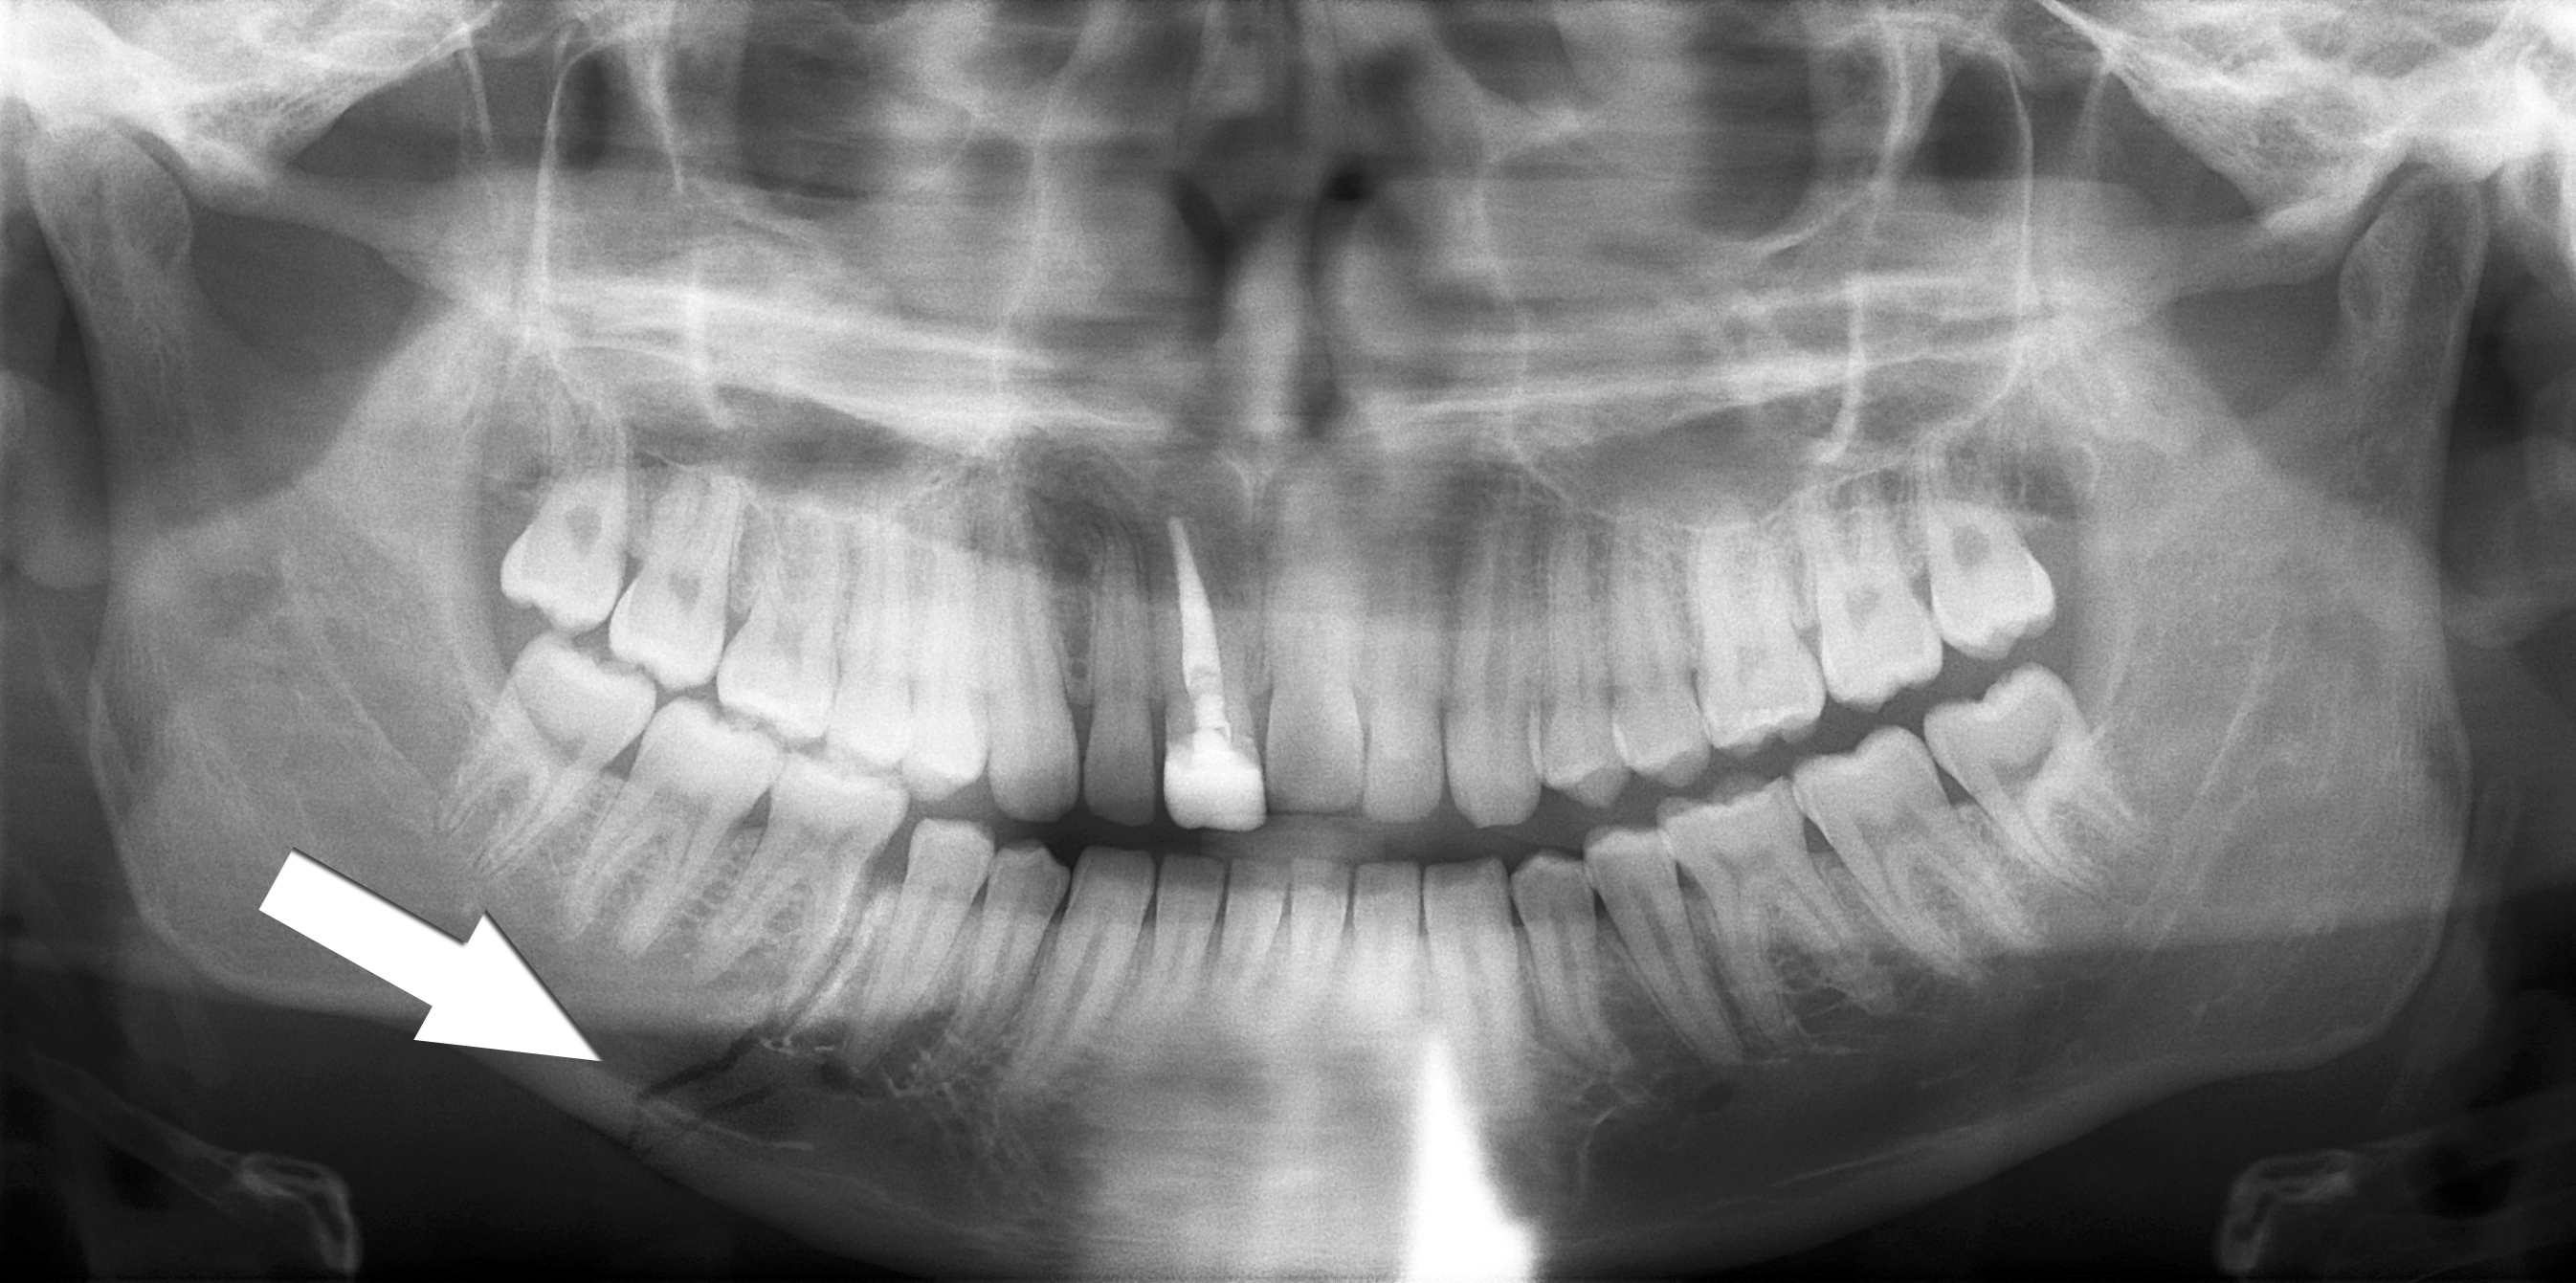
Trace the lower mandibular border through the fracture marked by the source arrow. Inspect the teeth and the remaining mandible as well as the marked site. The source describes a right body fracture. Clinical occlusion, soft tissues, sensation and the mechanism of injury remain part of the trauma assessment.
Simple mandible fracture.jpg · Coronation Dental Specialty Group · CC BY 3.0. Reproduced without alteration. Labels, arrows and circles, where present, belong to the source image.
Why should the search continue after finding the marked fracture?
Another fracture or associated injury may be present. Review the whole image and the patient’s clinical findings rather than stopping at the first abnormality.
Multiple mandibular fractures: inspect every region
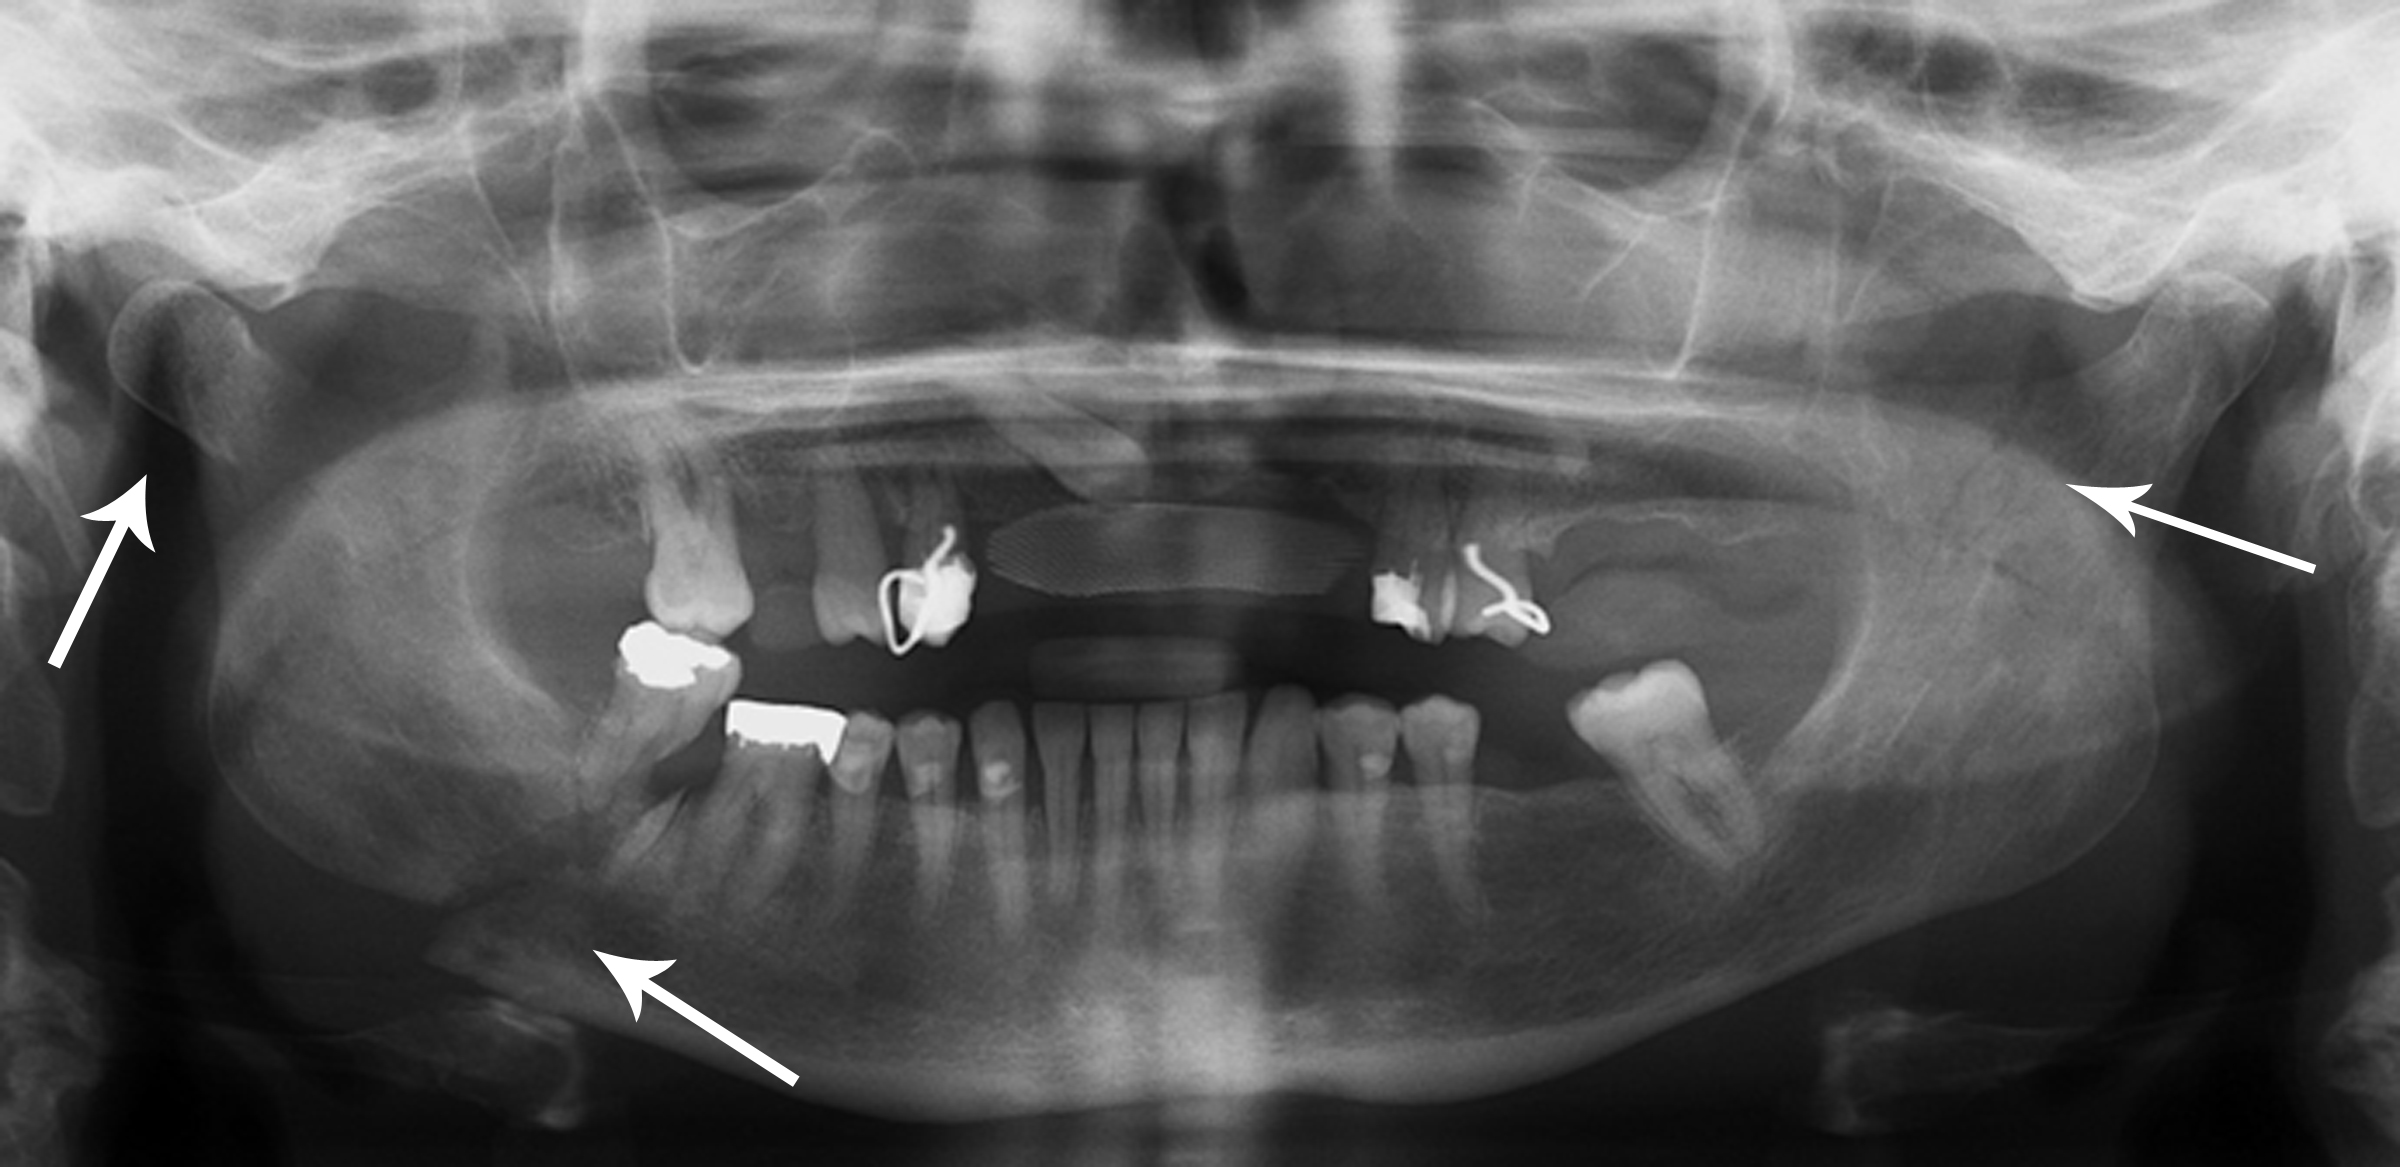
The source records right condylar and body fractures and a left coronoid fracture. Use the original arrows to orient the search, then trace each border systematically. A panoramic projection has overlap and positional limitations; a single teaching image cannot establish the complete injury pattern or its management.
Multiple mandible fractures.jpg · Coronation Dental Specialty Group · CC BY 3.0. Reproduced without alteration. Labels, arrows and circles, where present, belong to the source image.
Which clinical information is needed alongside the fracture pattern?
Airway and wider trauma assessment, occlusion, mouth opening, dental and soft-tissue injury, sensory findings and relevant patient factors, with additional investigations chosen for the clinical question.
A distinction to remember
Do not confuse lingual nerve sensation, chorda tympani taste, facial nerve movement and hypoglossal tongue movement. Their fibres may travel together locally but their functions remain distinct.
After lower third-molar surgery a patient reports tongue numbness and altered taste, but lip sensation and tongue movement are normal. Which structure is most likely involved?
Reveal the reasoning
The lingual nerve carrying chorda tympani fibres best explains the sensory and taste changes. Normal lower lip sensation makes an isolated inferior alveolar injury less likely; normal tongue movement does not rule out lingual sensory injury. Document the territory, pain and functional impact and arrange appropriate review.
Guidance to read alongside this chapter
Test your recall
Which openings transmit the three trigeminal divisions?
Show answer
V1 uses the superior orbital fissure, V2 foramen rotundum and V3 foramen ovale. V1 and V2 are sensory; V3 also carries motor fibres to mastication and selected first-arch muscles. Trace a named peripheral branch back through the correct division.