
Dental anatomy and occlusion
Recognise normal tooth form before interpreting a restoration, radiograph or worn dentition. Occlusion describes how teeth meet and move within a system that also includes joints, muscles and periodontal support.
THE ANATOMY LAB / INTERACTIVE 3DExplore the jaws and individual teeth in 3D↗Quick revision summary
Dentitions, surfaces and notation
The primary dentition has twenty teeth: two incisors, one canine and two molars in each quadrant. The complete permanent dentition has thirty-two, adding two premolars and three molars per quadrant.
Contacts, contours and the gingival environment
The anatomical crown is enamel-covered; the clinical crown is the portion visible above the gingival margin. Recession can expose root without changing the anatomical crown. The cemento-enamel junction is therefore a stable structural reference, whereas the gingival margin varies with eruption, inflammation, enlargement and recession.
Apply the anatomy to restorative planning
Before restoring a tooth, assess the remaining walls and cusps, the neighbouring contact and marginal ridge, opposing teeth and static and excursive space. A restoration must achieve a seal, maintainable contour and sufficient material thickness while preserving sound tissue.
Common mistake
Root number, canal number and crown appearance are related but not interchangeable. A normal-looking crown cannot establish the anatomy hidden beneath it.
Dental anatomy and occlusion
Recognise normal tooth form before interpreting a restoration, radiograph or worn dentition. Occlusion describes how teeth meet and move within a system that also includes joints, muscles and periodontal support.
Dentitions, surfaces and notation
The primary dentition has twenty teeth: two incisors, one canine and two molars in each quadrant. The complete permanent dentition has thirty-two, adding two premolars and three molars per quadrant. Permanent premolars replace primary molars; permanent molars have no primary predecessors. Mixed dentition contains both sets, so an erupted first permanent molar must not be mistaken for a primary tooth merely because no tooth was shed.
Describe mesial and distal relative to the arch midline, labial or buccal towards lips or cheeks, and lingual or palatal towards tongue or palate. Incisal edges occur anteriorly and occlusal surfaces posteriorly. FDI notation uses a quadrant digit followed by position from the midline; specify the notation system and dentition when communicating across services.
Tooth & supporting tissues
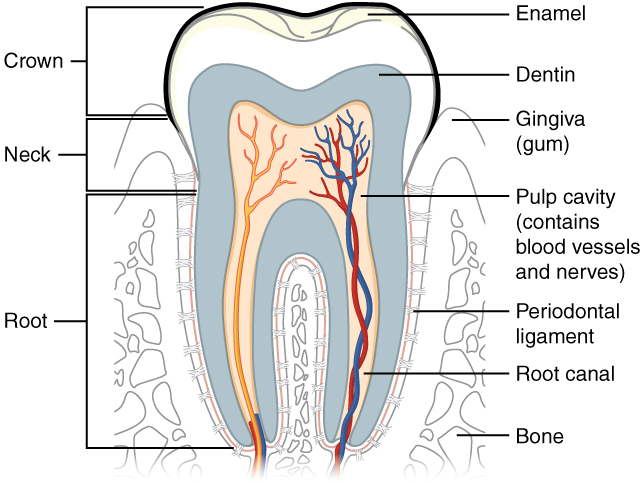
Trace the pulp and root canal to the apical region, then identify the periodontal ligament and supporting bone. Relate these structures to avulsion, apical pathology and extraction. The original uses the spelling “dentin”; cementum is not separately labelled.
Tooth & supporting tissues · OpenStax College · CC BY 3.0. Original image; displayed at a responsive size. Original publication.
Identify teeth by a combination of features
Incisors have cutting edges, canines a single prominent cusp, and posterior teeth broader occlusal tables. Maxillary incisors generally show a more prominent cingulum and lingual anatomy than mandibular incisors. The mandibular first premolar often has a dominant buccal cusp and a small lingual cusp; the maxillary first premolar commonly has two substantial cusps and may have two roots. Individual variation is normal.
Maxillary molars commonly have three roots: mesiobuccal, distobuccal and palatal. Their occlusal anatomy includes an oblique ridge between the mesiolingual and distobuccal cusps. Mandibular molars commonly have mesial and distal roots; a first molar often has five cusps, whereas a second commonly has four. Crown form, root form, radiographs and the clinical context should agree before identifying or treating a tooth.
The four muscles of mastication
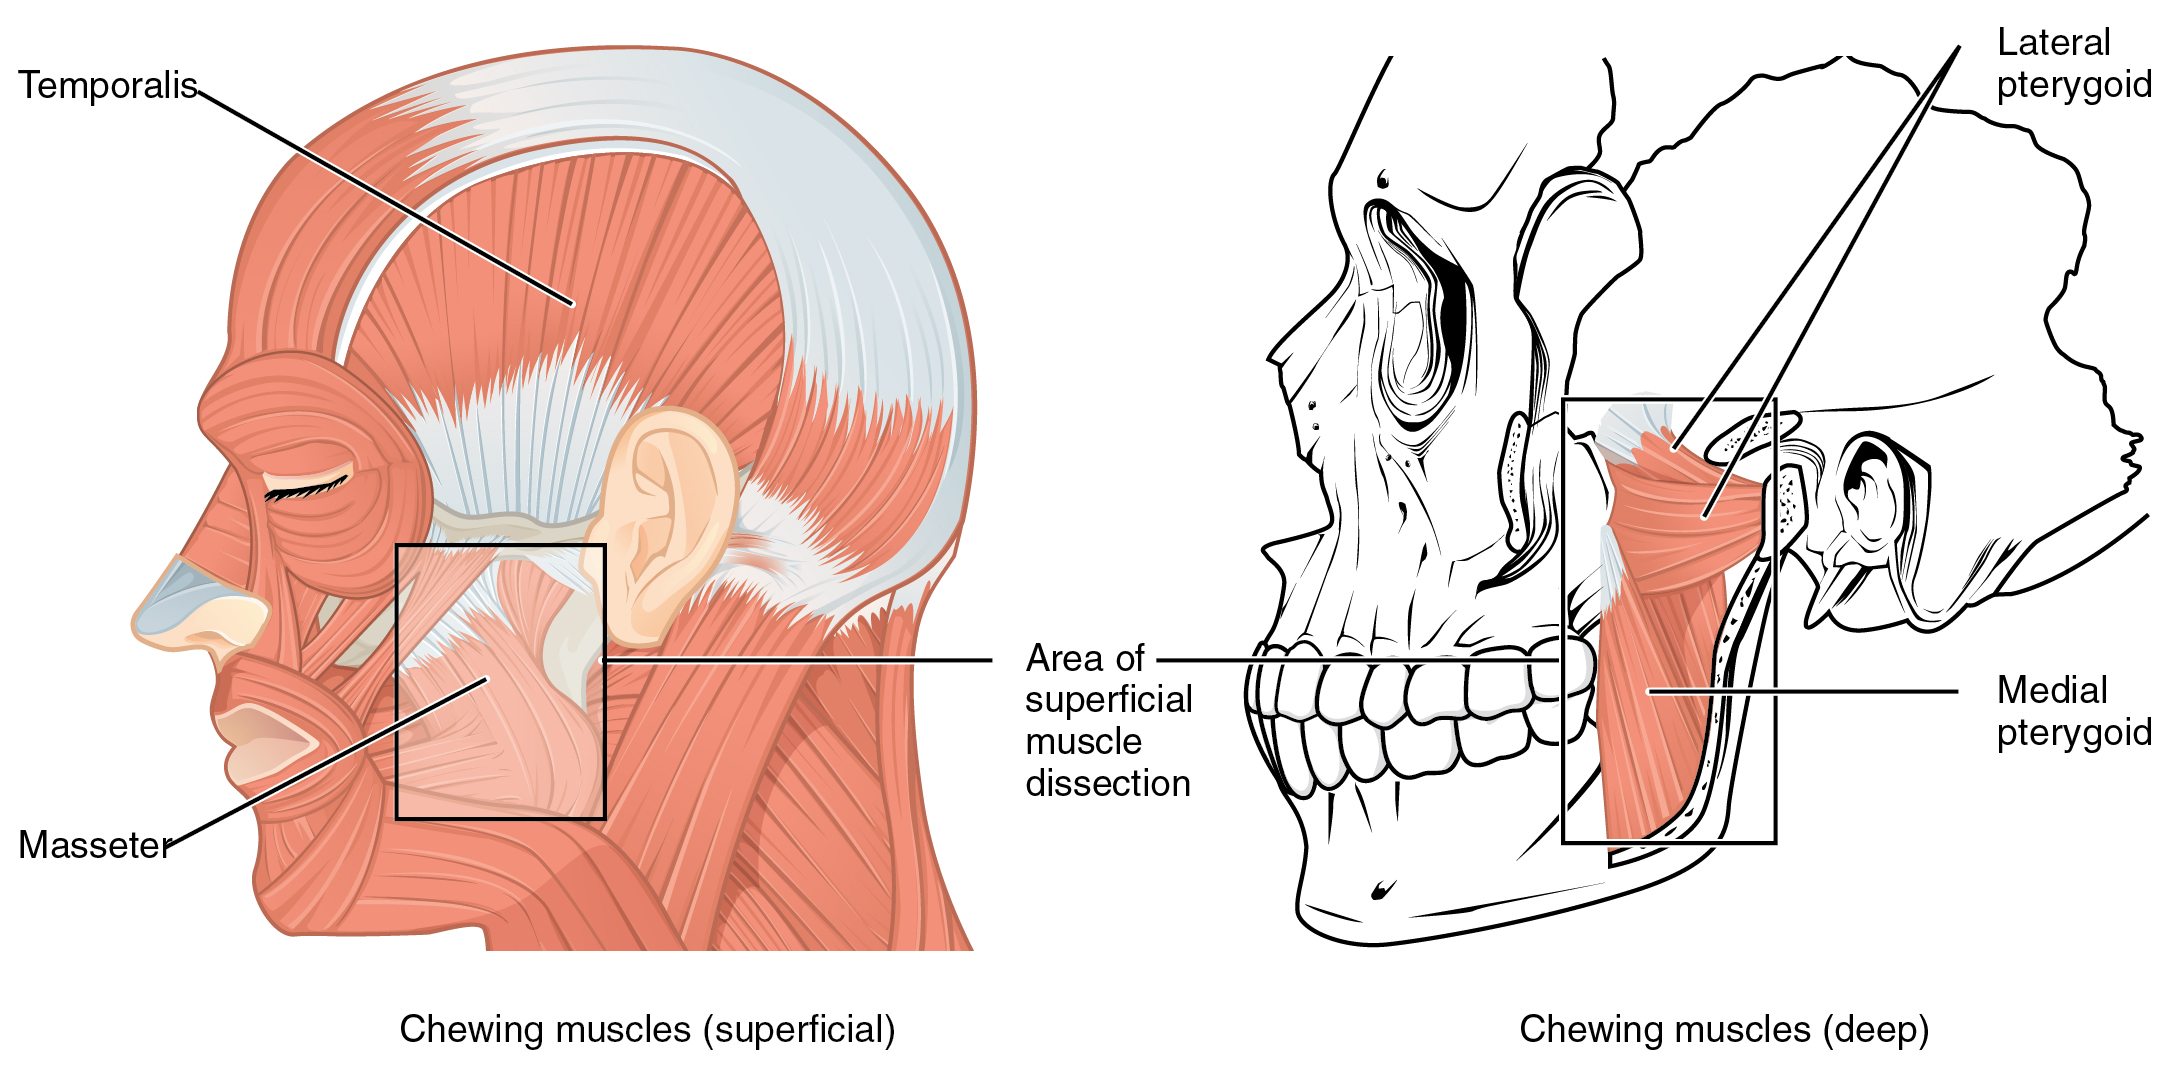
Identify temporalis and masseter in the superficial view, then both pterygoid muscles in the deeper view. Use the lines of pull to explain mandibular elevation, protrusion and side-to-side movement. All four receive motor supply from the mandibular division of the trigeminal nerve.
1108 Muscle that Move the Lower Jaw.jpg · OpenStax · CC BY 4.0. None; original image reproduced without alteration.
Which division of the trigeminal nerve supplies the muscles of mastication?
The mandibular division, V3. Do not confuse this with the facial nerve supply to the muscles of facial expression.
Root and canal anatomy are different maps
A root may contain more than one canal, and canals can divide, merge, curve or communicate through isthmuses. Maxillary molar mesiobuccal roots commonly warrant a search for additional canal anatomy; mandibular molar mesial roots frequently contain two canals. These patterns guide access and investigation but do not prove a particular tooth has the textbook arrangement.
Roots also determine extraction mechanics and prosthetic support. Divergence, curvature, hypercementosis, fusion and proximity to adjacent roots can obstruct a proposed delivery path. In a heavily restored tooth, the apparent crown axis may not match the root axis. Identify the actual anatomy rather than extending a preparation or increasing force to make the tooth conform to an expectation.
Overjet and overbite
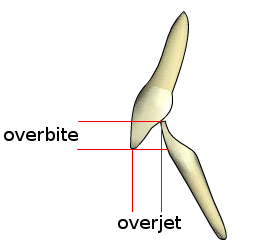
Overjet describes the horizontal relationship between the incisors; overbite describes their vertical overlap. Record the magnitude, direction and whether the overbite is complete or incomplete. The schematic is not drawn to a clinical measurement scale.
Overjet-overbite.png · Nielson2000 · CC BY-SA 3.0. None; original image reproduced without alteration.
Which measurement is horizontal: overjet or overbite?
Overjet is horizontal. Overbite is the vertical overlap of the incisors.
Contacts, contours and the gingival environment
The anatomical crown is enamel-covered; the clinical crown is the portion visible above the gingival margin. Recession can expose root without changing the anatomical crown. The cemento-enamel junction is therefore a stable structural reference, whereas the gingival margin varies with eruption, inflammation, enlargement and recession.
Proximal contact areas, marginal ridges and buccal, lingual and gingival embrasures work together. Restoration of contact tightness alone does not restore this anatomy: an overhang, inappropriate emergence profile, uneven marginal ridge or absent papillary support can retain plaque or pack food. Contour should permit cleaning and respect periodontal tissues rather than simply fill the available space.
Class II division 1: relationship schematic
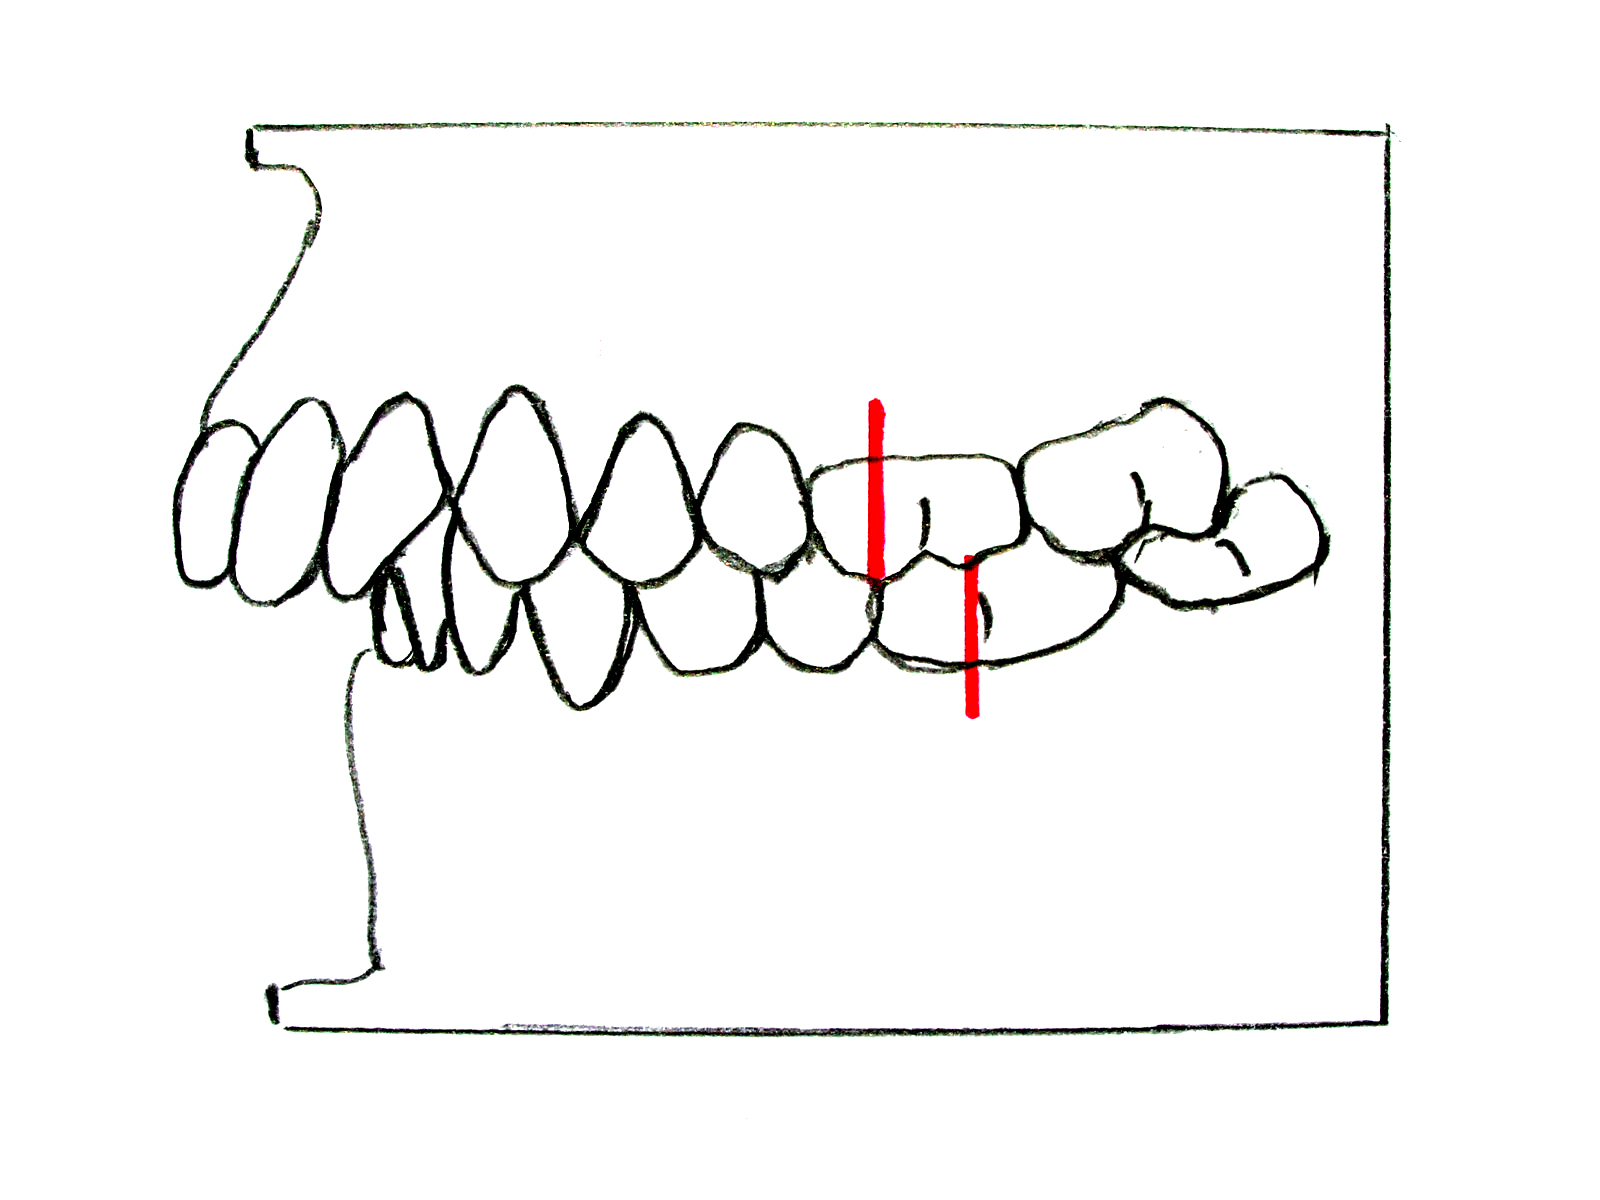
Compare the posterior molar relationship with the upper-incisor inclination and increased overjet. The red reference marks demonstrate the Class II molar relationship. Describe the incisor relationship separately from the molar and skeletal relationships in a clinical assessment.
Zahnfehlstellung Angle-Klasse II-1.jpg · Dr. Georg Risse · CC BY-SA 3.0. None; original image reproduced without alteration.
What upper-incisor feature typically distinguishes Class II division 1 from division 2?
Division 1 usually has proclined or normally inclined upper incisors with increased overjet; division 2 has retroclined upper central incisors.
Static occlusion: describe the relationship precisely
Maximum intercuspation is the position of greatest intercuspation of the teeth. Centric relation describes a reproducible maxillomandibular relationship independent of tooth contact; it is not another name for the habitual bite. Whether the positions coincide is a clinical observation. Vertical dimension describes separation of reference points and needs a stated context, such as occlusion or rest.
Overjet is the horizontal incisor relationship and overbite the vertical overlap. Record direction, amount and which teeth are involved. A crossbite is a reversed buccolingual relationship and may be anterior or posterior; an open bite lacks vertical contact in a stated region. Angle molar classification describes an anteroposterior dental relationship, not a complete skeletal diagnosis.
| Term | What is being described | What it does not establish |
|---|---|---|
| Maximum intercuspation | Tooth-determined best fit | A joint-based reference position |
| Centric relation | Jaw relationship independent of tooth contact | The patient’s usual tooth contact |
| Overjet / overbite | Horizontal / vertical incisor relationship | The complete skeletal pattern |
| Angle classification | Relative first permanent molar relationship | Symptoms, guidance or treatment need by itself |
Class II division 2: relationship schematic
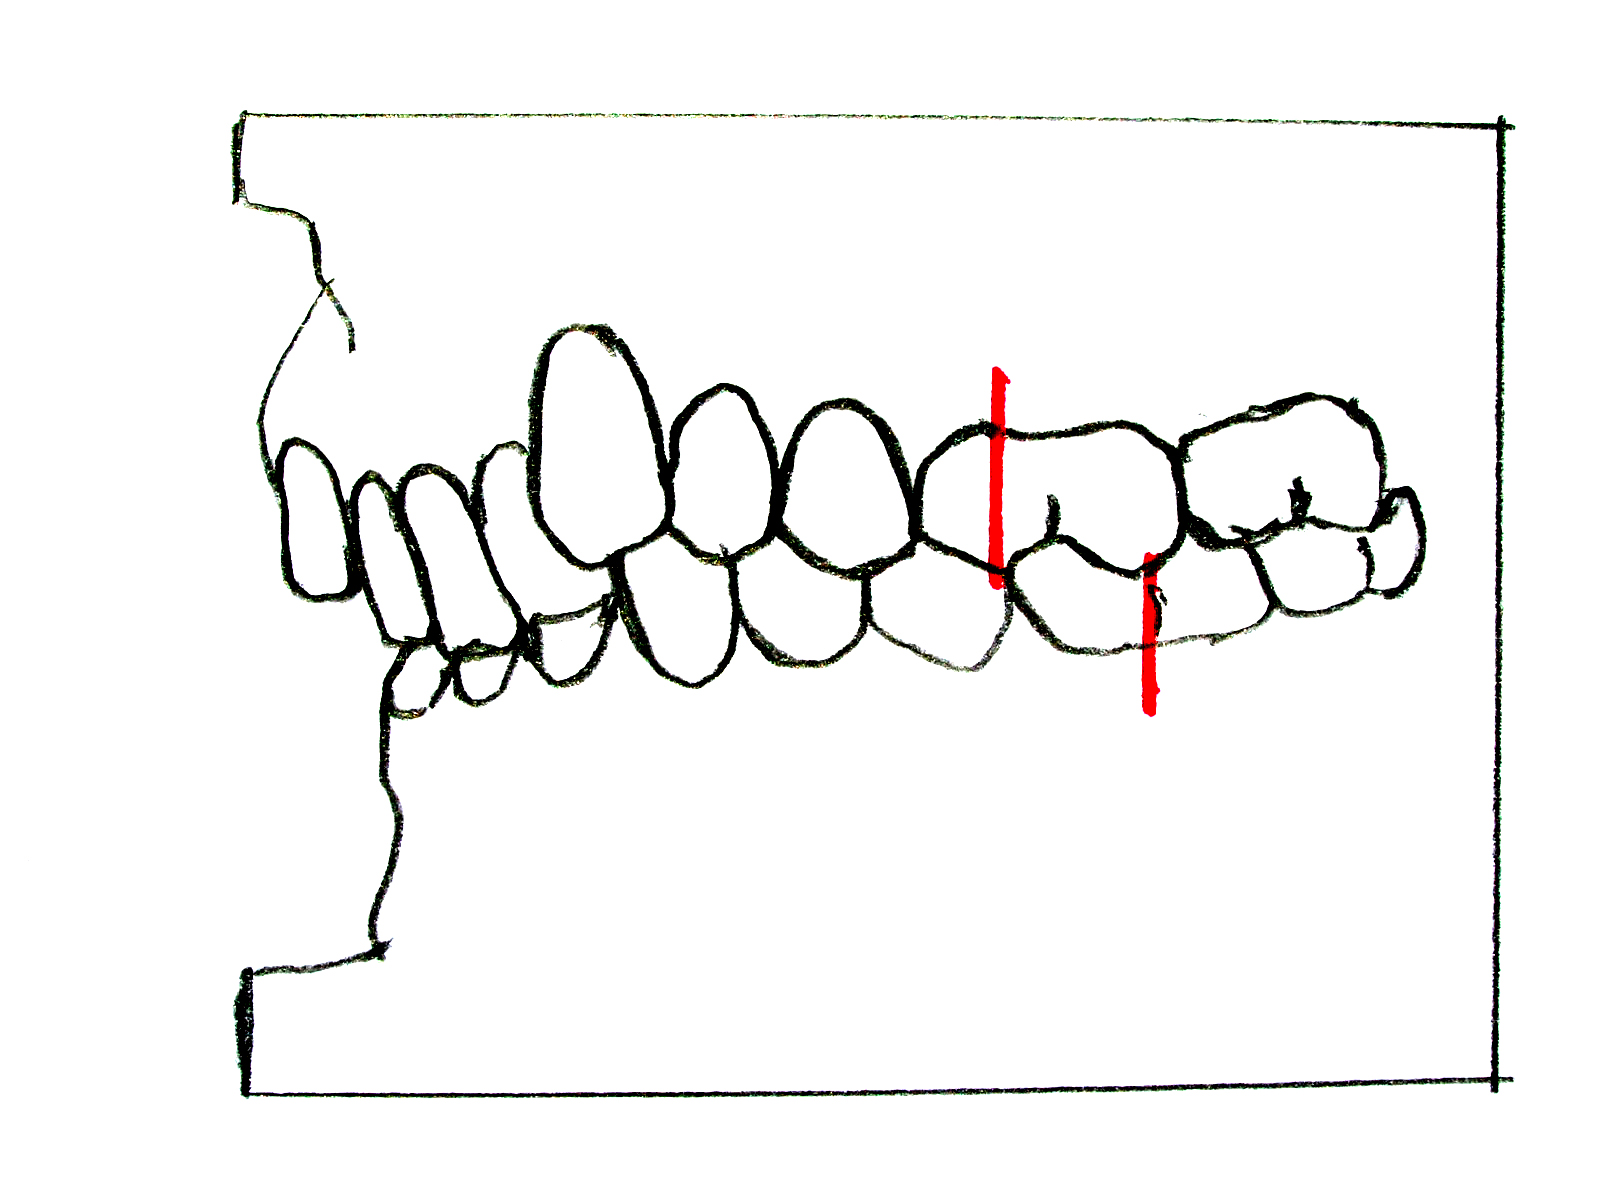
Identify the retroclined upper incisors and deep overlap, then compare the molar references with the division 1 schematic. A Class II molar relationship does not by itself specify the incisor division or establish the skeletal diagnosis.
Zahnfehlstellung Angle-Klasse II-2.jpg · Dr. Georg Risse · CC BY-SA 3.0. None; original image reproduced without alteration.
Does a Class II molar relationship alone tell you the incisor division?
No. Assess the upper central-incisor inclination and incisor relationship separately; document skeletal and soft-tissue findings as well.
Excursions, guidance and load
During a lateral excursion the side towards which the mandible moves is the working side; the opposite is non-working. Canine guidance and group function describe different patterns of working-side contacts. Protrusive guidance usually involves anterior teeth. Record the observed contacts and symptoms rather than assuming every person must have one identical scheme.
The consequences of a contact depend on the tooth’s support, direction of force and restoration. A small high contact on a new restoration may cause discomfort; a thin unsupported cusp may fracture under repeated load. Wear facets alone do not quantify current bruxism. Parafunction, mobility, fremitus, fracture history and patient symptoms should be assessed together before irreversible occlusal adjustment.
Class III: relationship schematic
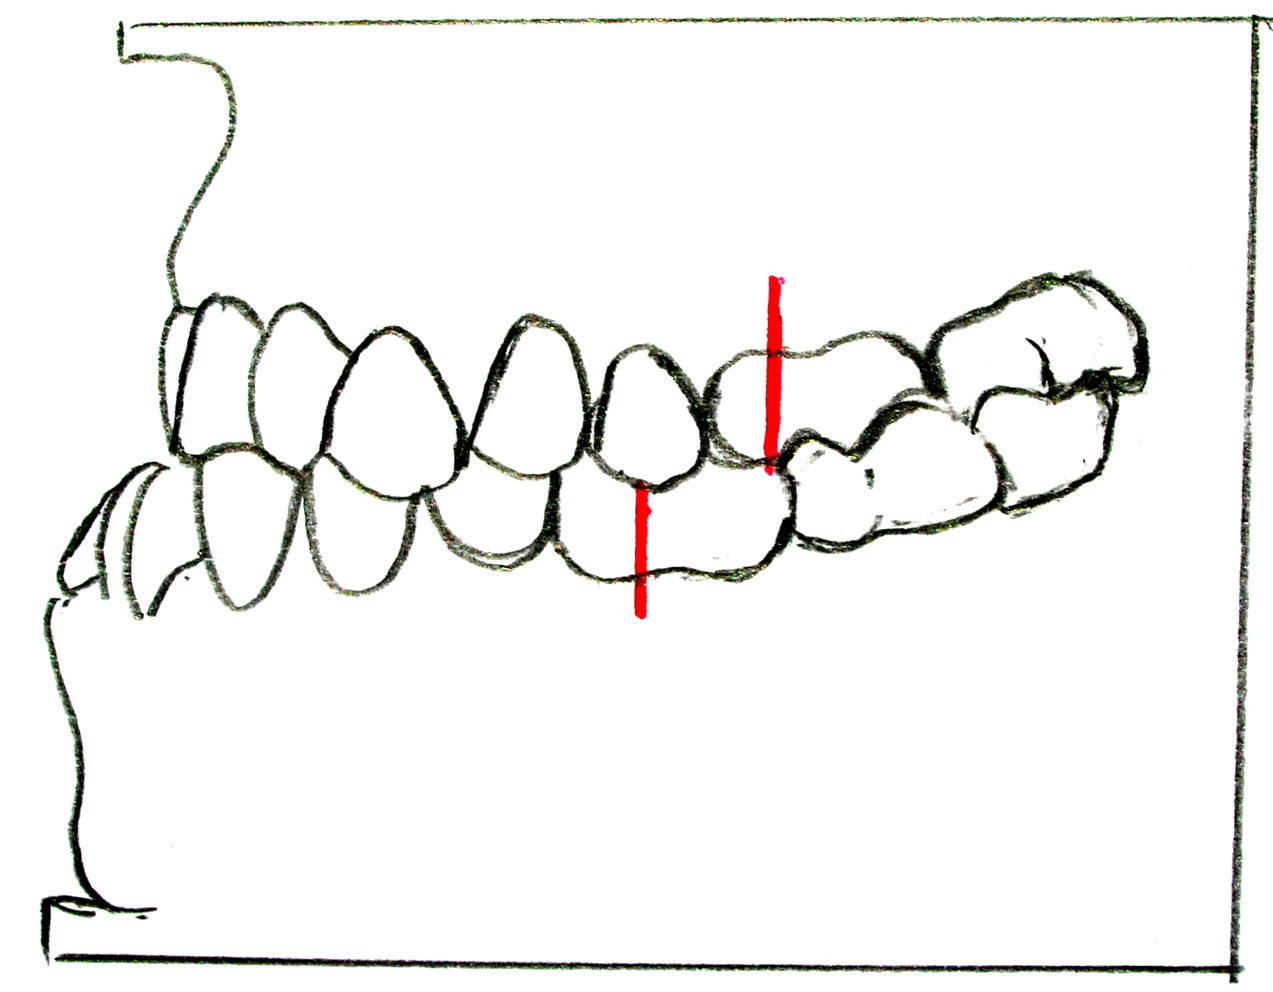
Compare the molar reference points with the Class II diagrams. The anterior relationship shown is a reverse overjet. A dental Class III relationship is not automatically proof of a skeletal Class III pattern: examine the facial profile and any functional displacement.
Zahnfehlstellung Angle-Klasse III.jpg · Dr. Georg Risse · CC BY-SA 3.0. None; original image reproduced without alteration.
Why assess the mandible on closure when a child has an anterior crossbite?
A functional forward displacement can create or exaggerate an apparent Class III relationship and influences diagnosis and referral.
Apply the anatomy to restorative planning
Before restoring a tooth, assess the remaining walls and cusps, the neighbouring contact and marginal ridge, opposing teeth and static and excursive space. A restoration must achieve a seal, maintainable contour and sufficient material thickness while preserving sound tissue. Reducing healthy tissue merely to reproduce an idealised anatomical drawing sacrifices the structure that supports the result.
After treatment check proximal contact, floss passage, contour and occlusion with appropriate clinical methods. Compare the patient’s comfortable closure and excursions before and after adjustment. A persistent problem may reflect a crack, pulp disease, periodontal support or an incorrect diagnosis; occlusion should be examined as one part of that assessment.
A distinction to remember
Root number, canal number and crown appearance are related but not interchangeable. A normal-looking crown cannot establish the anatomy hidden beneath it.
A restored lower molar has a firm contact but food repeatedly packs beside it. What anatomical checks are missing?
Reveal the reasoning
Assess contact location and breadth, marginal-ridge height, emergence profile, gingival embrasures and papillary support, as well as occlusion. A contact can feel tight to floss yet still direct food into an unsuitable contour or open gingival space.
Guidance to read alongside this chapter
Test your recall
Which permanent teeth replace primary molars?
Show answer
The permanent premolars replace primary molars. Permanent molars erupt distal to the primary dentition without replacing predecessors. This distinction helps identify first permanent molars in mixed dentition and explains why eruption can occur without a recent exfoliation.