
Interpretation and reporting
Separate observed features from the diagnosis you infer.
Quick revision summary
Separate observation, interpretation and action
Include the examination, clinical question, image adequacy and relevant findings. Describe lesion site, size, density, margins, internal structure and effects on teeth, cortices or nearby structures.
Build a report the next clinician can use
Begin with the examination and its adequacy for the question. Describe relevant findings using location and extent, border, internal appearance and effects on surrounding structures. “Radiolucency in the posterior mandible” is an observation; “likely odontogenic lesion” is an interpretation.
Communicate the significance and next step
An ill-defined destructive change, unexplained sensory symptoms or progressive abnormality may alter urgency even if the initial referral was routine. Explain how the imaging and clinical information fit together and use the relevant pathway.
Common mistake
A descriptive report needs a conclusion and an accountable next step when an abnormality remains unresolved.
A report should describe, interpret and direct
Separate observed features from the diagnosis you infer.
Separate observation, interpretation and action
Include the examination, clinical question, image adequacy and relevant findings. Describe lesion site, size, density, margins, internal structure and effects on teeth, cortices or nearby structures. A well-defined border can suggest slower growth but does not establish a benign histological diagnosis. Ill-defined destruction or unexpected change should prompt appropriate clinical correlation and escalation.
Give a reasoned differential where indicated and state limitations. The recommended next step should answer the remaining question: further clinical assessment, comparison, imaging, referral or tissue diagnosis through a suitable pathway. Ensure significant findings are communicated with the appropriate urgency. A report filed without an allocated action or discussed result can leave the patient’s problem unresolved.
Apical radiolucency around a premolar
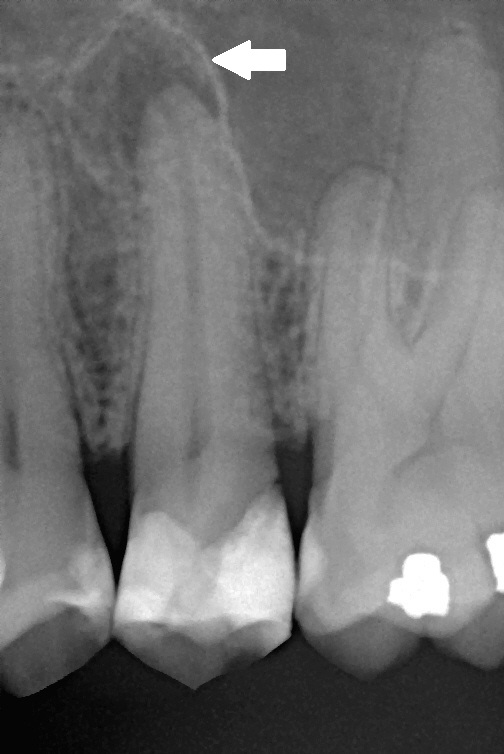
The original arrow marks the radiolucency described as apical periodontitis in the source. Relate this finding to symptoms and pulp tests rather than assigning a diagnosis from the shadow alone.
Chronic apical periodontitis.jpg · Michele Gardini; original arrow annotation by Lesion · CC BY-SA 3.0. Image reproduced without alteration; original marks and any embedded credits retained.
Panoramic anatomy with unerupted third molars
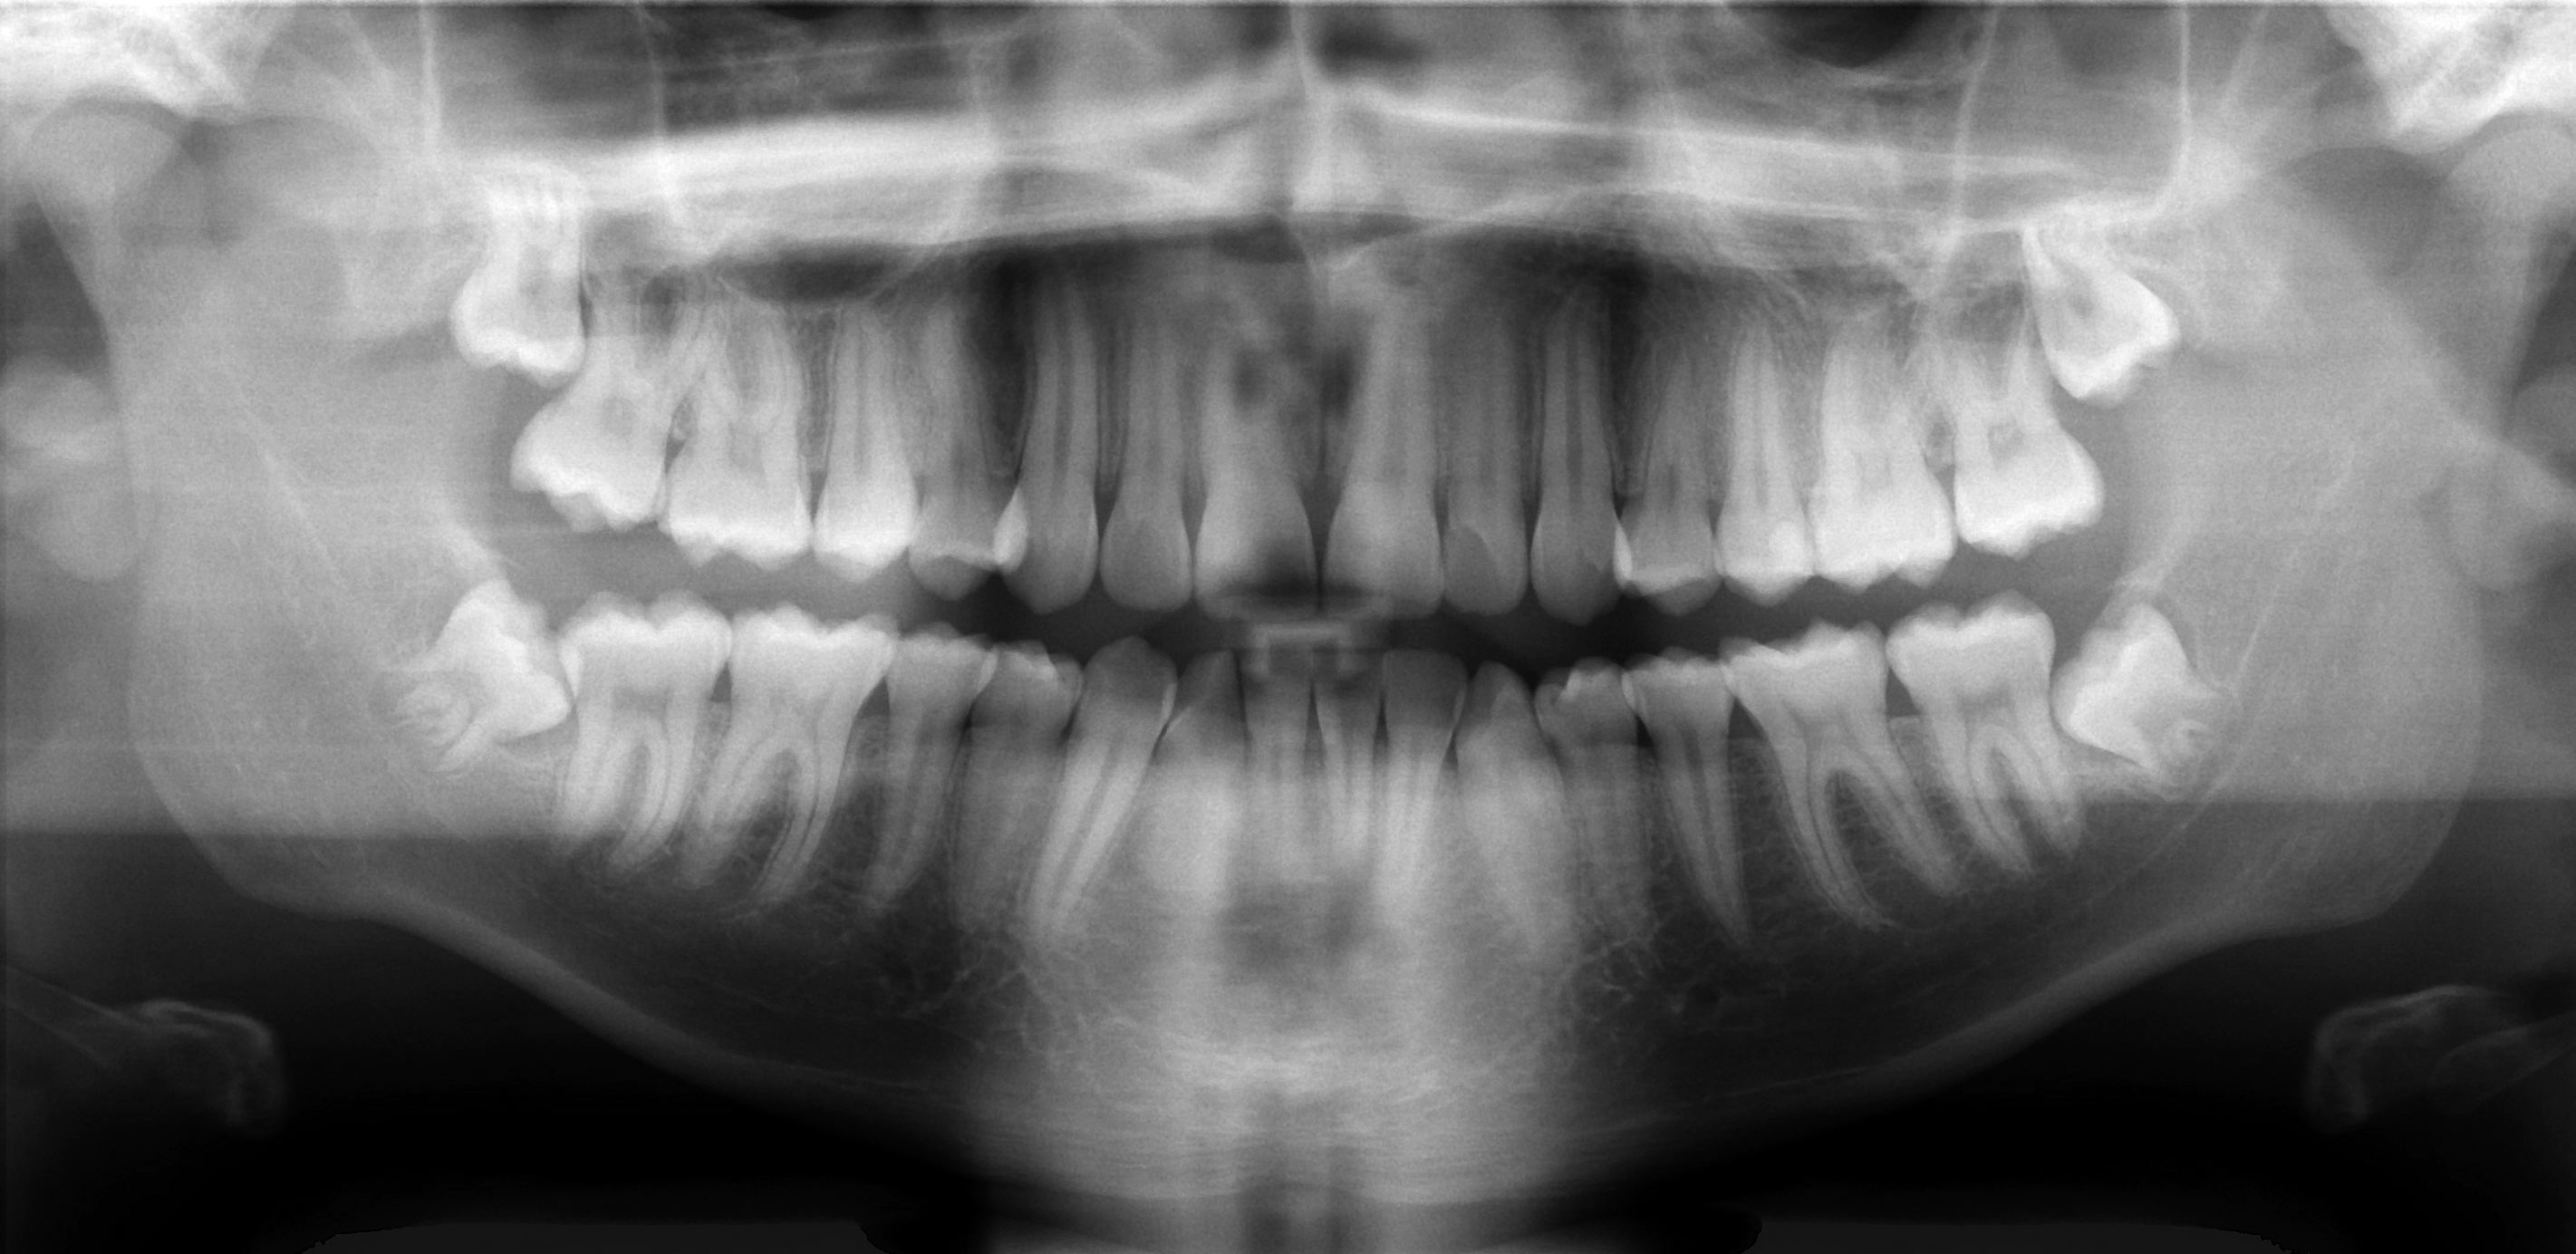
Scan the whole image systematically: compare both sides, trace the mandibular borders and canals, inspect the maxillary sinuses and count the teeth. This published example includes unerupted third molars; it is not an all-normal reference. Radiographic overlap alone cannot establish the three-dimensional nerve–root relationship.
Basic panoramic radiograph.jpg · Coronation Dental Specialty Group · CC BY 3.0. None; original image reproduced without alteration.
Can a panoramic image alone prove whether roots touch the inferior alveolar nerve?
No. It is a two-dimensional projection. Interpret the signs in clinical context, and request further imaging only when justified by a management question.
Key distinctions in practice
| Finding or option | What it means | Clinical consequence |
|---|---|---|
| Description | What the image actually shows | Use reproducible anatomical and radiographic terms. |
| Interpretation | What the pattern may mean | Keep confidence and differential explicit. |
| Limitation | What cannot be assessed reliably | Explain its effect on the decision. |
| Action | How the unresolved issue will be addressed | Allocate communication and follow-up responsibility. |
Dentigerous cyst: a pericoronal radiolucency
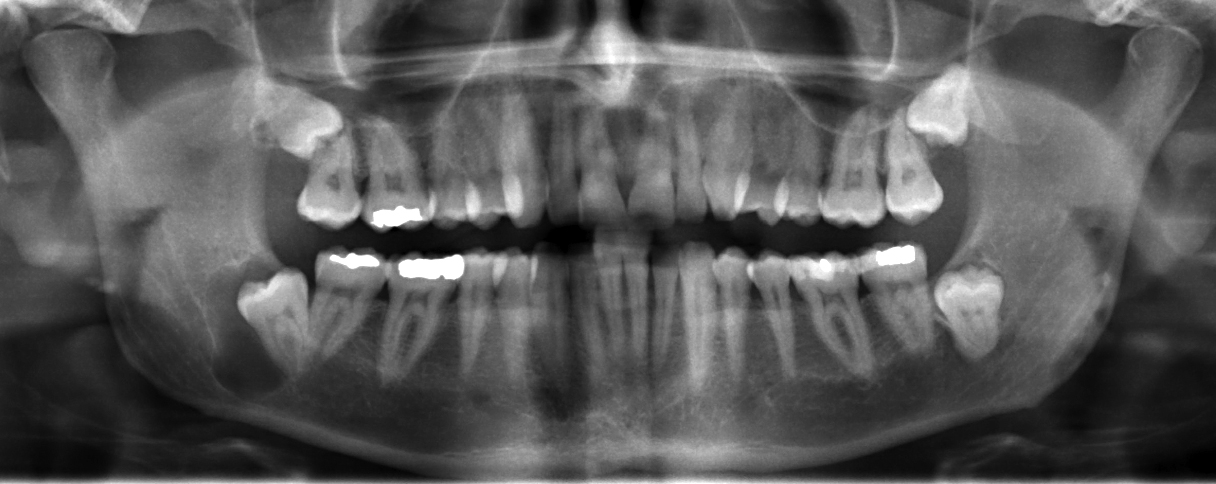
Locate the radiolucency associated with the impacted lower third molar on the left of the displayed image; the source describes a right mandibular dentigerous cyst. Assess its border and relationship to the crown, adjacent roots and mandibular canal. A pericoronal radiolucency supports a differential; imaging alone cannot establish the lining or exclude other odontogenic lesions.
JawCyst.jpg · Coronation Dental Specialty Group · CC BY 3.0. Source image reproduced without alteration; any arrows or circles are part of the original.
Which tooth relationship makes a dentigerous cyst an important consideration?
A radiolucency surrounding the crown of an unerupted tooth. An enlarged follicle and other odontogenic lesions can resemble it, so clinical, radiographic and appropriate histological findings must be correlated.
Build a report the next clinician can use
Begin with the examination and its adequacy for the question. Describe relevant findings using location and extent, border, internal appearance and effects on surrounding structures. “Radiolucency in the posterior mandible” is an observation; “likely odontogenic lesion” is an interpretation. Make that distinction explicit and avoid a histological label presented as certainty when imaging cannot establish it.
Give a concise conclusion that addresses the clinical question. If the image is normal within its limits, say which question has been answered and which has not. If a finding is indeterminate, offer a reasoned differential or recommend appropriate reporting input. A long list of unrelated possible diagnoses can obscure the finding that actually needs action.
Impacted third molar beside distal second-molar caries
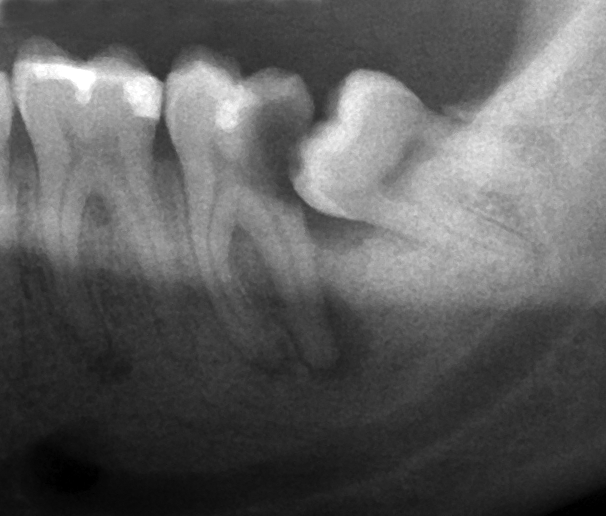
The source identifies caries on the second molar beside an impacted lower third molar. Describe the tooth positions and adjacent surface before deciding the clinical significance.
Wisdom tooth causing dental caries.png · Coronation Dental Specialty Group · CC BY-SA 3.0. Image reproduced without alteration; original marks and any embedded credits retained.
Odontogenic keratocyst: a posterior mandibular example
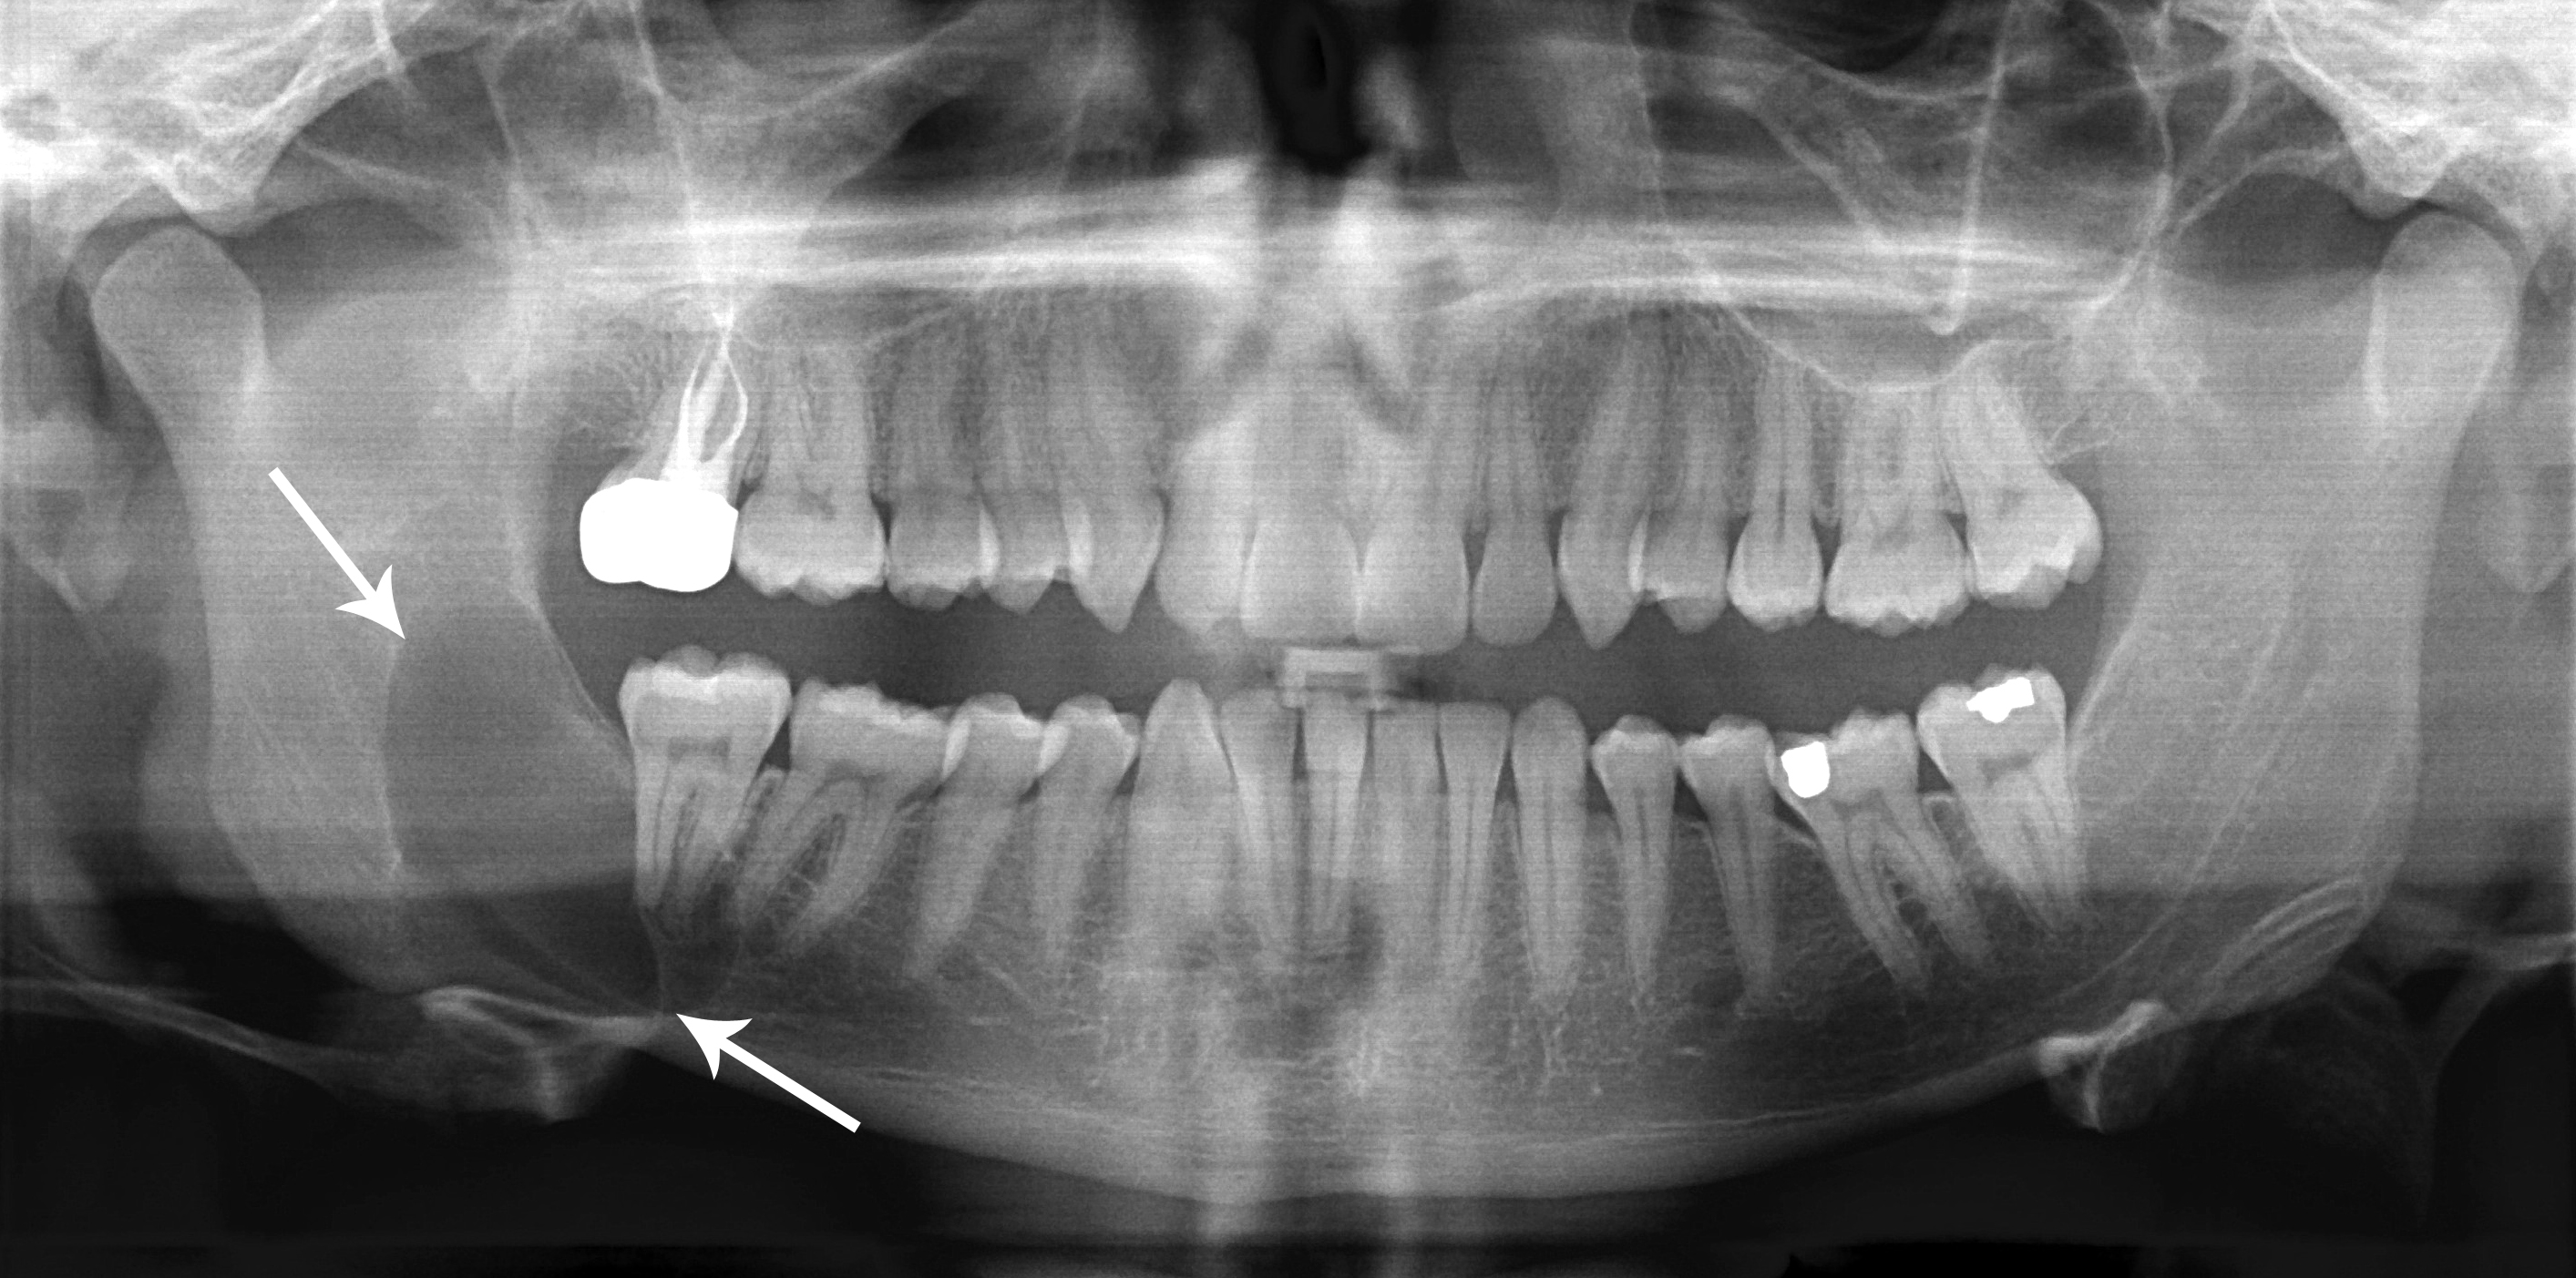
Use the original arrows to locate the posterior mandibular radiolucency and inspect its extent. The source diagnosis is an odontogenic keratocyst, described under the historical name “keratocystic odontogenic tumour”. Its relatively well-defined appearance does not make follow-up unnecessary. Other jaw lesions can look similar; definitive classification requires correlation with tissue findings.
Classic_keratocystic_odontogenic_tumour.jpg · Coronation Dental Specialty Group · CC BY 3.0. Source image reproduced without alteration; any arrows or circles are part of the original.
Can the relatively well-defined border distinguish this keratocyst from every other odontogenic cyst?
No. Borders and location help rank possibilities but overlap between lesions. The source diagnosis is supplied for teaching; it cannot be independently established from this panoramic image alone.
Communicate the significance and next step
An ill-defined destructive change, unexplained sensory symptoms or progressive abnormality may alter urgency even if the initial referral was routine. Explain how the imaging and clinical information fit together and use the relevant pathway. A written report is not enough when an urgent concern requires direct communication.
Document who receives the report and who will arrange any comparison, further imaging, examination or referral. An incidental finding needs a proportionate plan, not automatic escalation of every variation. When imaging and clinical suspicion disagree, reassess both. A technically reassuring image cannot exclude all mucosal disease or replace tissue assessment where the clinical findings require it.
Nasopalatine duct cyst: an anterior maxillary example
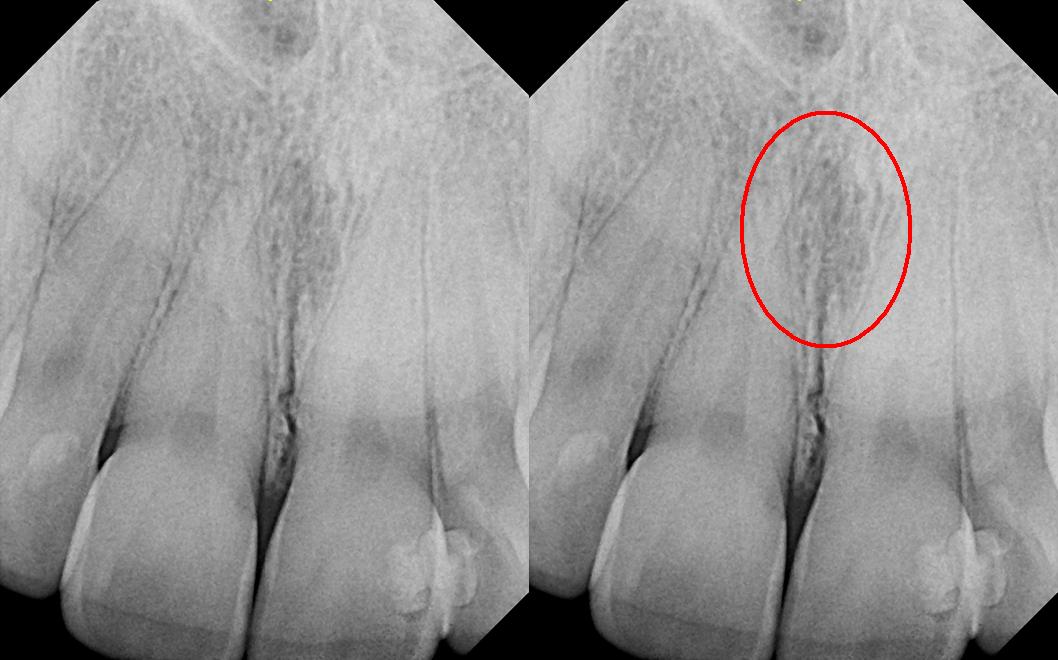
The right panel repeats the image with the source’s red circle highlighting the midline region. The source explicitly corrects its filename: this is reported as a nasopalatine duct cyst, not a nasolabial cyst. Consider the incisive canal and adjacent incisors, including pulp tests. The subtle appearance illustrates why a labelled example is not a stand-alone diagnostic rule.
Nasolabial_duct_cyst.JPG · DRosenbach · CC BY-SA 3.0. Source image reproduced without alteration; any arrows or circles are part of the original.
Why assess the adjacent incisors before treating a midline anterior maxillary radiolucency as endodontic disease?
A nasopalatine duct cyst or normal incisive-canal anatomy may overlap the incisor roots. Clinical examination, pulp tests and appropriate imaging help avoid unnecessary endodontic treatment of otherwise healthy teeth.
Periapical sclerosis: compare four patterns
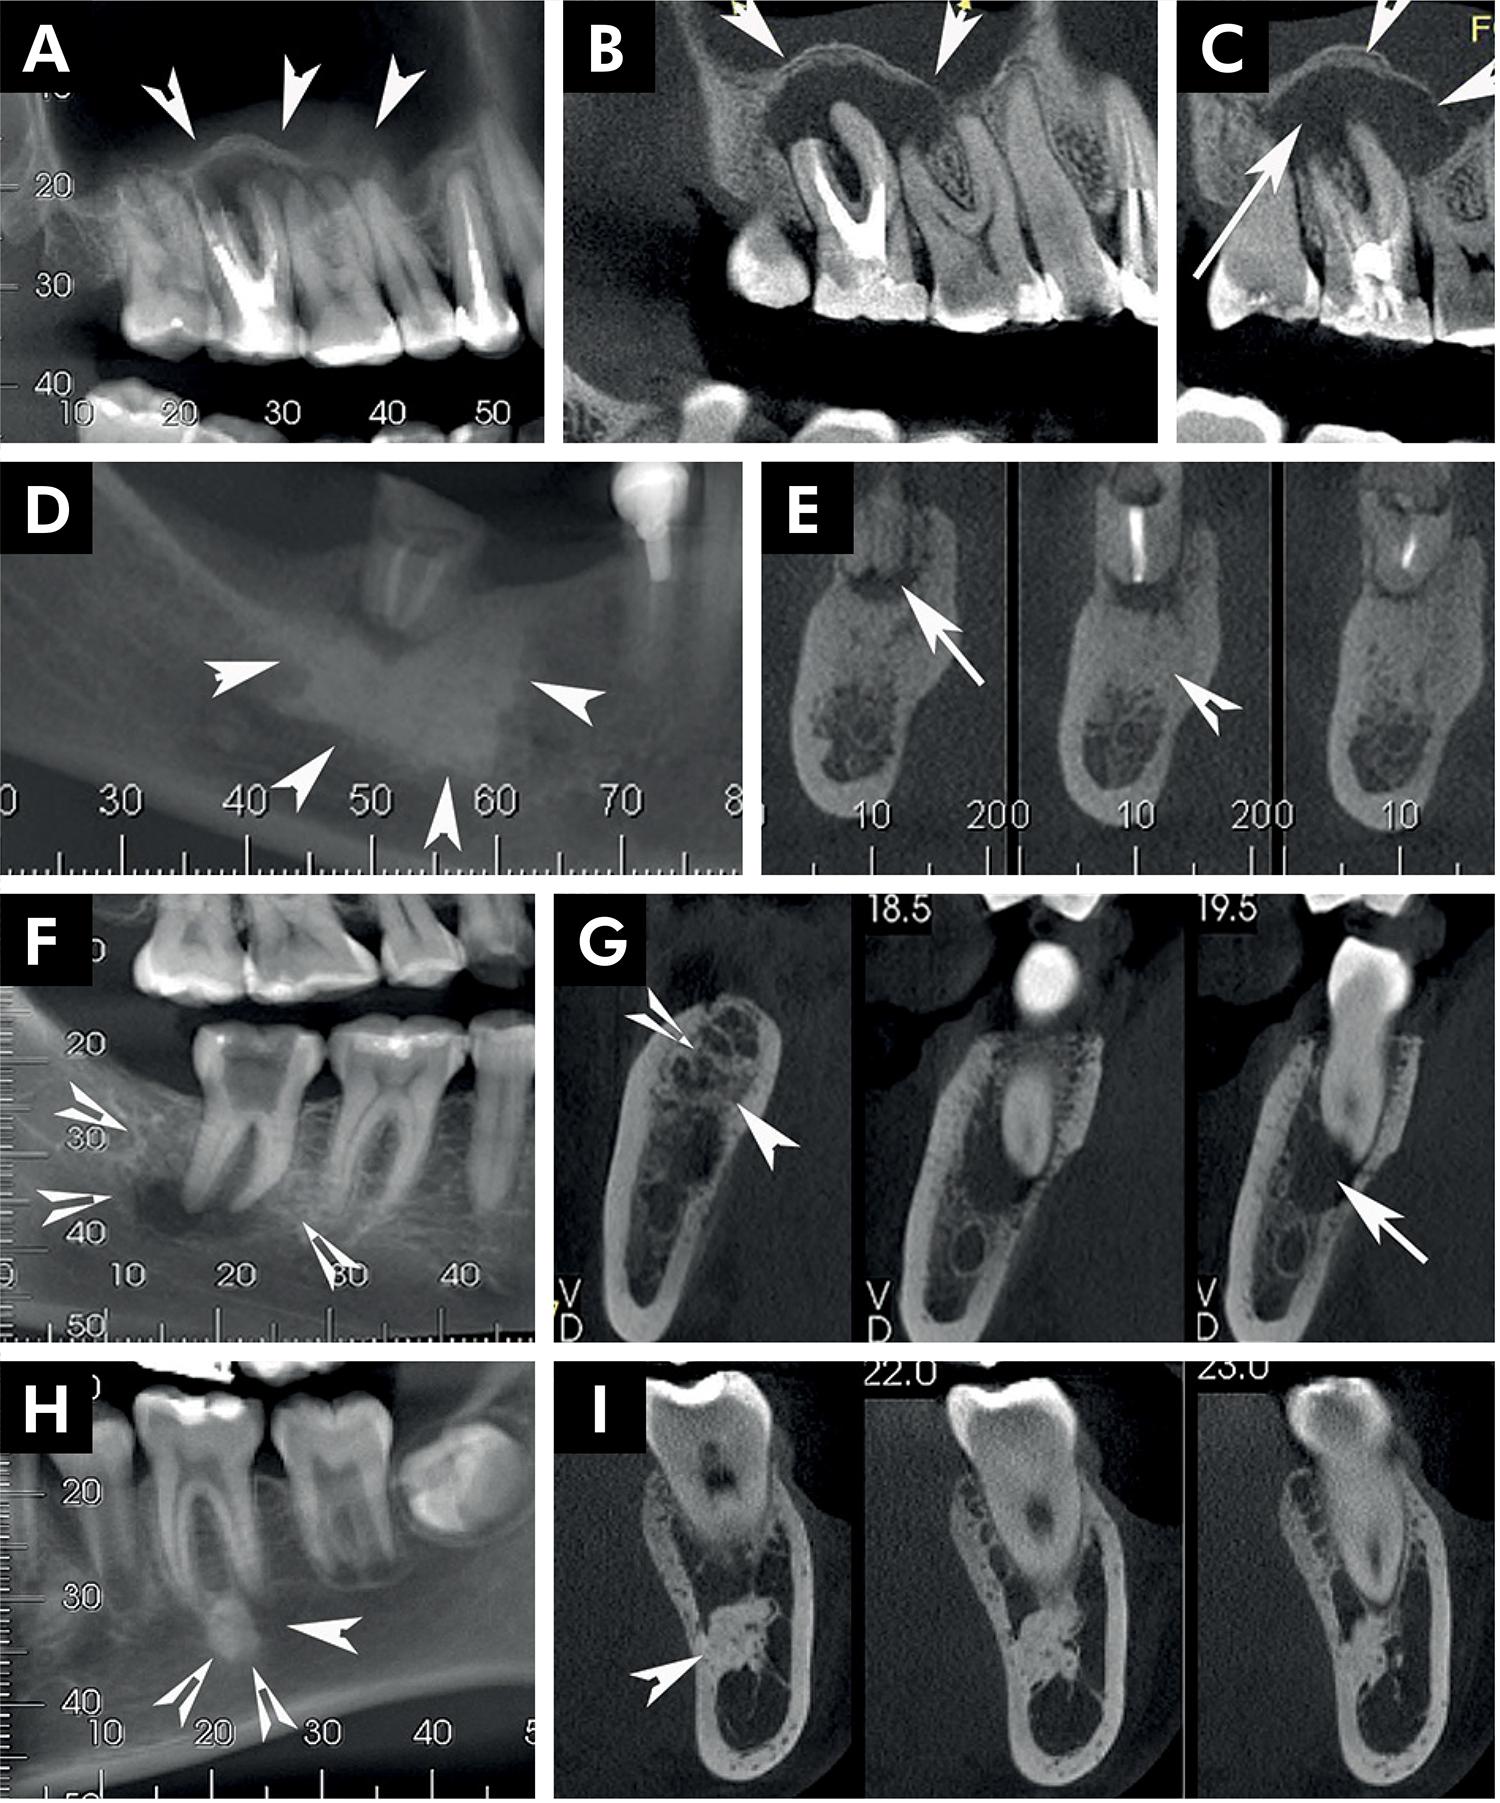
Compare the source diagnoses below. Tooth findings and lesion distribution help interpret the opacity.
Panel key
- A–C
- Reactive bone associated with inflammatory change.
- D–E
- Condensing osteitis.
- F–G
- Chronic osteomyelitis.
- H–I
- Idiopathic osteosclerosis.
Periapical radiopaque-hyperdense jaw lesions 1.jpg · Brunno Santos Freitas Silva, Mike Reis Bueno, Fernanda P. Yamamoto-Silva, Ricardo Santiago Gomez, Ove Andreas Peters and Carlos Estrela · CC BY 4.0. Reproduced without alteration. Labels, arrows and circles, where present, belong to the source image. Original publication.
Does periapical opacity alone establish an endodontic diagnosis?
No. Correlate it with tooth assessment and the broader pattern.
Cemento-osseous dysplasia: localised and florid examples
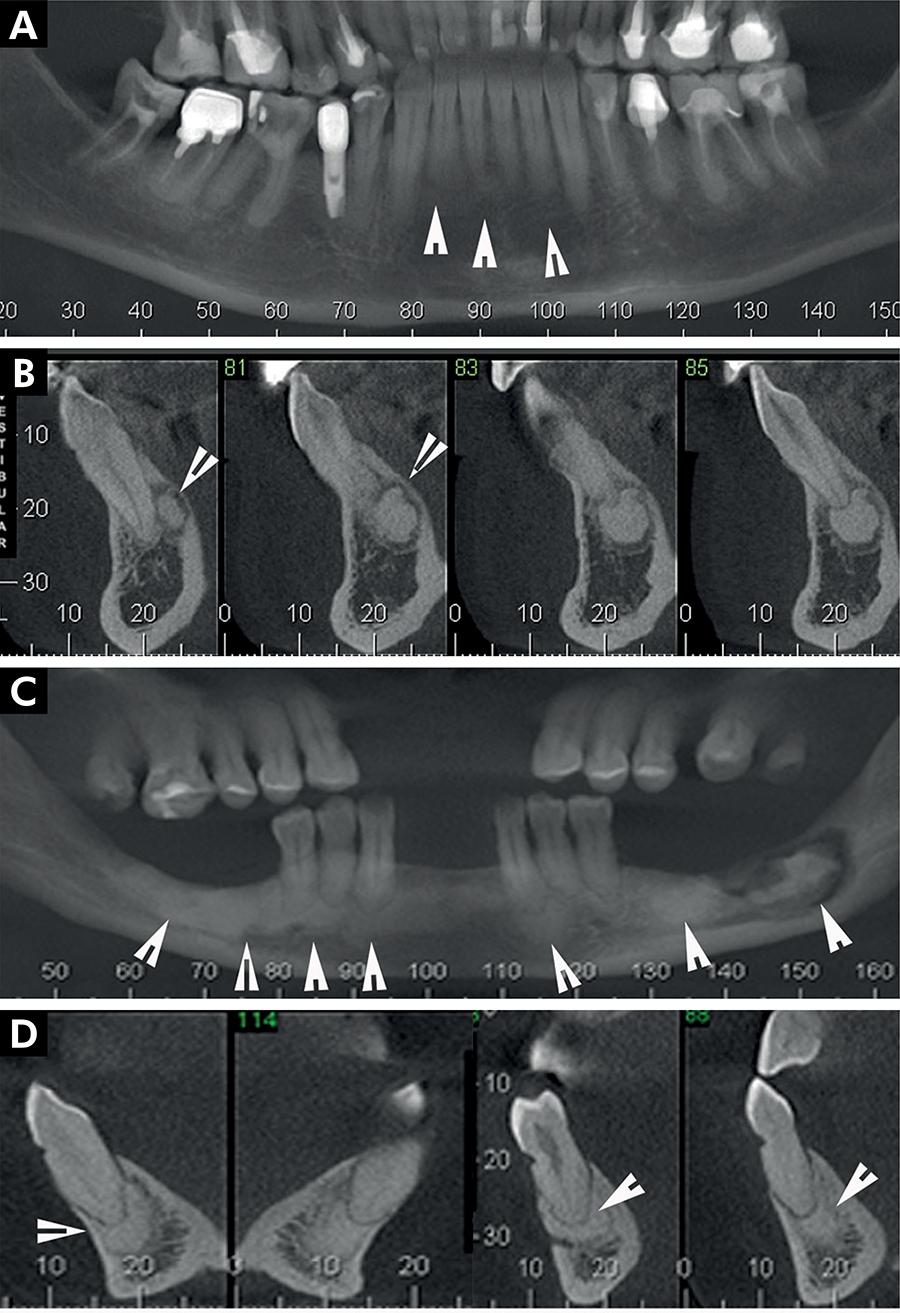
Compare the distribution and separation from roots in the source examples.
Panel key
- A–B
- Periapical cemento-osseous dysplasia.
- C–D
- Florid cemento-osseous dysplasia; the source also describes sequestration in C.
Periapical radiopaque-hyperdense jaw lesions 2.jpg · Brunno Santos Freitas Silva, Mike Reis Bueno, Fernanda P. Yamamoto-Silva, Ricardo Santiago Gomez, Ove Andreas Peters and Carlos Estrela · CC BY 4.0. Reproduced without alteration. Labels, arrows and circles, where present, belong to the source image. Original publication.
Why assess the teeth before attributing these findings to pulp disease?
The imaging distribution may have a non-endodontic explanation.
Fibrous dysplasia, osteoma and cementoblastoma
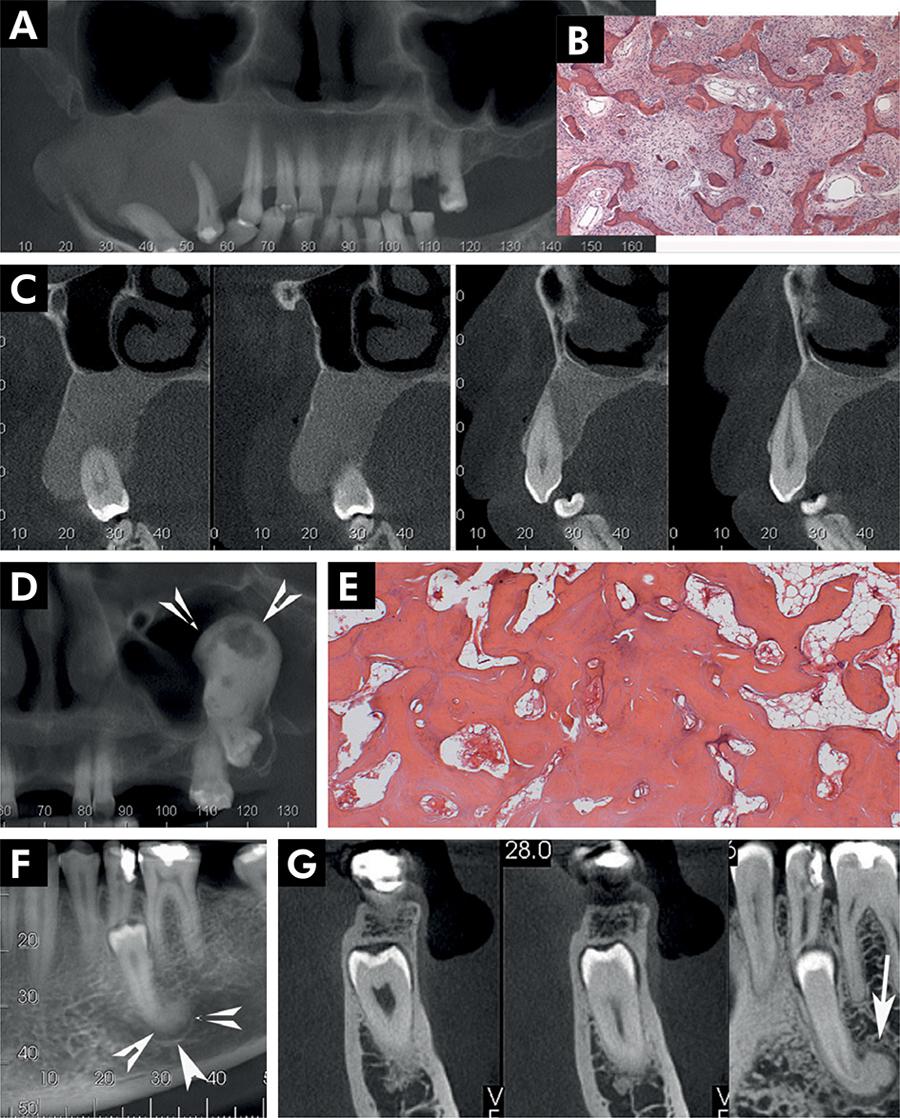
Compare the margins and root relationships of these source cases.
Panel key
- A–C
- Fibrous dysplasia.
- D–E
- Central osteoma.
- F–G
- Cementoblastoma.
Periapical radiopaque-hyperdense jaw lesions 3.jpg · Brunno Santos Freitas Silva, Mike Reis Bueno, Fernanda P. Yamamoto-Silva, Ricardo Santiago Gomez, Ove Andreas Peters and Carlos Estrela · CC BY 4.0. Reproduced without alteration. Labels, arrows and circles, where present, belong to the source image. Original publication.
Which relationship deserves attention in the cementoblastoma panels?
The lesion’s attachment to the root.
Odontomas and other calcified jaw lesions
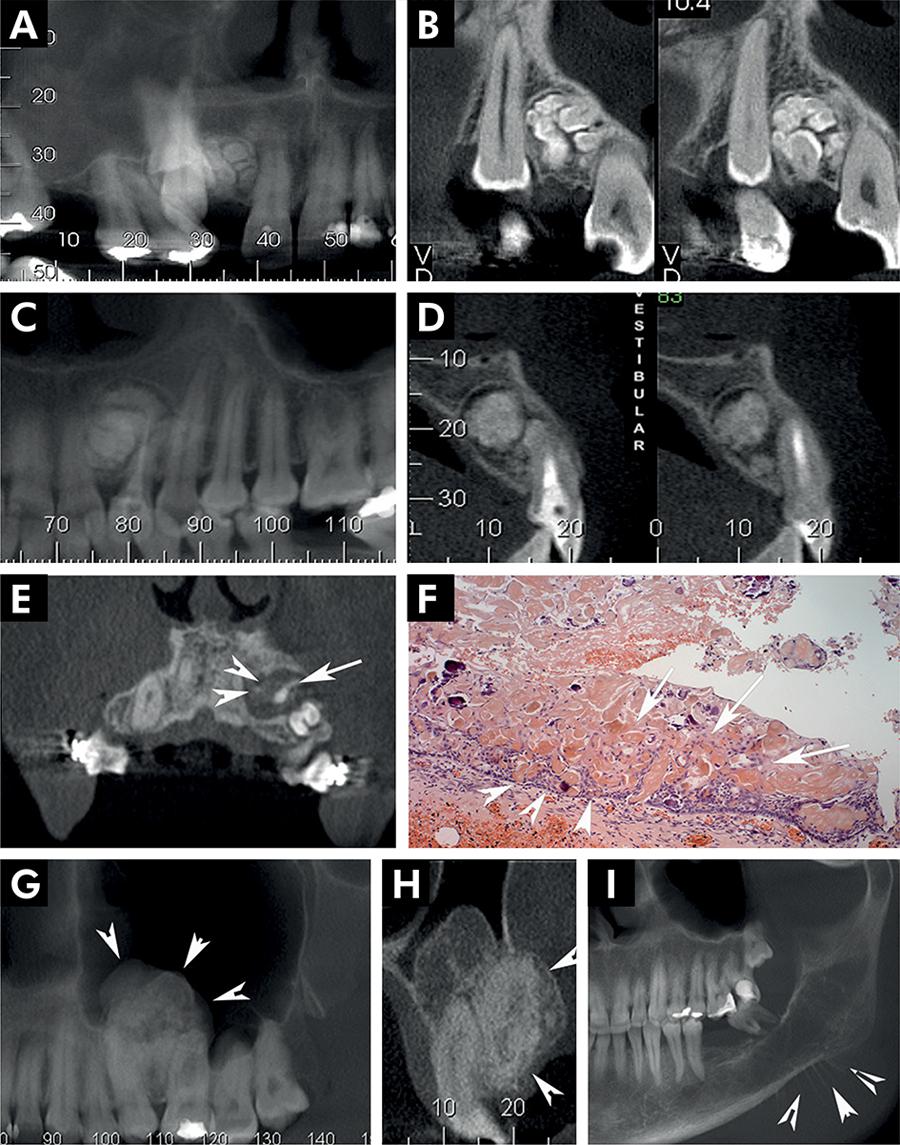
Use the panel key to compare the source diagnoses. The historical label CCOT corresponds here to calcifying odontogenic cyst.
Panel key
- A–B
- Compound odontoma.
- C–D
- Complex odontoma.
- E–F
- Calcifying odontogenic cyst (source label: CCOT).
- G–H
- Adenomatoid odontogenic tumour.
- I
- Source example of osteosarcoma.
Periapical radiopaque-hyperdense jaw lesions 4.jpg · Brunno Santos Freitas Silva, Mike Reis Bueno, Fernanda P. Yamamoto-Silva, Ricardo Santiago Gomez, Ove Andreas Peters and Carlos Estrela · CC BY 4.0. Reproduced without alteration. Labels, arrows and circles, where present, belong to the source image. Original publication.
Does calcification establish benignity?
No. Compare the entire lesion and clinical findings.
A distinction to remember
A descriptive report needs a conclusion and an accountable next step when an abnormality remains unresolved.
Does a corticated radiolucency establish the histological diagnosis of a cyst?
Reveal the reasoning
No. The pattern supports a differential but several lesions can resemble each other. Correlate clinically and use the appropriate diagnostic pathway.
Guidance to read alongside this chapter
Test your recall
What should happen with an incidental abnormality?
Show answer
Assess its significance and document any follow-up or referral.