
Malocclusion assessment
Describe the malocclusion in three dimensions before choosing a device or assigning an index score. The assessment should explain the patient’s concern, the cause of the relationship and the limits of correction.
Quick revision summary
Describe every plane of the bite
Assess sagittal, vertical and transverse relationships, overjet, overbite, crossbites, centre lines and crowding. Include the facial and skeletal pattern so the description explains the problem rather than listing tooth positions.
Look for a functional displacement
Compare the initial contact with the habitual bite where appropriate. A crossbite with a mandibular shift has different implications from a purely dental irregularity, and the movement should be recorded clearly.
Connect findings to the patient’s concern
Ask about appearance, function, trauma risk and expectations. Dental health, soft tissues and treatment burden affect suitability; an occlusal classification by itself does not select an appliance or establish eligibility.
Common mistake
Class II describes more than one relationship. Specify incisor, molar and skeletal findings rather than using the label as a complete diagnosis.
Malocclusion assessment
Describe the malocclusion in three dimensions before choosing a device or assigning an index score. The assessment should explain the patient’s concern, the cause of the relationship and the limits of correction.
Start with goals, history and facial assessment
Ask what the patient wants changed, whether there are functional difficulties and what commitment they can accept. Include growth, habits, trauma, dental treatment, missing teeth, family pattern and medical history. A technically visible irregularity may not be the concern that matters most to the patient.
Examine facial symmetry, profile, lip competence at rest, incisor display and vertical proportions. Assess possible jaw discrepancy and mandibular shifts rather than treating facial appearance as an exact skeletal measurement. A functional shift can make an apparent Class III or unilateral asymmetry look more skeletal than it is. Compare the resting face with the way the teeth meet.
Overjet and overbite
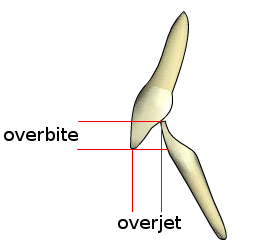
Overjet describes the horizontal relationship between the incisors; overbite describes their vertical overlap. Record the magnitude, direction and whether the overbite is complete or incomplete. The schematic is not drawn to a clinical measurement scale.
Overjet-overbite.png · Nielson2000 · CC BY-SA 3.0. None; original image reproduced without alteration.
Which measurement is horizontal: overjet or overbite?
Overjet is horizontal. Overbite is the vertical overlap of the incisors.
Describe the incisor relationship precisely
Class I describes lower incisor edges occluding on or immediately below the upper incisor cingulum region. In Class II they lie posteriorly: division 1 usually has proclined or normally inclined upper incisors and increased overjet; division 2 has retroclined upper central incisors, often with a deep overbite. Class III places the lower incisor edges anterior to the upper cingulum region.
Measure overjet horizontally, parallel to the occlusal plane, and overbite vertically, recording a millimetre or percentage description consistently. Note whether a deep bite is complete or causes palatal or labial trauma. A large overjet is not the same as a deep overbite, and a reverse overjet should be recorded with its actual extent and functional effects.
Class II division 1: relationship schematic
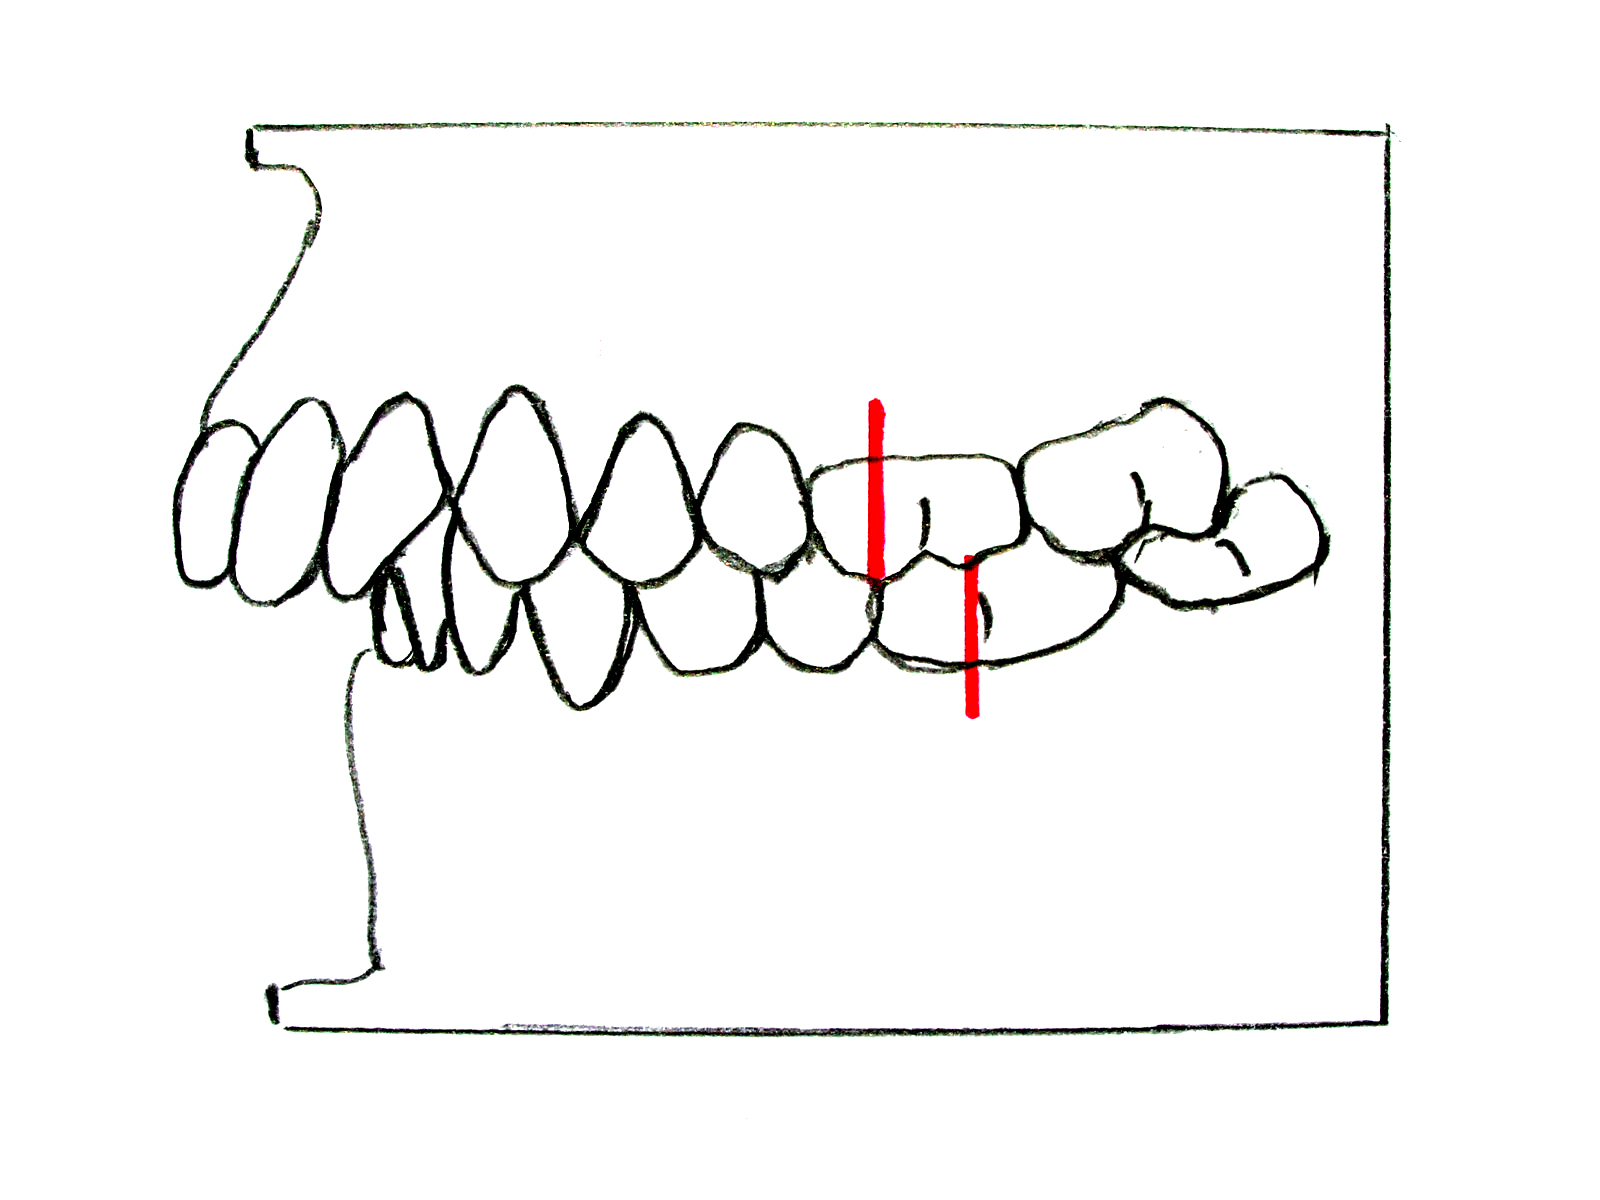
Compare the posterior molar relationship with the upper-incisor inclination and increased overjet. The red reference marks demonstrate the Class II molar relationship. Describe the incisor relationship separately from the molar and skeletal relationships in a clinical assessment.
Zahnfehlstellung Angle-Klasse II-1.jpg · Dr. Georg Risse · CC BY-SA 3.0. None; original image reproduced without alteration.
What upper-incisor feature typically distinguishes Class II division 1 from division 2?
Division 1 usually has proclined or normally inclined upper incisors with increased overjet; division 2 has retroclined upper central incisors.
Record the buccal segments and transverse relationship
Describe molar and canine relationships separately on each side. A Class I molar relationship places the upper first-molar mesiobuccal cusp near the lower first-molar buccal groove; Class II and III relationships shift this relationship distally or mesially from the lower arch’s perspective. Tooth loss and migration can obscure the original pattern.
Record anterior and posterior crossbites, the teeth involved and whether the jaw displaces between initial contact and maximum intercuspation. A unilateral posterior crossbite can reflect bilateral narrowing plus a shift. A scissors bite is a different transverse relationship, with upper posterior teeth lying wholly buccal to the lower teeth; identify it rather than calling every transverse discrepancy a crossbite.
Class II division 2: relationship schematic
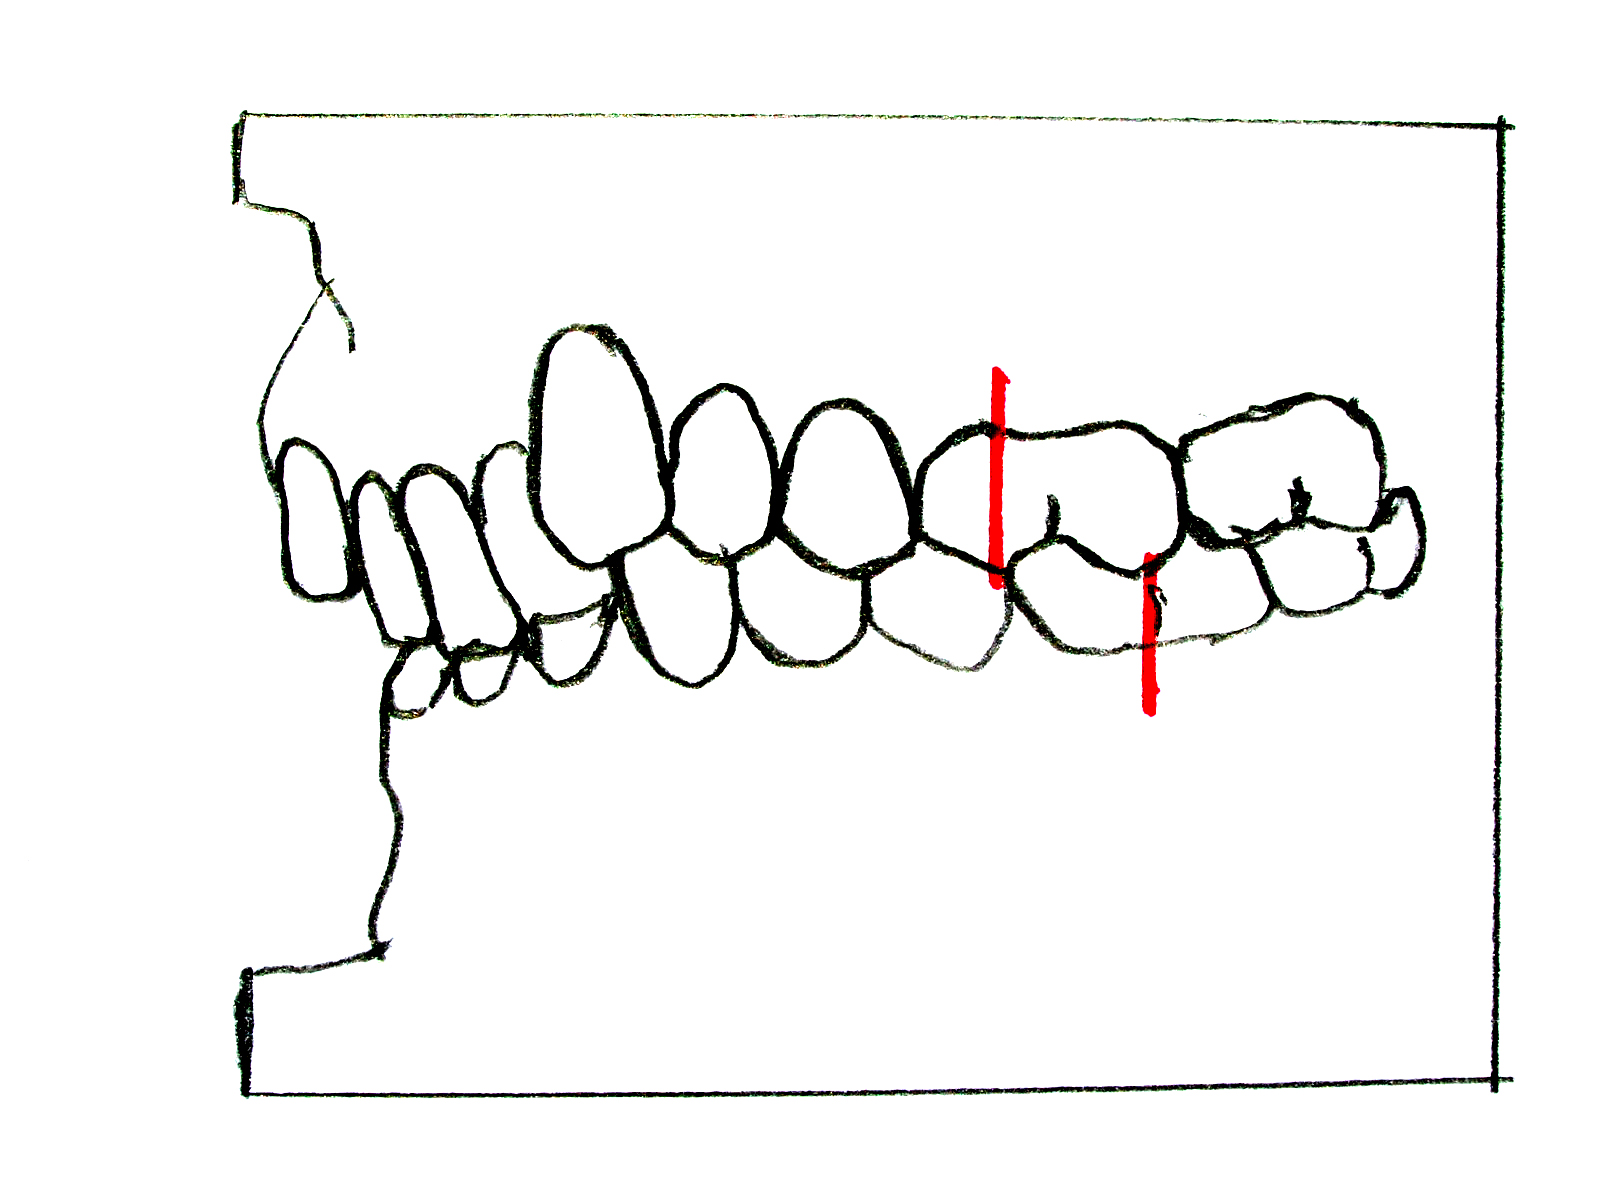
Identify the retroclined upper incisors and deep overlap, then compare the molar references with the division 1 schematic. A Class II molar relationship does not by itself specify the incisor division or establish the skeletal diagnosis.
Zahnfehlstellung Angle-Klasse II-2.jpg · Dr. Georg Risse · CC BY-SA 3.0. None; original image reproduced without alteration.
Does a Class II molar relationship alone tell you the incisor division?
No. Assess the upper central-incisor inclination and incisor relationship separately; document skeletal and soft-tissue findings as well.
Assess space, tooth identity and eruption
Count teeth and identify congenitally absent, previously removed, retained primary, ectopic and supernumerary teeth. Measure arch space and contact-point displacement rather than estimating crowding from a smile alone. An upper canine outside the arch may reflect space loss, ectopia or a wider developmental issue. Palpate unerupted canine regions at the appropriate stage.
Record centrelines relative to each other and the face. Look for tooth-size discrepancies, rotations, spacing and the curve of Spee. A centreline discrepancy can arise from asymmetric tooth loss or a functional shift as well as a skeletal asymmetry. Explain the cause before planning space closure or extractions.
Class III: relationship schematic
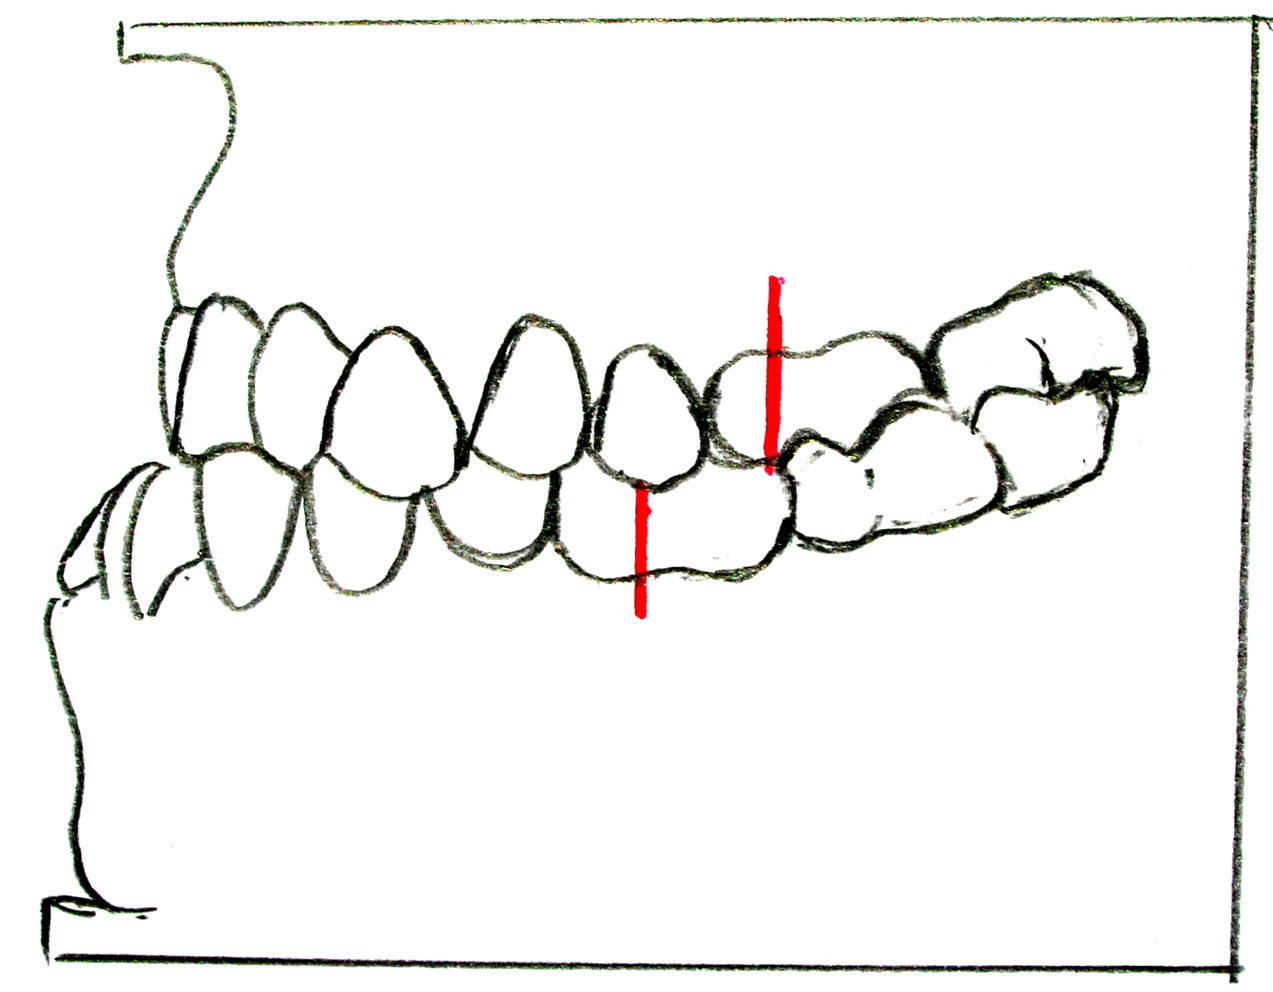
Compare the molar reference points with the Class II diagrams. The anterior relationship shown is a reverse overjet. A dental Class III relationship is not automatically proof of a skeletal Class III pattern: examine the facial profile and any functional displacement.
Zahnfehlstellung Angle-Klasse III.jpg · Dr. Georg Risse · CC BY-SA 3.0. None; original image reproduced without alteration.
Why assess the mandible on closure when a child has an anterior crossbite?
A functional forward displacement can create or exaggerate an apparent Class III relationship and influences diagnosis and referral.
Check biological readiness and relevant risks
Assess plaque, caries, white-spot lesions, gingival inflammation, periodontal support, recession, restorations and trauma-related problems. Tooth movement through a thin or compromised periodontal envelope can increase risk. Record root morphology and previous resorption where justified images are available. The need for treatment does not make uncontrolled disease compatible with active appliances.
Evaluate oral habits, mouth closure and potential contributing functional factors, without diagnosing an airway disorder from facial shape alone. Orthodontics should not be sold as a universal treatment for temporomandibular pain. Refer or investigate specific medical or functional concerns through an appropriate pathway rather than attaching unsupported causal explanations to malocclusion.
Produce a problem list and useful referral
Summarise skeletal pattern, incisor and buccal-segment relationships, vertical and transverse issues, crowding/spacing, eruption and dental-health risks. Identify time-sensitive features such as displacement, delayed incisors or an ectopic canine near roots. Records and radiographs should answer a clinical question; full imaging is not mandatory merely to make a referral.
Describe findings accurately if you are not calibrated in IOTN, and let the receiving clinician make the formal assessment. Explain alternatives, including observation, limited correction and comprehensive treatment where relevant. A problem list should connect the proposed benefit to the patient’s priorities and the level of treatment required, with no guarantee that a particular appliance can achieve every goal.
A distinction to remember
Class II describes more than one relationship. Specify incisor, molar and skeletal findings rather than using the label as a complete diagnosis.
A patient has a reverse overjet in their habitual bite but can guide back to an edge-to-edge contact. What does that suggest?
Reveal the reasoning
A functional mandibular shift may contribute to the apparent Class III relationship. Assess the first contact, displacement and skeletal pattern, and refer in a timely manner if developing. The finding does not by itself exclude a skeletal Class III component.
Test your recall
What is the difference between overjet and overbite?
Show answer
Overjet is the horizontal incisor relationship; overbite is the vertical overlap. Measure and describe them separately. A patient can have a large overjet with a shallow, normal or deep overbite, so one cannot be inferred from the other.