
Growth and dental development
Orthodontic timing depends on dental development, facial growth and the problem being treated. A chronological birthday is a poor substitute for examining the dentition and following change over time.
Quick revision summary
Distinguish growth from tooth movement
Skeletal growth, eruption and dentoalveolar adaptation all change the bite. A patient’s age alone does not establish remaining growth or predict the amount of correction achievable with an appliance.
Compare patterns over time
Assess facial proportions, dental development, eruption symmetry and occlusal relationships together. Records and previous observations help distinguish variation from a developing problem that needs timely specialist assessment or interception.
Refer while options remain available
Some developing problems benefit from assessment before the full permanent dentition erupts. Recognise displaced canines, functional shifts and compromised molars early, while avoiding unnecessary treatment of normal transient developmental features.
Common mistake
Functional appliances are not a guarantee of a permanently larger lower jaw. Explain expected dental effects, growth limitations and possible later treatment.
Growth and dental development
Orthodontic timing depends on dental development, facial growth and the problem being treated. A chronological birthday is a poor substitute for examining the dentition and following change over time.
Separate growth from tooth movement
Facial growth changes the size and relationship of the jaws through sutural growth, surface remodelling and displacement. Mandibular growth includes condylar growth and remodelling of the ramus and body. Rotation can alter the chin position and vertical facial proportions. Tooth eruption and alveolar development adapt the occlusion to these changes.
Orthodontic tooth movement remodels periodontal and alveolar tissues; it does not reproduce all effects of skeletal growth. A dental Class II incisor relationship can arise from tooth inclination, jaw discrepancy or both. Recognising the mechanism matters when comparing dentoalveolar correction, growth-related treatment and eventual orthognathic surgery.
Tooth development: cap, bell and root formation
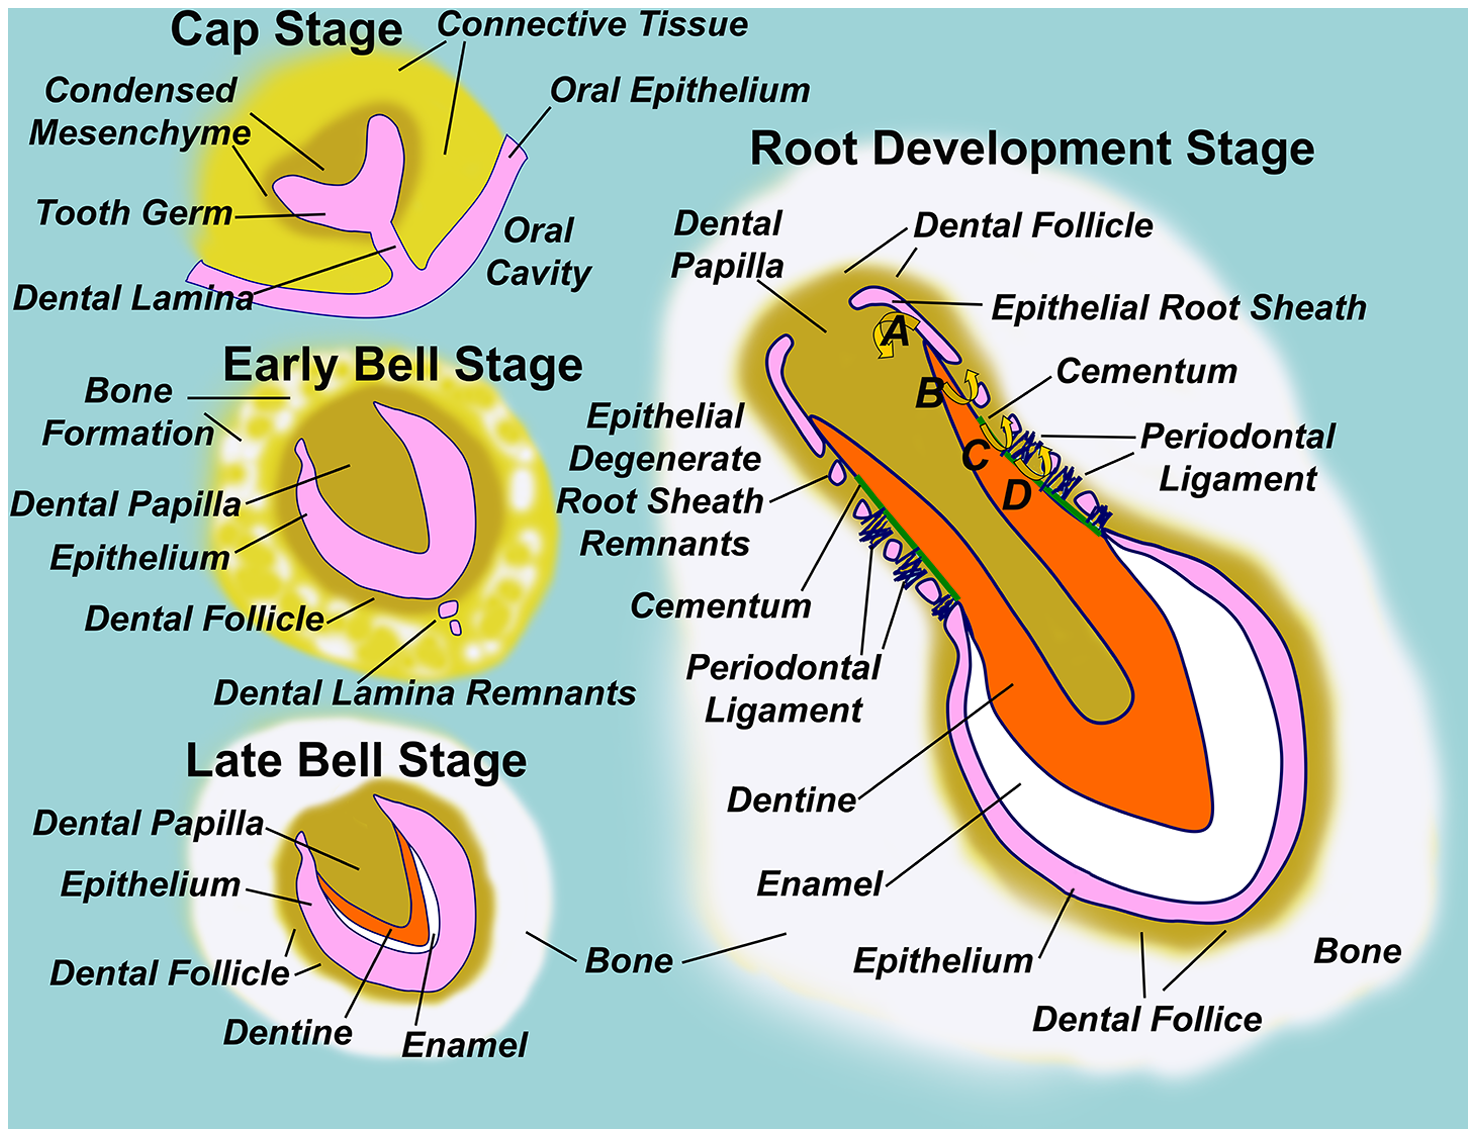
Follow the dental lamina, enamel organ, dental papilla and dental follicle through development. Locate the epithelial root sheath in the root-development panel.
Diagram illustrating normal tooth formation.png · Sarrafpour B, Swain M, Li Q, Zoellner H · CC BY 4.0. None; reproduced without alteration.
Which structure gives rise to dentine and pulp?
The dental papilla. The enamel organ gives rise to enamel; the dental follicle contributes to supporting periodontal tissues.
Read the three dimensions of facial development
Assess anteroposterior jaw relationships, vertical proportions and transverse width. A convex profile may suggest a skeletal Class II relationship, while a concave profile can suggest Class III, but soft-tissue thickness and posture influence appearance. Examine facial symmetry and compare centrelines and the chin in rest and closure.
A high-angle pattern often accompanies increased lower facial height and open-bite tendency; a low-angle pattern may accompany a deep bite. These are tendencies rather than diagnoses on their own. Dental compensation can mask the skeletal discrepancy, for example retroclined lower incisors in a Class III pattern. Treating only visible crowding can miss these relationships.
Mixed dentition on a panoramic radiograph
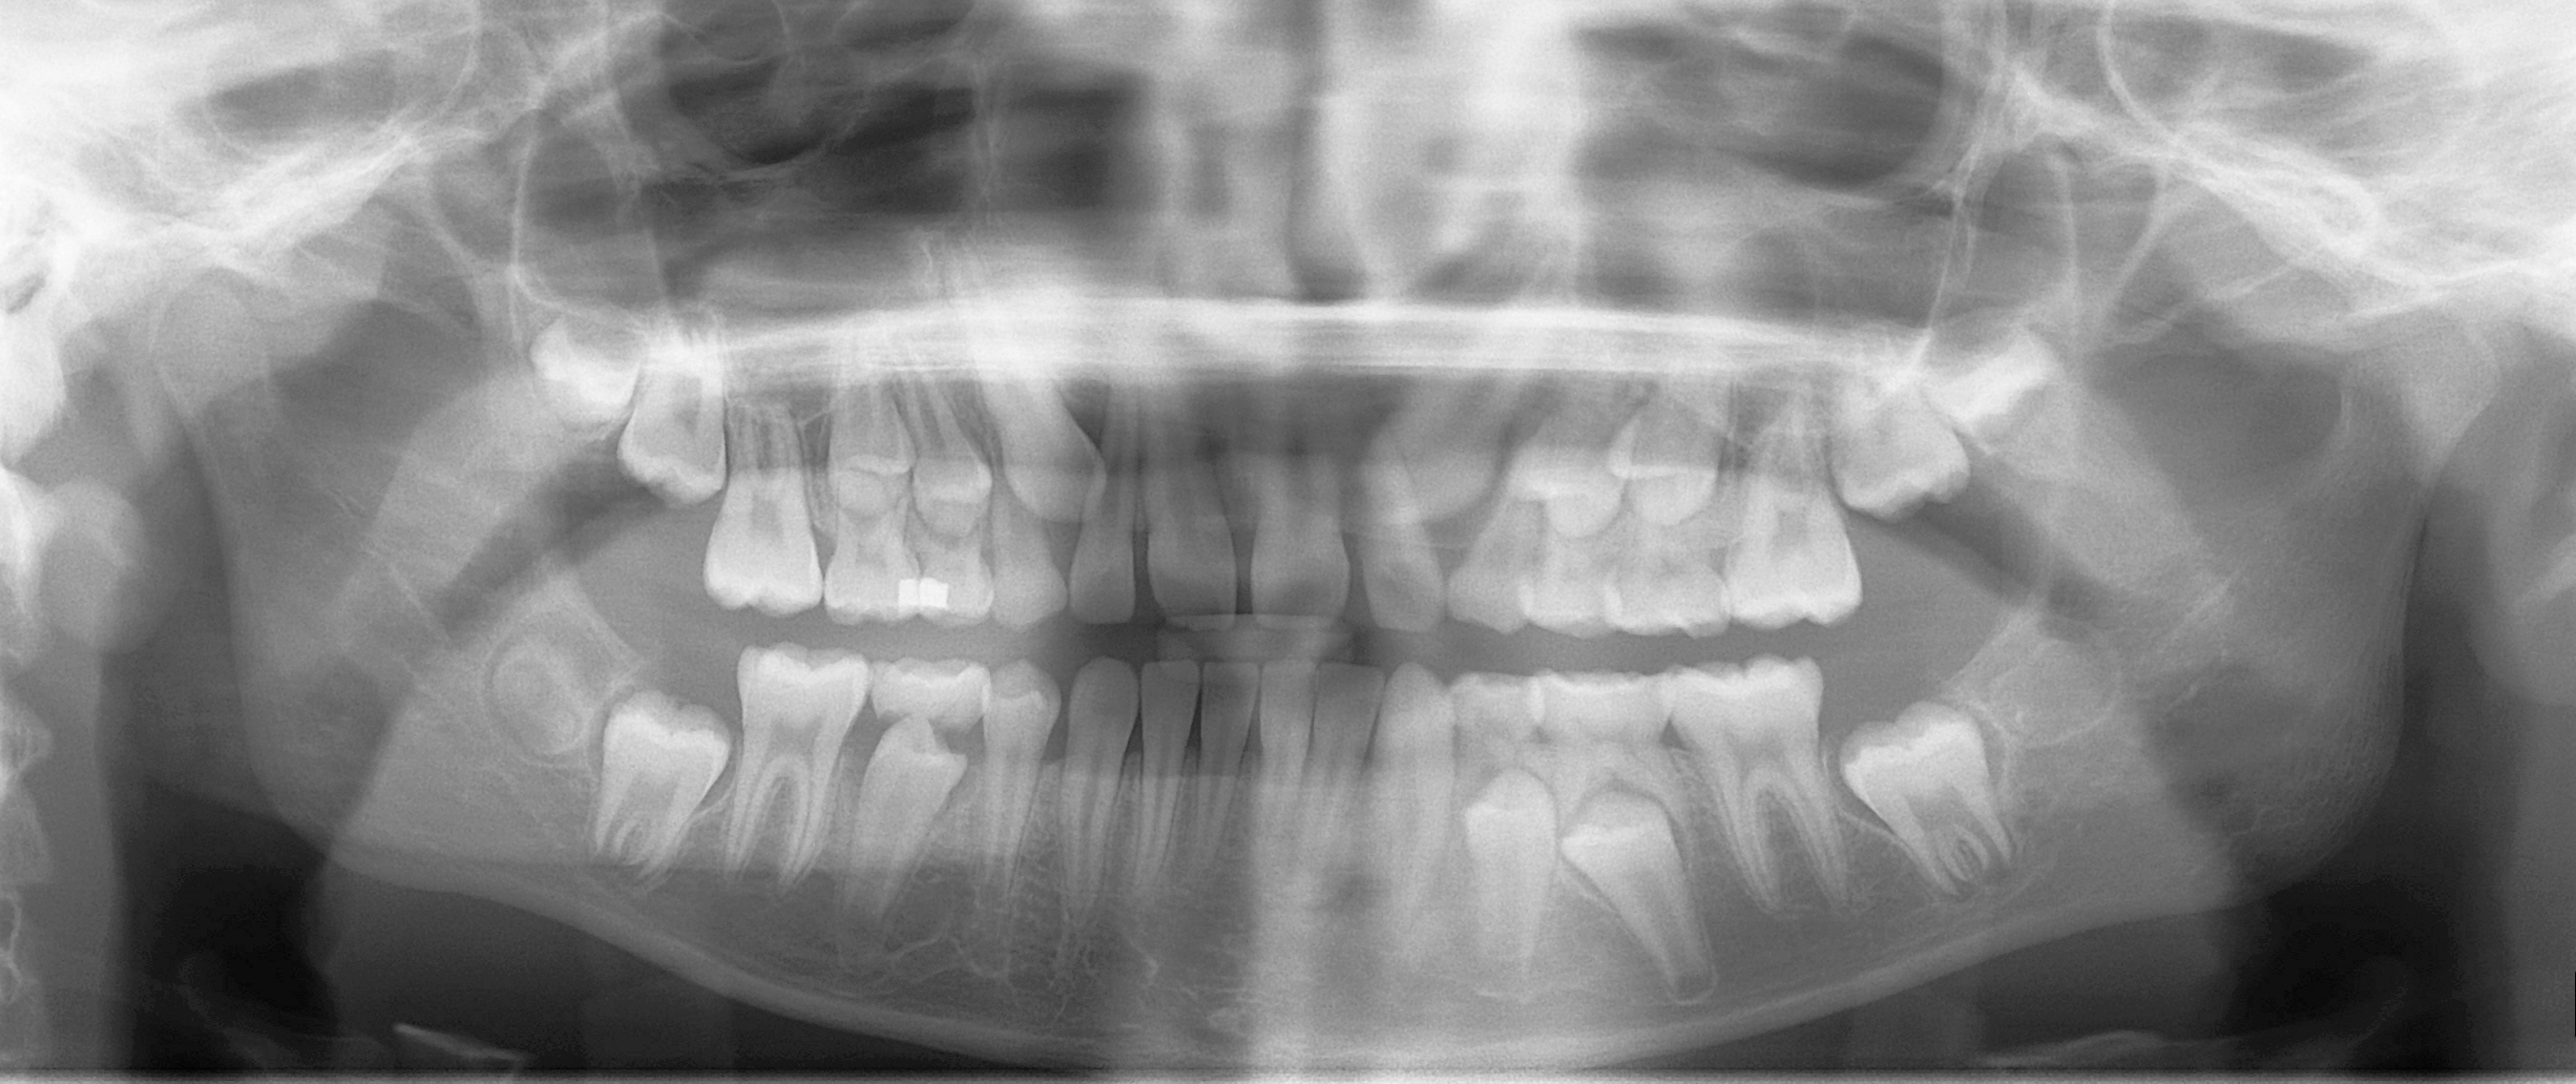
Distinguish erupted permanent teeth, retained primary teeth and unerupted successors. Compare development on the two sides and account for every permanent tooth. This is one published example of mixed dentition, not a fixed age-based template for every child.
Mixed dentition pan.jpg · Coronation Dental Specialty Group · CC BY 3.0. None; original image reproduced without alteration.
Which permanent teeth erupt without replacing primary teeth?
The permanent molars. Premolars replace the primary molars; permanent incisors and canines replace their primary predecessors.
Follow dentition stages and space changes
The primary dentition establishes an initial occlusal relationship, then larger incisors and first molars emerge during early mixed dentition. Later, primary canines and molars are replaced and leeway space becomes relevant. Count teeth, compare sides and palpate the canine regions rather than relying solely on an age-based eruption chart.
Premature loss, hypodontia, supernumerary teeth, ectopia and ankylosed primary teeth can redirect development. Record the actual stage and space available. Natural developmental spacing does not make every diastema pathological, while marked asymmetric incisor eruption is a different problem. Distinguish a physiological transition from an obstruction that will not resolve by waiting.
Estimate remaining growth with appropriate caution
Height history, pubertal development, growth velocity, dentition and previous records can contribute to an estimate. Pubertal timing varies considerably between individuals, and dental maturity does not perfectly predict skeletal maturity. Girls often mature earlier than boys at a population level, but this is not a reliable individual scheduling rule.
Do not expose a patient to radiographs solely to obtain a maturity score unless justified for a treatment decision. When a cephalogram is otherwise indicated, cervical vertebral appearance may contribute but cannot guarantee future growth. Family pattern and serial observations can refine expectations. Explain that growth modification has biological limits and future growth is never entirely predictable.
Identify problems where timing changes options
A developing Class II pattern may benefit from assessment while growth remains. Functional appliances alter occlusal and muscular relationships and achieve important dentoalveolar changes; do not promise large permanent increases in mandibular size. Early Class III assessment can identify selected opportunities for intervention, but later mandibular growth may still compromise the result.
Crossbites with a functional mandibular shift, asymmetric eruption, suspected ectopic canines and compromised first molars deserve attention before the full permanent dentition is established. Other alignment problems can usually wait until the relevant teeth erupt. Referral timing should preserve an option, rather than being early merely to join a queue.
Understand limits and plan long-term review
Once growth is largely complete, severe skeletal discrepancies may require combined orthodontic and surgical treatment if the patient wants correction. Dentoalveolar camouflage may be appropriate in selected cases but has periodontal and aesthetic limits. Adult tooth movement remains possible when tissue health permits, although growth-related options differ.
Continued facial and dentoalveolar changes also influence relapse and implant timing. A fixed implant does not erupt with neighbouring teeth, so growth assessment is important in planning replacement of a missing incisor. Monitor an evolving problem with an explicit question and review point. Document uncertainty, changing goals and the need for retention after active orthodontic care.
A distinction to remember
Functional appliances are not a guarantee of a permanently larger lower jaw. Explain expected dental effects, growth limitations and possible later treatment.
A twelve-year-old has a large overjet, a retrusive mandibular profile and remaining growth. Why might referral now matter?
Reveal the reasoning
Assessment before growth is complete may preserve suitable treatment options, including functional appliances when indicated. Record dental and skeletal findings and readiness. The appliance may achieve substantial dental correction, but should not be promised to permanently transform mandibular growth.
Test your recall
Why distinguish dental from skeletal Class II features?
Show answer
A Class II incisor relationship may reflect tooth inclination, a jaw discrepancy or both. The distinction changes what tooth movement can reasonably achieve and whether growth-related or surgical options are relevant. An overjet measurement alone does not identify the underlying mechanism.