
White and red lesions
Colour reflects changes in keratin, epithelial thickness, inflammation, blood vessels or surface material. It does not establish a diagnosis or cancer risk by itself. Assess whether the change wipes away, its distribution and persistence, and any focal ulceration, induration or evolution before deciding whether reassurance, treatment or biopsy is appropriate.
Quick revision summary
Describe colour and behaviour precisely
Record site, size, number, symmetry, surface, margins and palpation findings. A homogeneous flat white plaque differs from a speckled red-white, nodular or verrucous lesion. Ask about duration, change, soreness, trauma, tobacco, areca use, alcohol, immune status and medicines.
Interpret red lesions in context
Erythema may reflect inflammation, candidosis, trauma, epithelial atrophy or other mucosal disease. Geographic tongue has changing depapillated areas with a characteristic border and migratory course; a fixed indurated red area needs another explanation.
Explain monitoring and risk reduction
Support cessation of tobacco and areca exposure and appropriate alcohol advice without blame. Continue preventive dental care and explain the difference between a clinical appearance and a tissue diagnosis. Many white or red changes are benign, but some need surveillance even after initial treatment.
Common mistake
“It does not rub off” narrows the differential; it neither diagnoses leukoplakia nor proves malignancy. A painless red patch can still be significant.
White and red lesions: build a mucosal differential
Colour reflects changes in keratin, epithelial thickness, inflammation, blood vessels or surface material. It does not establish a diagnosis or cancer risk by itself. Assess whether the change wipes away, its distribution and persistence, and any focal ulceration, induration or evolution before deciding whether reassurance, treatment or biopsy is appropriate.
Describe colour and behaviour precisely
Record site, size, number, symmetry, surface, margins and palpation findings. A homogeneous flat white plaque differs from a speckled red-white, nodular or verrucous lesion. Ask about duration, change, soreness, trauma, tobacco, areca use, alcohol, immune status and medicines. Photographs help compare evolving lesions.
Gently testing whether a surface coating wipes away can help, but it is not an absolute diagnostic test. Pseudomembranous candidosis may leave an erythematous surface, whereas many keratotic lesions remain. Do not scrape aggressively or use wiping behaviour to decide whether a persistent abnormality is safe.
Oral lichen planus: reticular white striae
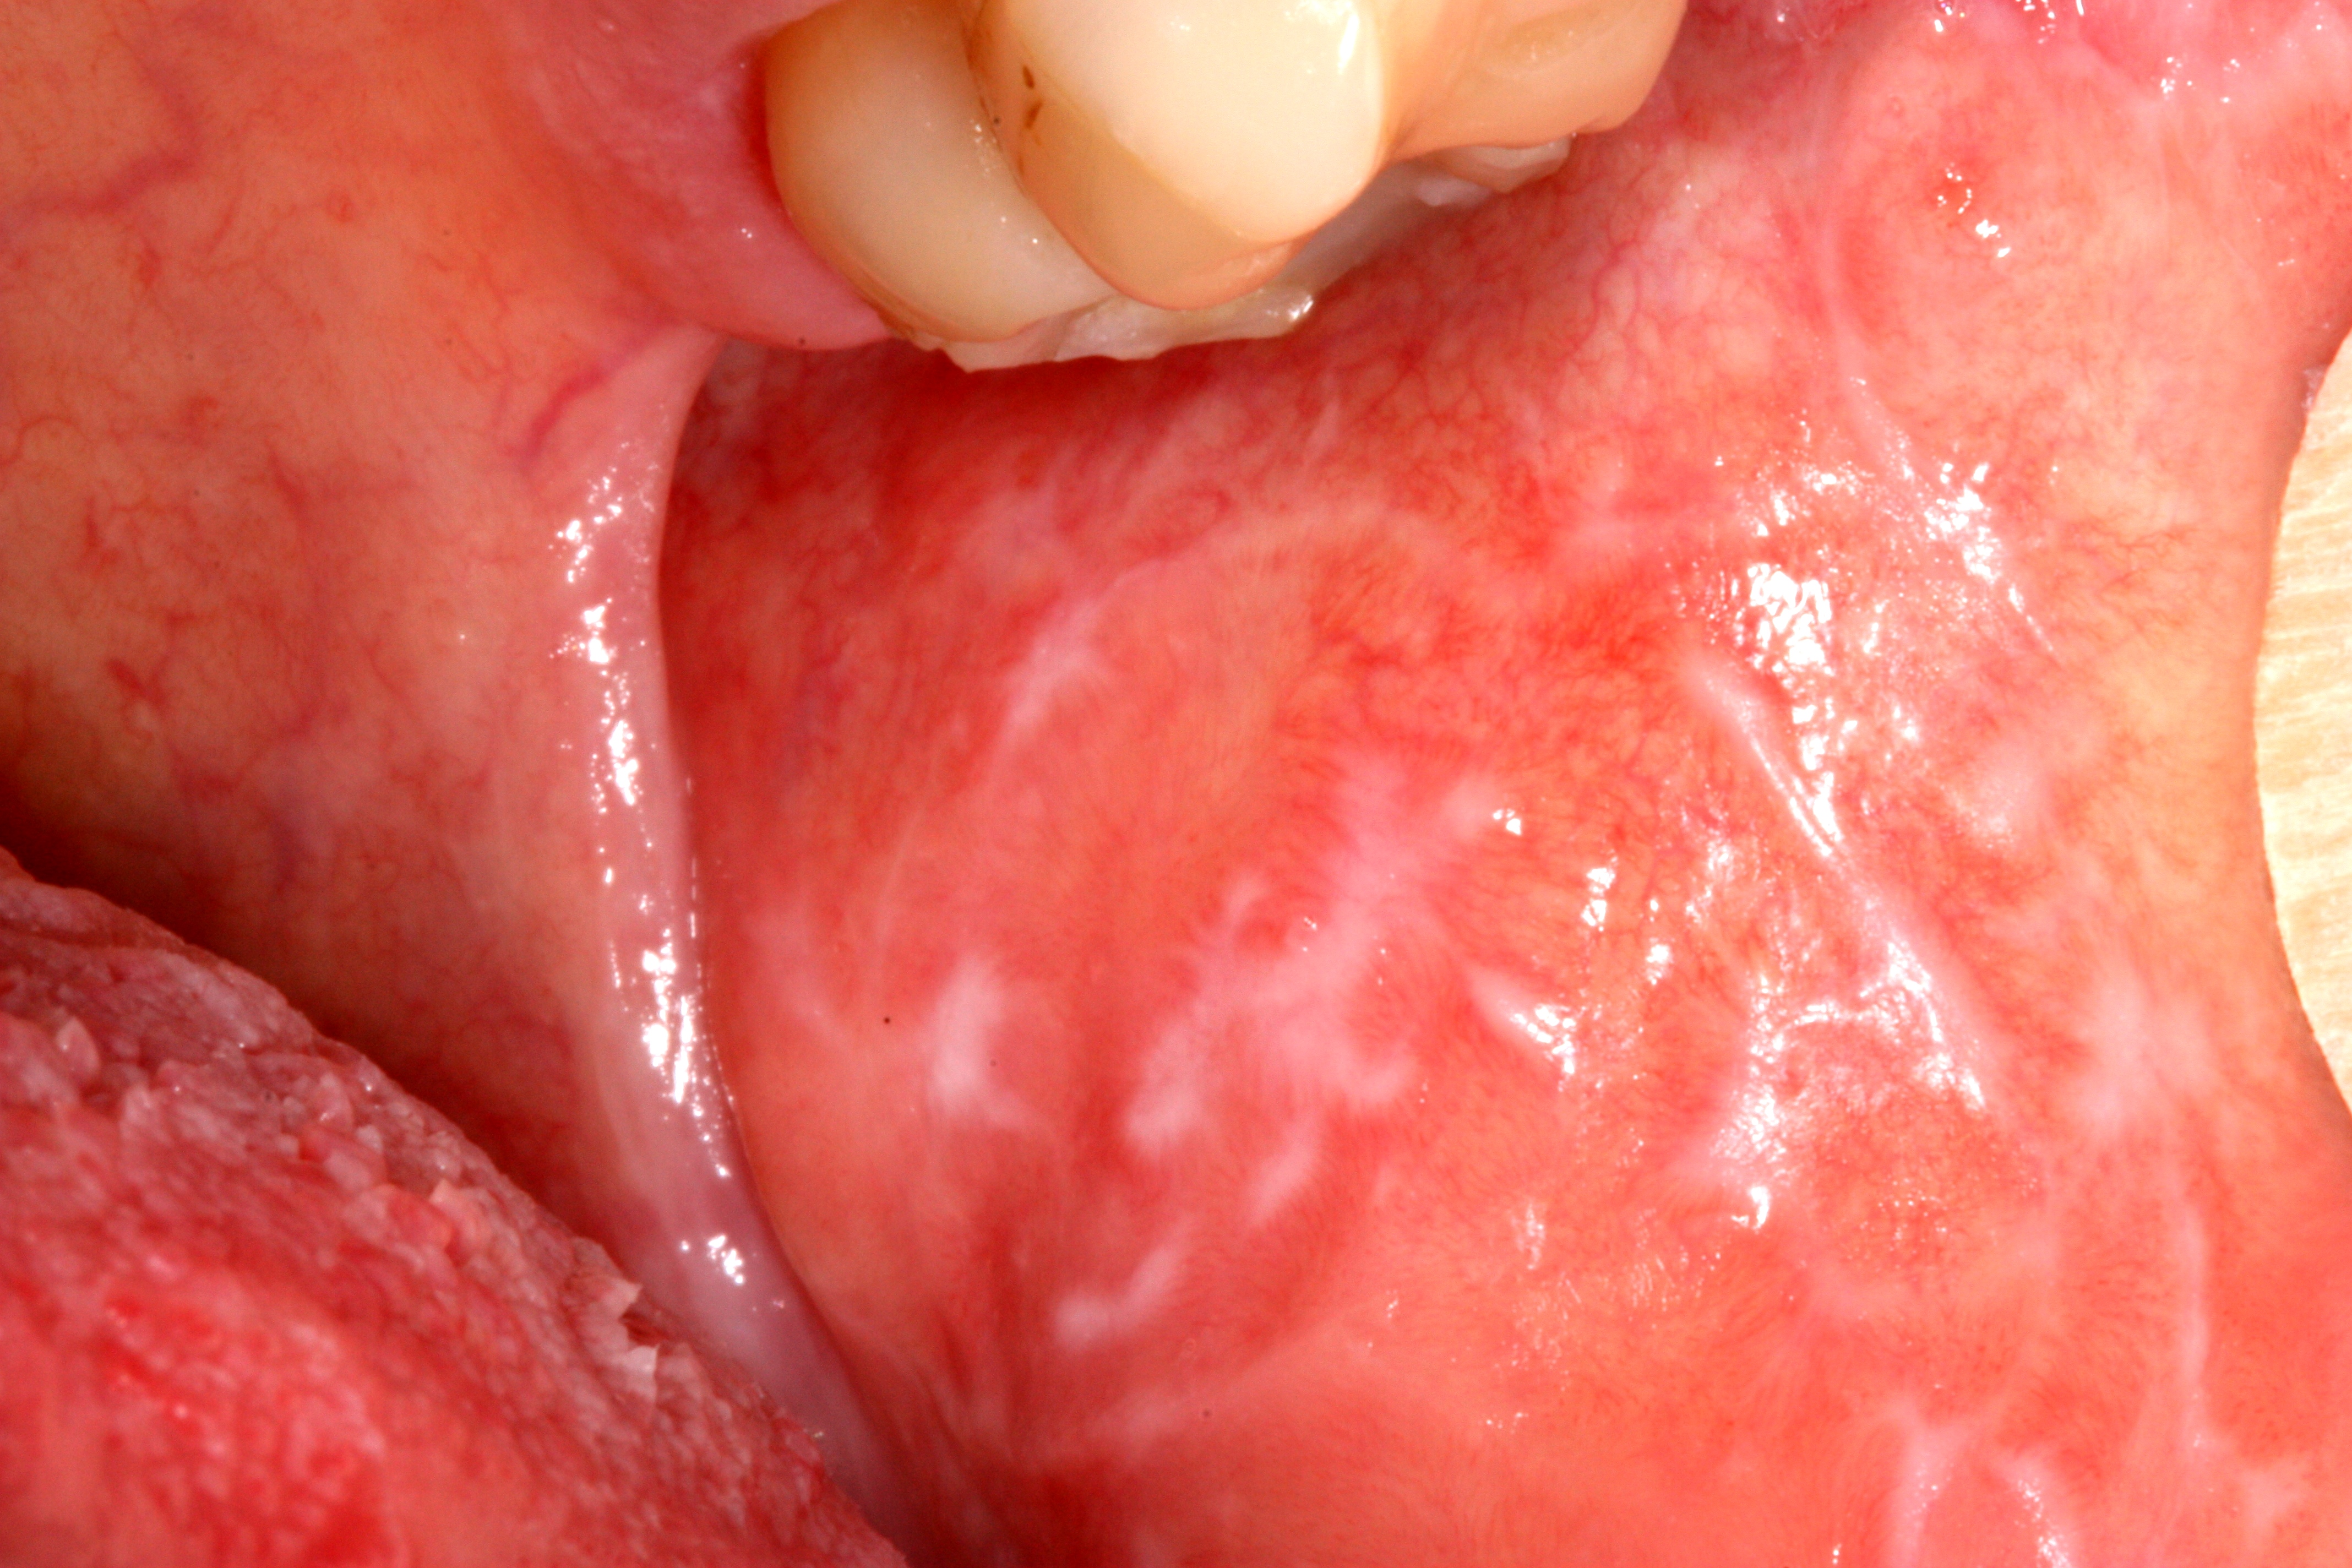
Follow the fine, intersecting white lines across the buccal mucosa. The source identifies this as non-erosive oral lichen planus. In practice, examine the distribution elsewhere in the mouth and consider lichenoid reactions; a photograph cannot establish the full clinical or histological diagnosis.
Lichen_planus.jpg · Ian Furst · CC BY-SA 4.0. Source image reproduced without alteration; any arrows or circles are part of the original.
Which visible feature gives this lesion a reticular pattern?
The interlacing white striae form a lace-like network. Describe that pattern before interpreting it, then correlate with distribution, history and appropriate clinical assessment.
Recognise benign and reactive white patterns
Frictional keratosis should fit a credible chronic mechanical exposure; reassessment after removing the irritant confirms the interpretation. Linea alba and cheek-biting changes follow characteristic sites and appearances. Leukoedema is a diffuse mucosal variant that becomes less conspicuous on stretching, rather than a focal progressive plaque.
A coated or hairy tongue reflects surface accumulation and altered filiform papillae, with a different differential from a discrete lateral tongue patch. Oral hairy leukoplakia is associated with Epstein–Barr virus and immune context, and should not be confused with ordinary leukoplakia because of its name. Atypical appearances warrant specialist assessment.
Oral lichen planus: a mixed red and white appearance
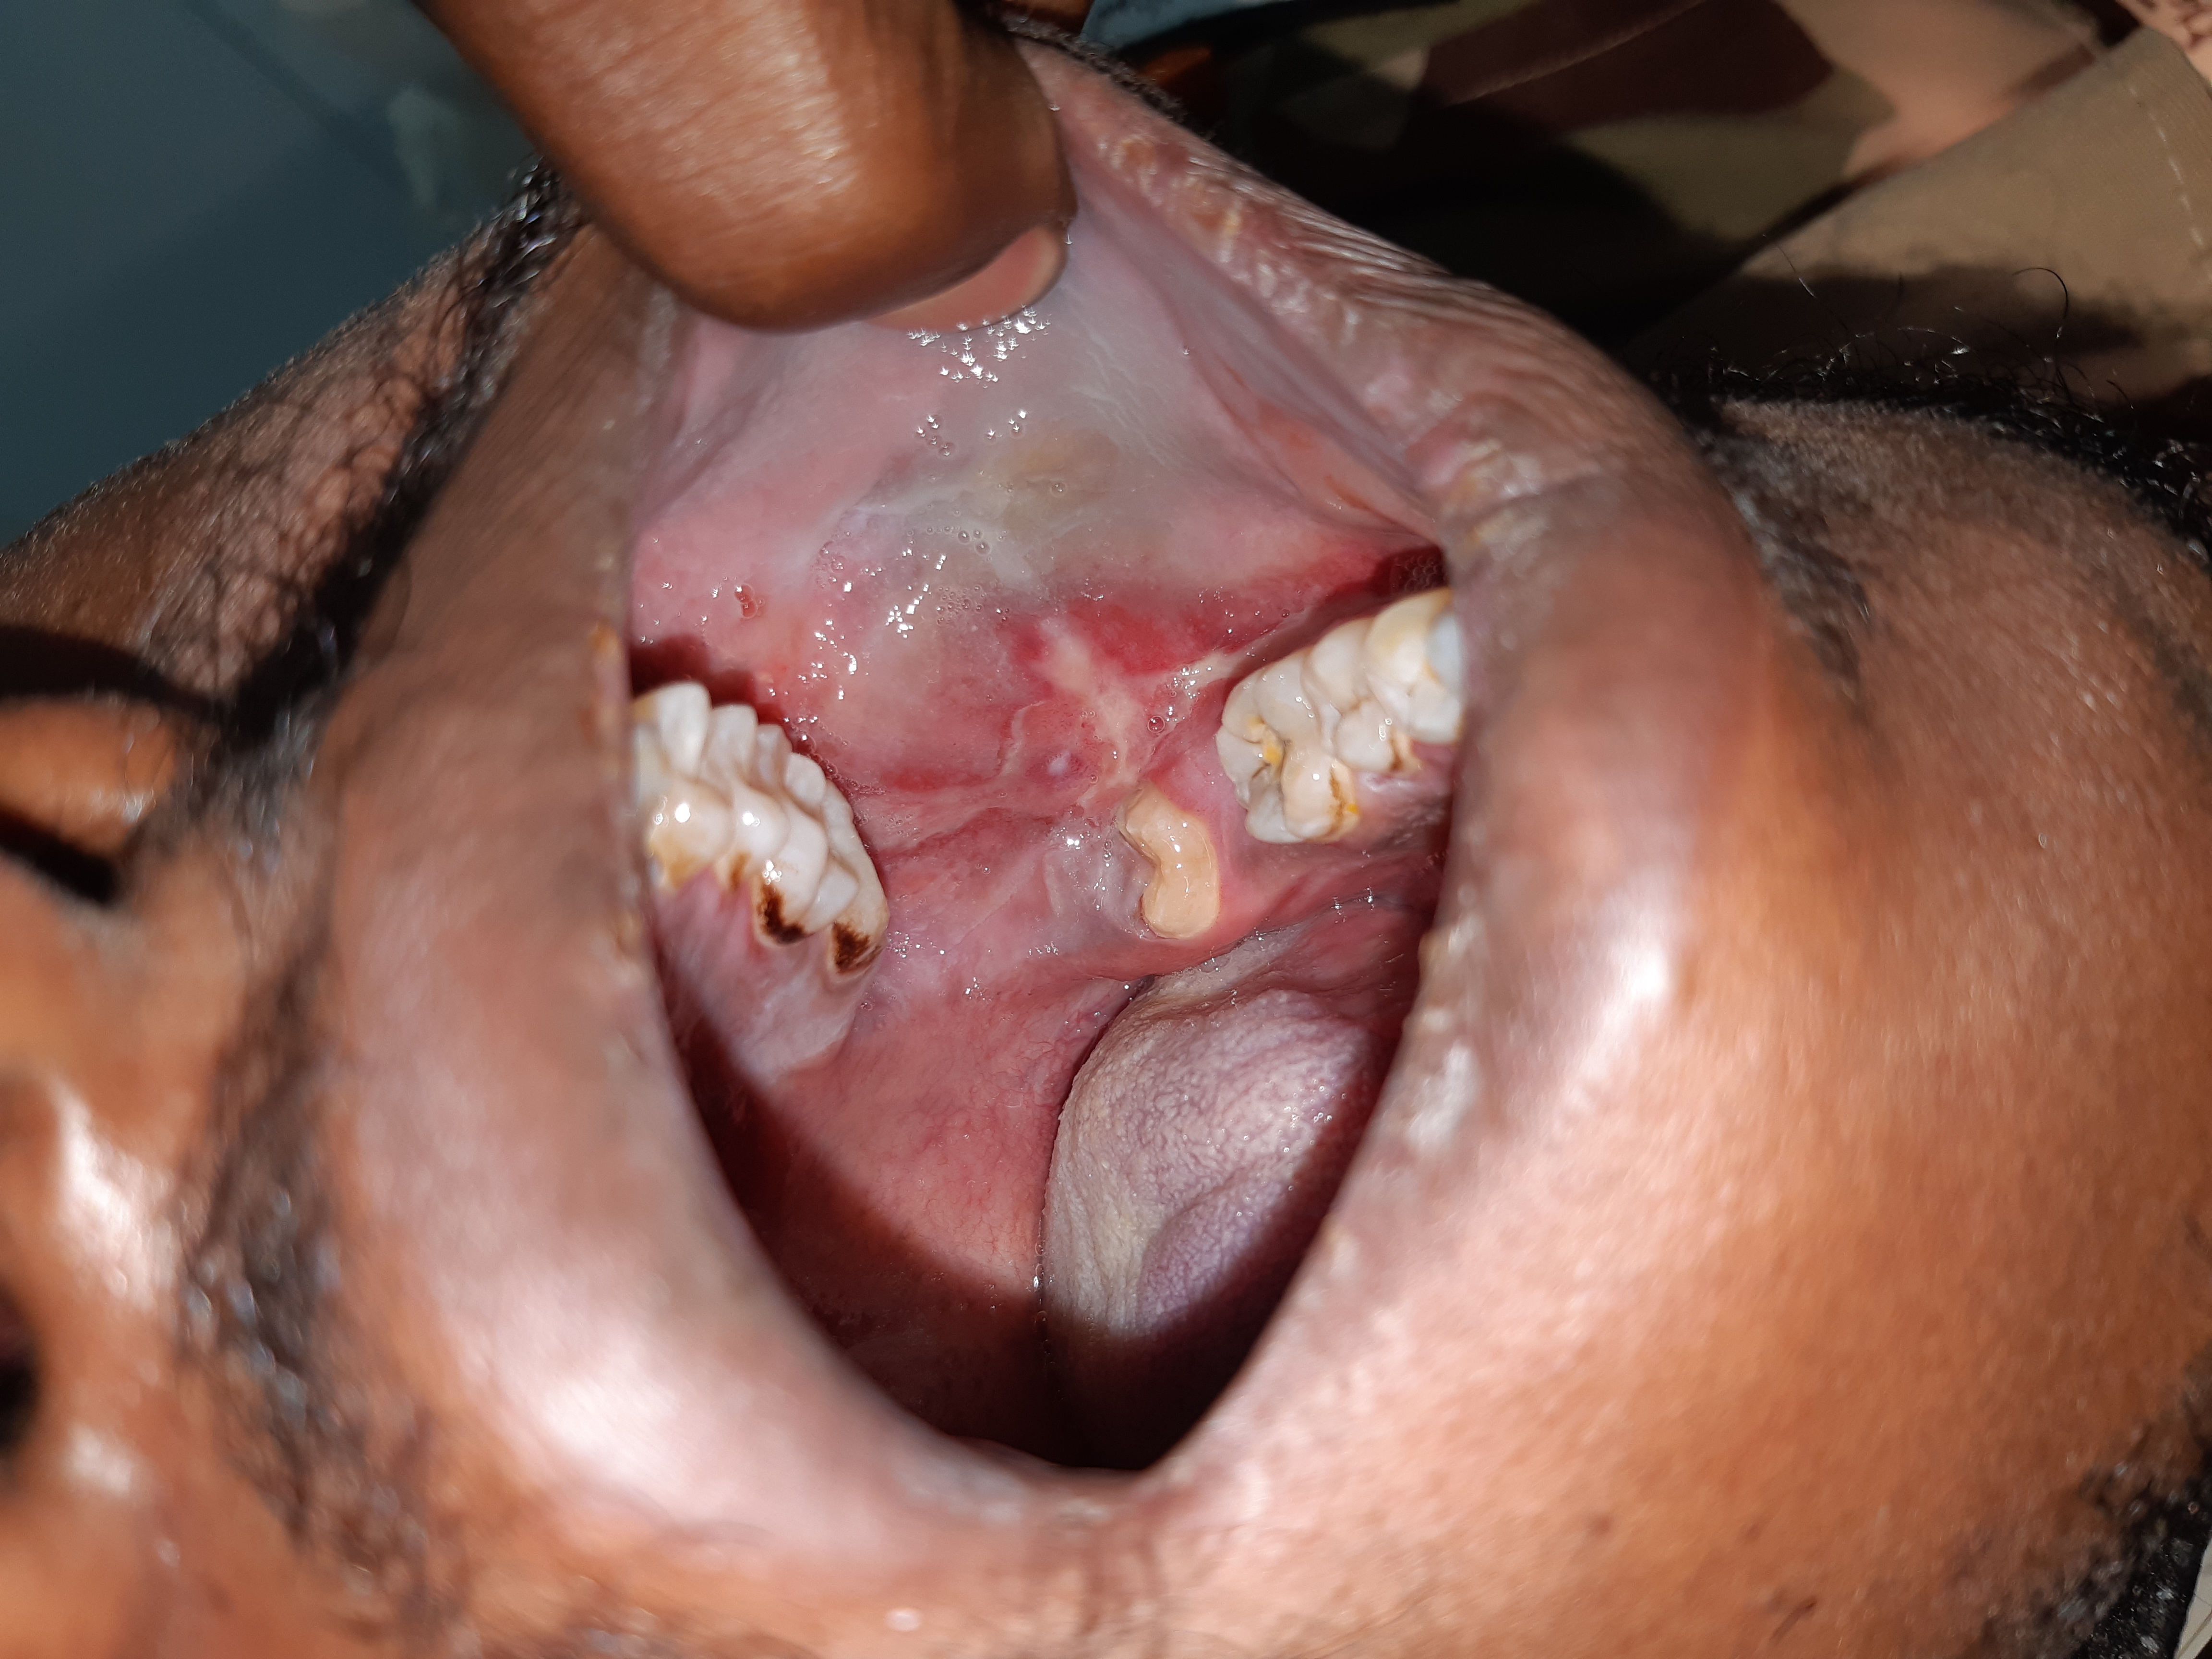
Compare the white striae and thicker white areas with the adjacent erythematous mucosa. The source labels this case oral lichen planus. A red or ulcerated area needs assessment in its own right: symptoms, change, induration and a persistent focal abnormality matter, even when a background lichenoid pattern is familiar.
Lichen_planus-intra_oral_lesion.jpg · Syed Wali Peeran · CC BY-SA 4.0. Source image reproduced without alteration; any arrows or circles are part of the original.
Does recognising a lichenoid pattern explain every red area in the photograph?
No. Describe and assess each significant area. Lichenoid disease, trauma, infection and dysplasia can overlap clinically; a persistent or changing focal lesion may need specialist assessment and biopsy.
Separate infection from immune-mediated disease
Pseudomembranous and erythematous candidosis can produce white coating or red soreness, respectively. Assess denture surfaces, recent antibiotics, inhaled steroids, dry mouth and immune compromise. A positive Candida result alone can represent colonisation and must fit the clinical lesion.
Oral lichen planus often has bilateral reticular striae with possible erythema or erosion. Lichenoid reactions may relate to medicines or a local contact pattern. Desquamative gingivitis has a broader differential, including blistering disease. An isolated persistent plaque should not be called lichen planus solely because one edge appears white.
Leukoplakia: a focal white plaque
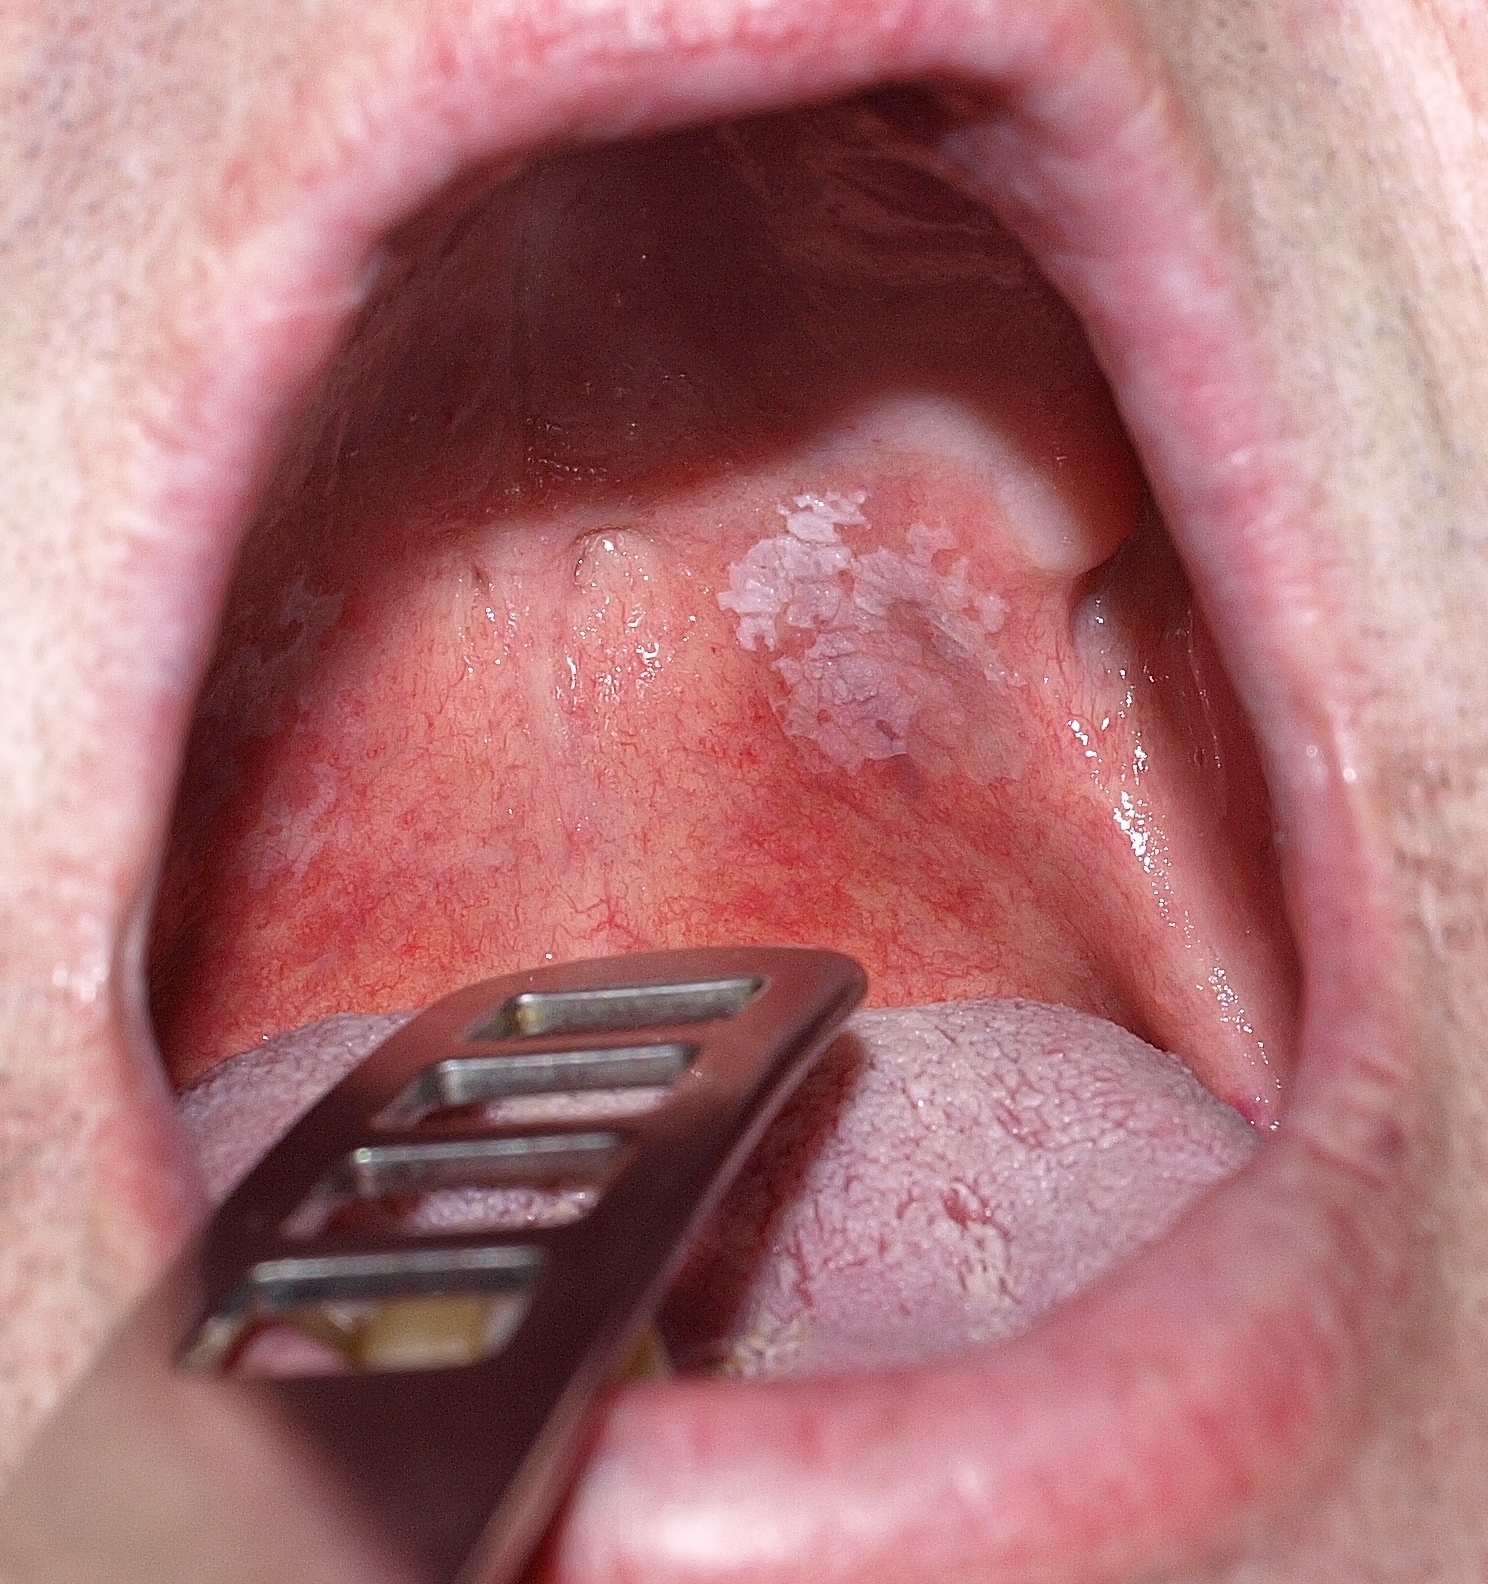
Describe the plaque’s site, outline, surface and surrounding mucosa before proposing a diagnosis. The source calls this lesion leukoplakia and reports that malignancy was excluded histologically in that case. That result cannot be inferred from its appearance or applied to another patient; white colour alone does not establish benignity.
Orale_Leukoplakie.jpg · Klaus D. Peter, Gummersbach, Germany · CC BY 3.0 DE. Source image reproduced without alteration; any arrows or circles are part of the original.
Can this photograph tell you whether the plaque contains epithelial dysplasia?
No. Dysplasia is a histological assessment. Clinical features guide the differential, urgency and sampling, but the photograph alone cannot grade or exclude it.
Interpret red lesions in context
Erythema may reflect inflammation, candidosis, trauma, epithelial atrophy or other mucosal disease. Geographic tongue has changing depapillated areas with a characteristic border and migratory course; a fixed indurated red area needs another explanation. Localised denture-related redness should fit the appliance-bearing area and its contributing factors.
Erythroplakia and erythroleukoplakia describe otherwise unexplained red or mixed red-white lesions after appropriate exclusion of other causes. They can harbour important dysplasia or carcinoma and need prompt specialist assessment. The absence of pain, tobacco use or an obvious mass does not provide reassurance.
Oral candidosis: pseudomembranous plaques
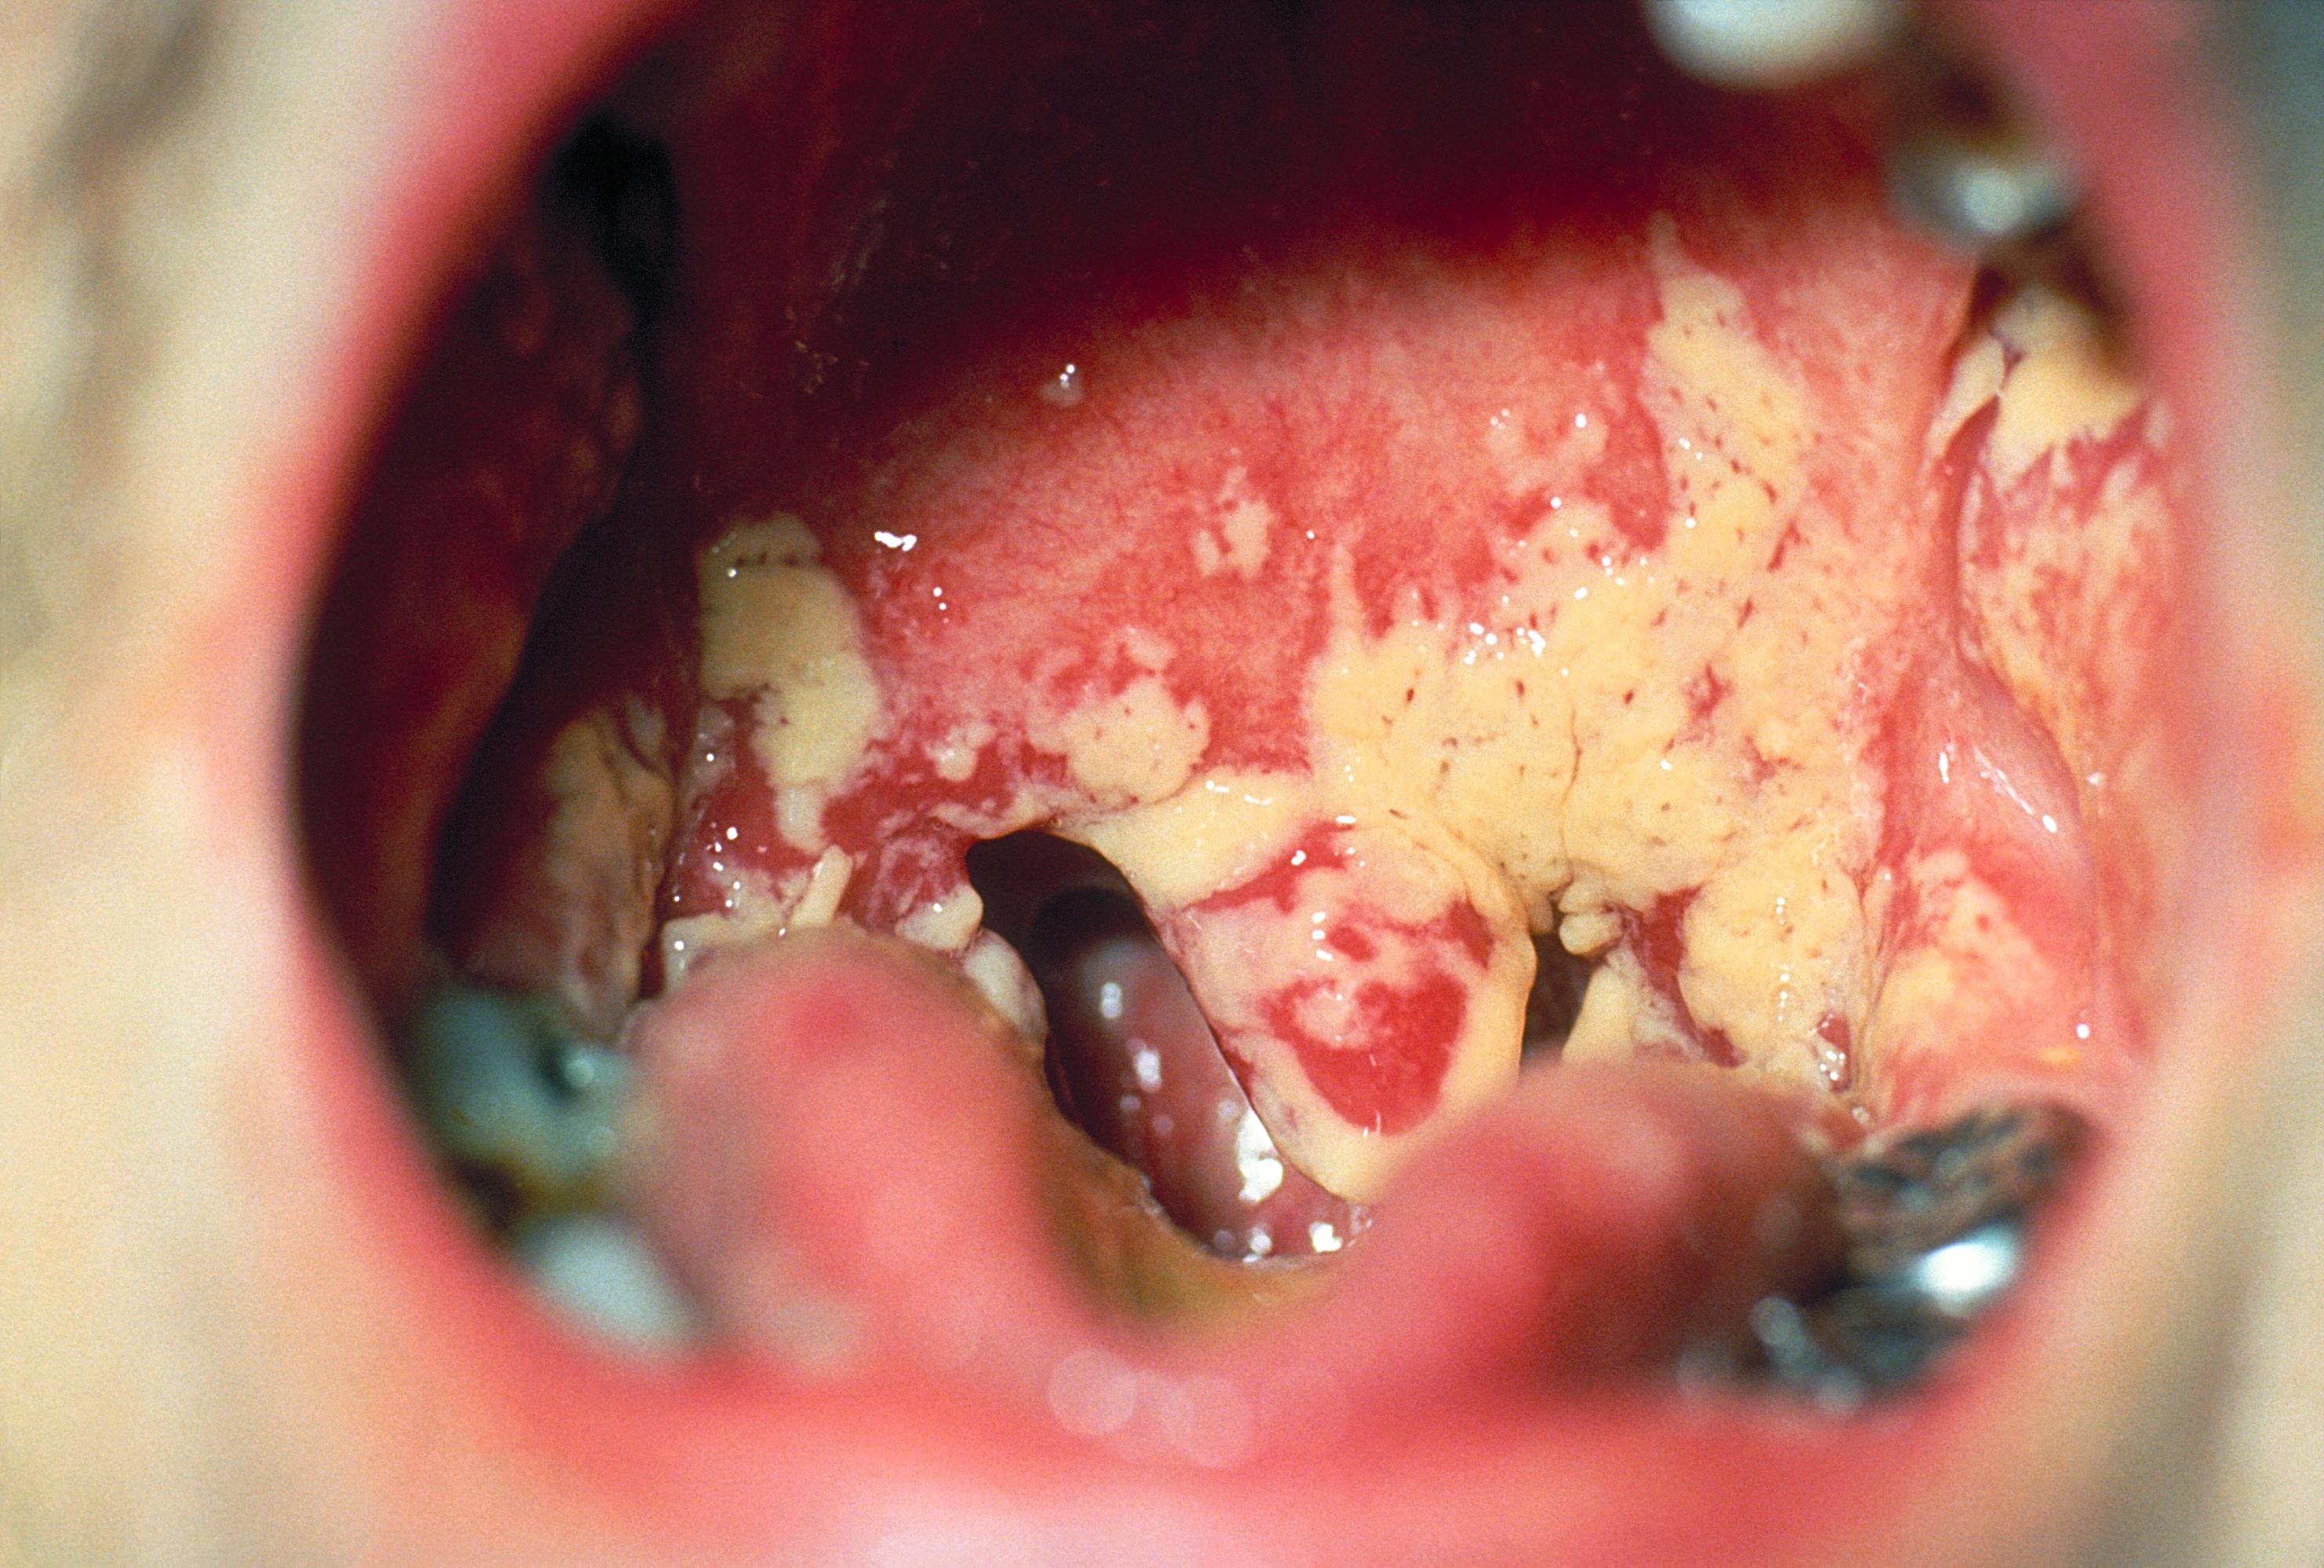
The CDC source identifies oral candidosis. Note the cream-coloured plaques over erythematous mucosa. Pseudomembranous candidosis often has removable deposits, but a static photograph cannot demonstrate that behaviour. Correlate with examination and factors such as medicines, denture use, dry mouth and immunosuppression. The legacy filename includes “Aphthae”; this is not an aphthous-ulcer example.
Oral_thrush_Aphthae_Candida_albicans._PHIL_1217_lores.jpg · Centers for Disease Control and Prevention (CDC), PHIL 1217 · Public domain (US federal government). Source image reproduced without alteration; any arrows or circles are part of the original.
What bedside observation helps distinguish pseudomembranous candidosis from a fixed white plaque?
Whether the deposit can be gently removed, often exposing erythematous mucosa. Interpret this with the history and examination; not every white lesion is candidosis.
Use leukoplakia as a clinical diagnosis of exclusion
Leukoplakia is a persistent white plaque that cannot be characterised as another defined condition. It is not synonymous with every white patch, histological dysplasia or invasive cancer. The histology can vary, and the patient’s risk cannot be determined from whiteness alone.
Non-homogeneity, focal redness, ulceration, nodularity, induration, change and high-risk anatomical contexts increase concern. Proliferative multifocal verrucous disease requires specialist longitudinal assessment. A bland-looking area in a heterogeneous lesion may not represent the most significant pathology, so biopsy planning should consider the whole distribution.
Geographic tongue: map-like depapillation
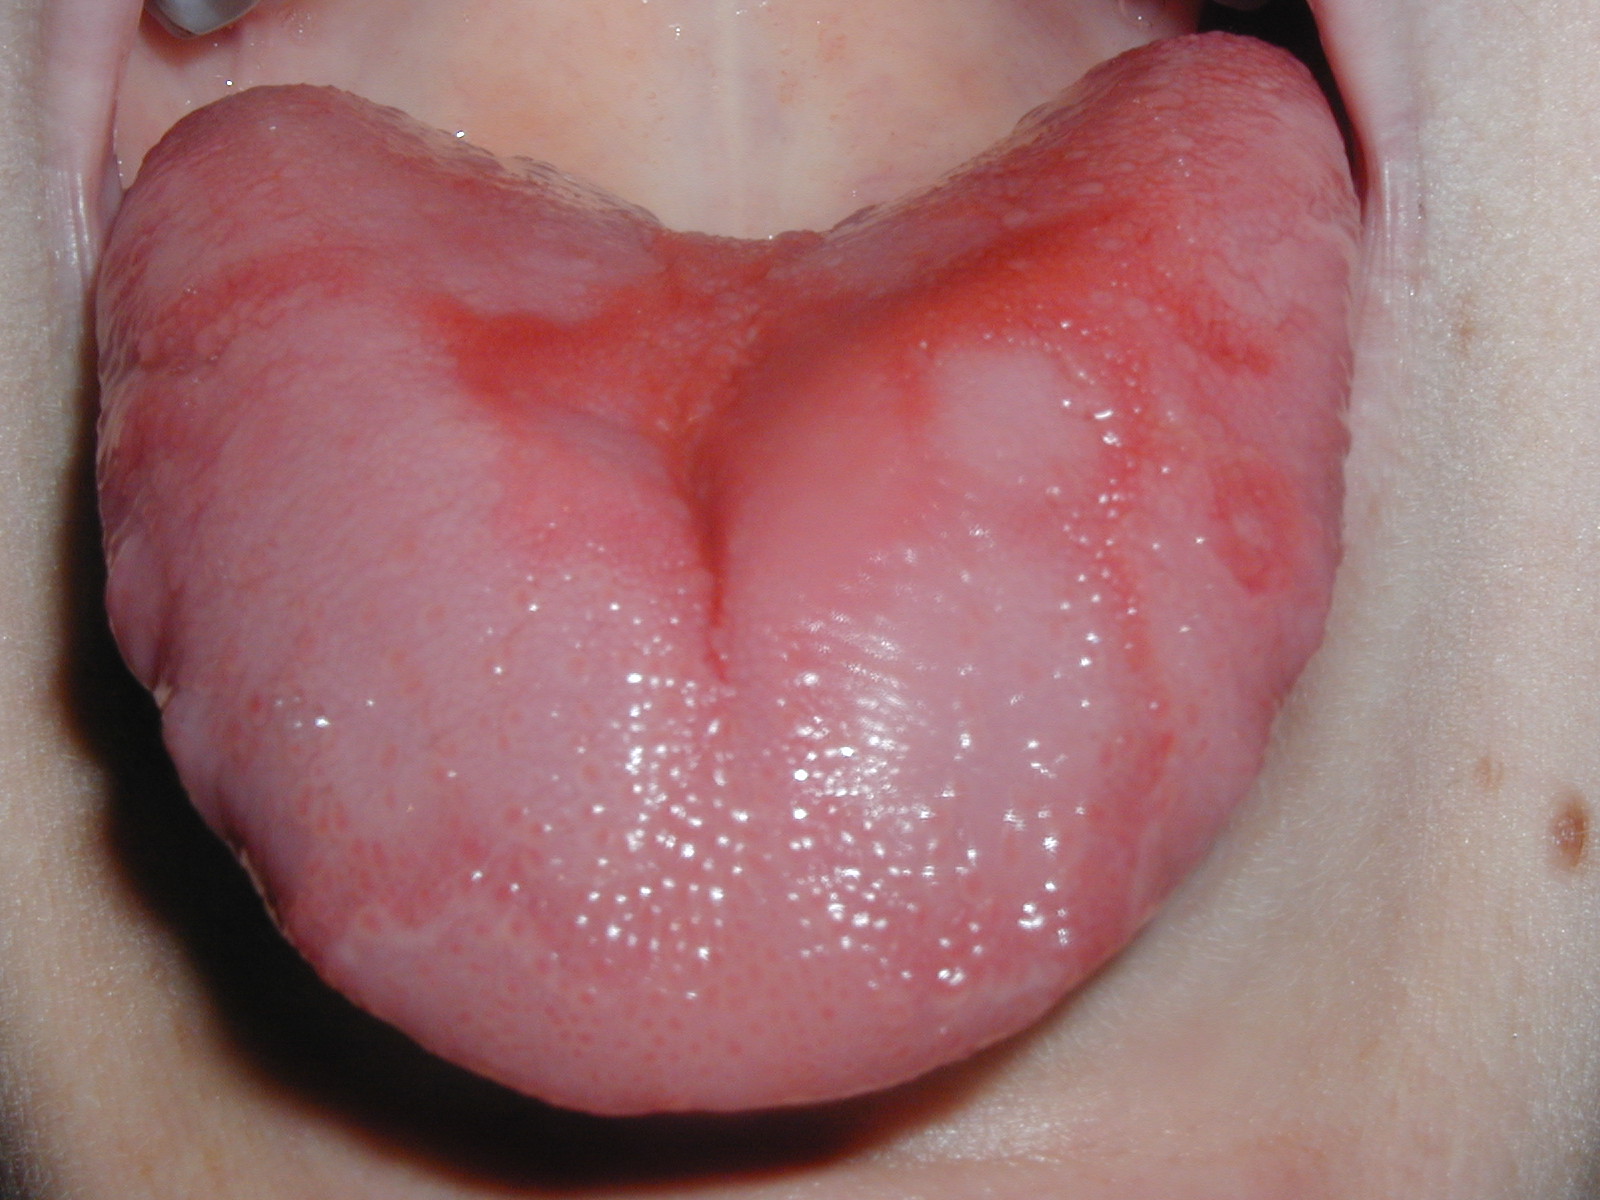
Follow the irregular red areas and their pale curving borders. The source identifies geographic tongue. The changing distribution over time is clinically useful: a single photograph shows a pattern but cannot demonstrate migration. Compare this broad map-like appearance with the more localised midline change in the median rhomboid glossitis example.
Geographic Tongue.jpg · Jaksmata · CC BY-SA 3.0. Reproduced without alteration. Labels, arrows and circles, where present, belong to the source image.
Which feature needs a history or serial photographs rather than one static image?
Migration: the shape and position can change over time. Ask about the course and inspect the whole tongue rather than inferring change from one photograph.
Choose assessment, treatment or biopsy
A credible reversible cause may justify targeted treatment with a documented review, provided this does not delay referral of a suspicious lesion. Treat candidosis using current guidance and interaction checks, and address trauma or appliance factors. Improvement must be assessed clinically rather than inferred from less soreness.
Unexplained persistent lesions, suspicious focal change or a relevant red/red-white lesion require specialist evaluation and biopsy when indicated. Record the exact sampled area and correlate histology. A small nondysplastic sample does not establish the safety of every part of a large or changing lesion.
Median rhomboid glossitis: central papillary change
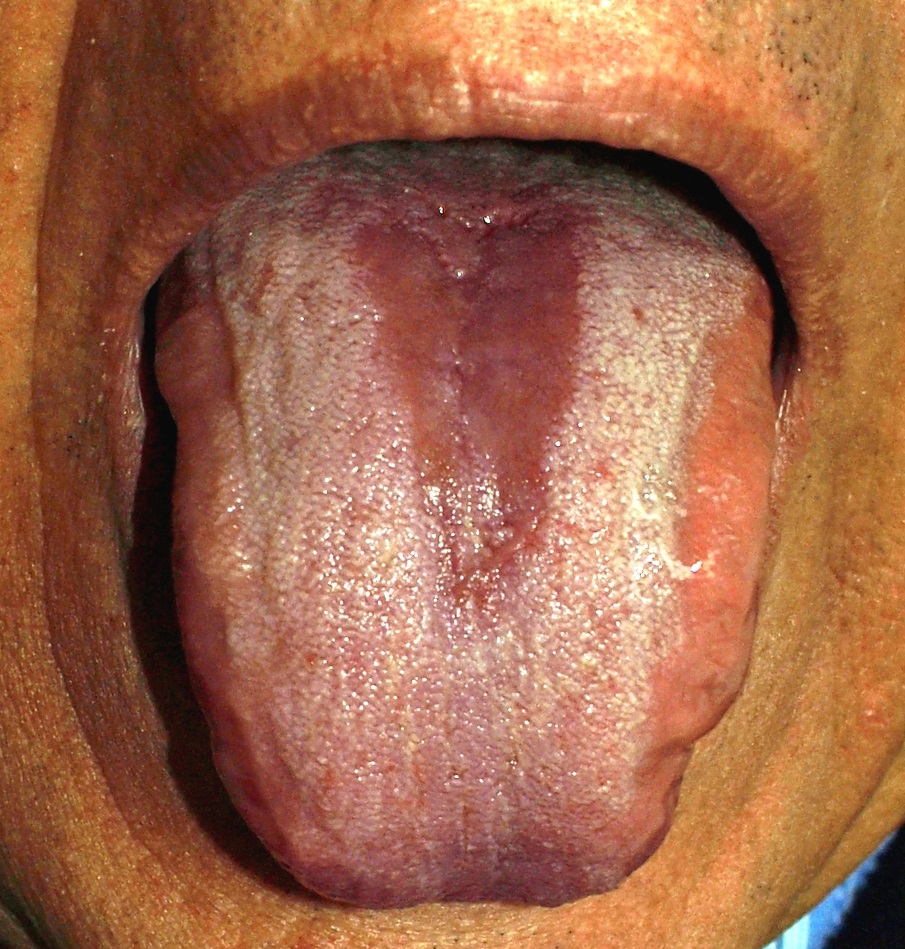
The source identifies median rhomboid glossitis. Locate the relatively smooth red midline area and compare it with the surrounding papillary surface. Describe the site and shape before interpreting the cause. A photograph does not demonstrate fungal organisms, and treatment decisions depend on symptoms and the wider assessment.
Glossitis.jpg · Klaus D. Peter, Wiehl, Germany · CC BY 3.0 DE. Reproduced without alteration. Labels, arrows and circles, where present, belong to the source image.
How does its distribution differ from the geographic-tongue example?
This example has a more localised central area. Geographic tongue shows an irregular map-like pattern whose distribution may change over time.
Explain monitoring and risk reduction
Support cessation of tobacco and areca exposure and appropriate alcohol advice without blame. Continue preventive dental care and explain the difference between a clinical appearance and a tissue diagnosis. Many white or red changes are benign, but some need surveillance even after initial treatment.
Review the entire mouth and compare photographs, symptoms and palpation, not just the original index patch. Give a clear route for persistent ulceration, new focal thickening or a lump. Follow-up should reflect the diagnosis and risk rather than a single interval applied to all mucosal colours.
A distinction to remember
“It does not rub off” narrows the differential; it neither diagnoses leukoplakia nor proves malignancy. A painless red patch can still be significant.
An adult has a persistent painless red-white patch on the floor of the mouth without a clear cause. What is the appropriate next step?
Reveal the reasoning
Arrange prompt specialist assessment through the appropriate suspected-cancer pathway where indicated. Document the lesion, palpation and nodes. Do not delay because it is painless or prescribe repeated empirical treatment without a review; tissue assessment may be needed to establish its nature.
Test your recall
What does leukoplakia mean clinically?
Show answer
It is a persistent white plaque that cannot be assigned to another defined disorder after appropriate assessment. It is a diagnosis of exclusion, not a histological grade. Dysplasia or carcinoma may be present, but the appearance alone cannot establish either.