
Potentially malignant disorders
Oral potentially malignant disorders are associated with an increased risk of oral cancer, but their course is variable. Clinical labels, histological dysplasia and invasive carcinoma describe different things. Learn to identify concerning change, interpret sampling limits and explain why surveillance remains necessary even after treatment.
Quick revision summary
Separate the vocabulary
Leukoplakia is a clinical diagnosis of exclusion for a persistent white plaque; erythroplakia and erythroleukoplakia describe unexplained red or mixed appearances. Dysplasia is a microscopic assessment of epithelial architectural and cellular abnormality.
Plan representative biopsy
Select tissue that answers the question and captures the most concerning viable area. Larger heterogeneous lesions may need more than one mapped sample. A small superficial specimen may miss invasion or a higher-grade region.
Maintain meaningful surveillance
Compare the whole mouth and lesion map over time. New focal ulceration, induration, a nodule, increasing size, persistent pain or a neck lump should prompt reassessment and possible re-biopsy. Stable colour alone is insufficient.
Common mistake
Dysplasia is a tissue diagnosis, while leukoplakia is a clinical label. Removal of one patch does not guarantee freedom from cancer elsewhere or later.
Potentially malignant disorders: risk, biopsy and surveillance
Oral potentially malignant disorders are associated with an increased risk of oral cancer, but their course is variable. Clinical labels, histological dysplasia and invasive carcinoma describe different things. Learn to identify concerning change, interpret sampling limits and explain why surveillance remains necessary even after treatment.
Separate the vocabulary
Leukoplakia is a clinical diagnosis of exclusion for a persistent white plaque; erythroplakia and erythroleukoplakia describe unexplained red or mixed appearances. Dysplasia is a microscopic assessment of epithelial architectural and cellular abnormality. Invasive carcinoma has breached the epithelial boundary into underlying tissue.
The terms are not interchangeable. A white patch may contain no dysplasia, while a small red or mixed lesion can contain advanced disease. “Potentially malignant” means increased risk, not an inevitable progression or a promise that an initially reassuring specimen will remain representative indefinitely.
Leukoplakia: a focal white plaque
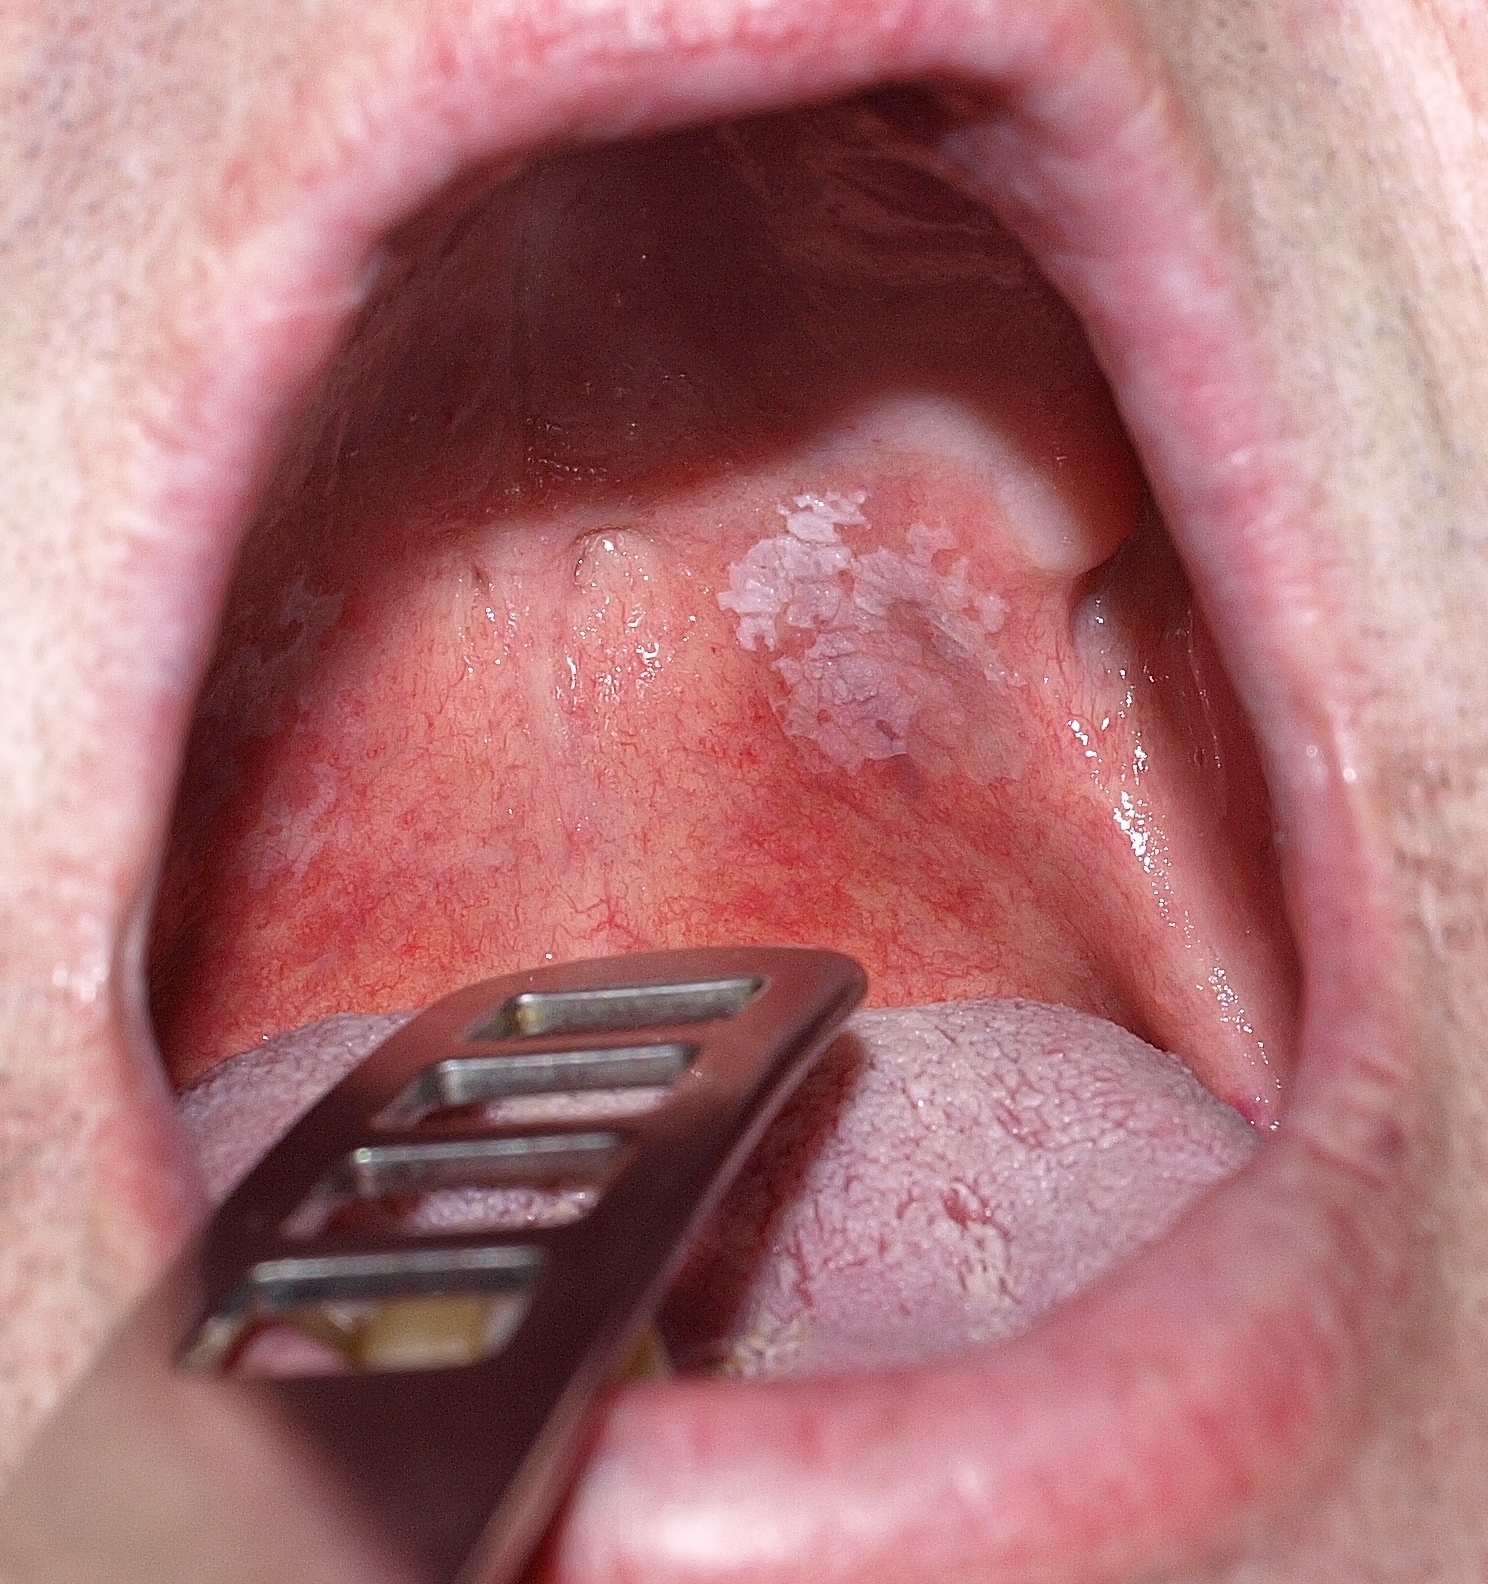
Describe the plaque’s site, outline, surface and surrounding mucosa before proposing a diagnosis. The source calls this lesion leukoplakia and reports that malignancy was excluded histologically in that case. That result cannot be inferred from its appearance or applied to another patient; white colour alone does not establish benignity.
Orale_Leukoplakie.jpg · Klaus D. Peter, Gummersbach, Germany · CC BY 3.0 DE. Source image reproduced without alteration; any arrows or circles are part of the original.
Can this photograph tell you whether the plaque contains epithelial dysplasia?
No. Dysplasia is a histological assessment. Clinical features guide the differential, urgency and sampling, but the photograph alone cannot grade or exclude it.
Recognise the wider group of disorders
Relevant entities include leukoplakia, erythroplakia, oral lichen planus and lichenoid disorders, oral submucous fibrosis and other defined conditions. Submucous fibrosis is associated with areca exposure and can cause mucosal blanching, fibrous bands and restricted opening. A history should include products used culturally or intermittently, not only cigarettes.
Proliferative verrucous leukoplakia describes a progressive multifocal process requiring specialist longitudinal assessment. Ordinary frictional keratosis is not assigned the same framework simply because it is white. Establish a careful diagnosis and distribution before discussing risk or deciding on surveillance.
Assess lesion and patient risk
Record site, dimensions, number, surface, homogeneous or non-homogeneous appearance, ulceration and palpation. Focal redness, nodularity, induration, progressive change and a suspicious lymph node need particular attention. A lesion can be important despite being painless or occurring in someone without tobacco or alcohol exposure.
Assess immune context, previous dysplasia or cancer and relevant exposures. Explain that risk estimates come from heterogeneous cohorts and do not predict an individual outcome with precision. Histological grade informs management, but sampling, lesion behaviour and clinical-pathological fit also matter.
Plan representative biopsy
Select tissue that answers the question and captures the most concerning viable area. Larger heterogeneous lesions may need more than one mapped sample. A small superficial specimen may miss invasion or a higher-grade region. Avoid destroying diagnostic tissue with crush or excessive thermal artefact.
Provide clinical history, exact site and differential to the laboratory. Histological dysplasia can be reported using grades such as mild, moderate and severe or a binary low/high framework; understand the terminology in the actual report. Ask for clarification when wording or adequacy leaves management uncertain.
Match management to diagnosis and morbidity
Specialist decisions may include risk-factor modification, observation with surveillance, excision or other lesion-directed treatment. Grade, size, site, multifocality, change, patient health and functional consequences influence the balance. Removing tissue can provide more information and local control, but larger procedures can cause significant morbidity.
A low-grade result does not automatically require surgery, and a high-risk changing lesion should not be managed by generic annual reassurance. Avoid presenting one procedure as a guaranteed way to prevent all future cancer. The surrounding mucosa and other sites can remain at risk.
Use the referral pathway correctly
Unexplained ulceration persisting beyond three weeks is a NICE suspected-cancer trigger. A suspicious oral lump or a red/red-white patch consistent with erythroplakia or erythroleukoplakia also requires the relevant assessment and referral. Strong clinical concern can justify earlier action rather than waiting for a duration threshold.
Do not postpone referral while cycling through antifungal or steroid trials in a suspicious lesion. Explain the reason for urgency clearly and sensitively, without claiming a cancer diagnosis before investigation. Track the referral and provide instructions if symptoms change while the patient is awaiting assessment.
Maintain meaningful surveillance
Compare the whole mouth and lesion map over time. New focal ulceration, induration, a nodule, increasing size, persistent pain or a neck lump should prompt reassessment and possible re-biopsy. Stable colour alone is insufficient. Record who provides surveillance and how urgent re-entry to specialist care works.
Support tobacco and areca cessation and reduction of hazardous alcohol exposure. Explain that recurrence or new lesions can occur after apparent removal and that follow-up is part of treatment. The patient should leave understanding both the uncertainty and the practical actions they can take.
A distinction to remember
Dysplasia is a tissue diagnosis, while leukoplakia is a clinical label. Removal of one patch does not guarantee freedom from cancer elsewhere or later.
A large white patch has a new red nodule despite a previous nondysplastic biopsy. What should happen?
Reveal the reasoning
Reassess promptly and arrange specialist review with targeted biopsy when indicated. The new component may not have been sampled previously and can represent changed disease. A prior reassuring specimen does not establish the nature of an evolving area indefinitely.
Test your recall
How do dysplasia and invasive carcinoma differ?
Show answer
Dysplasia describes epithelial architectural and cellular abnormalities without established invasion in the sampled tissue. Invasive carcinoma extends into underlying tissue. The distinction requires adequate histology, and a limited sample may not represent the deepest or highest-risk part of a heterogeneous lesion.