
Oral cancer
Most oral cavity cancers are squamous cell carcinomas, but other malignancies occur. Dental teams contribute through early recognition, appropriate referral, pretreatment optimisation and lifelong prevention. Understand the distinction between diagnosis, stage and grade, and how treatment affects the mouth beyond the original tumour site.
Quick revision summary
Recognise the range of presentations
A persistent ulcer, indurated patch, exophytic mass, unexplained red/red-white lesion, non-healing extraction site or unexplained tooth mobility can represent oral malignancy. Pain may be absent early. Sensory change, fixation, dysphagia, reduced tongue mobility or a neck lump may indicate deeper or regional disease.
Distinguish stage, grade and important pathology
TNM describes the primary tumour, regional nodes and distant metastasis. Oral cavity staging incorporates size and depth of invasion, while nodal assessment includes features such as extranodal extension. Clinical stage and pathological stage use different available information and can differ after surgery.
Support long-term recovery and surveillance
Radiotherapy can cause salivary dysfunction, increased caries risk, fibrosis, trismus and osteoradionecrosis risk; surgery can change anatomy and function. These risks vary with field, dose and individual treatment. High-risk dental care needs an agreed specialist-supported plan rather than an assumption that treatment effects end when oncology appointments stop.
Common mistake
Painlessness and absence of classic exposures do not exclude oral cancer. Stage, histological grade and dysplasia are different concepts.
Oral cancer: recognition, staging and the dental pathway
Most oral cavity cancers are squamous cell carcinomas, but other malignancies occur. Dental teams contribute through early recognition, appropriate referral, pretreatment optimisation and lifelong prevention. Understand the distinction between diagnosis, stage and grade, and how treatment affects the mouth beyond the original tumour site.
Recognise the range of presentations
A persistent ulcer, indurated patch, exophytic mass, unexplained red/red-white lesion, non-healing extraction site or unexplained tooth mobility can represent oral malignancy. Pain may be absent early. Sensory change, fixation, dysphagia, reduced tongue mobility or a neck lump may indicate deeper or regional disease.
Examine the entire mouth systematically and palpate the lesion and relevant neck nodes. Record exact site, size, surface, borders, induration and functional effects. Ask about duration, change, weight loss and exposures. A patient without tobacco or alcohol history can still have oral cancer.
Head and neck lymphatic glands (Gray's Anatomy, plate 602)
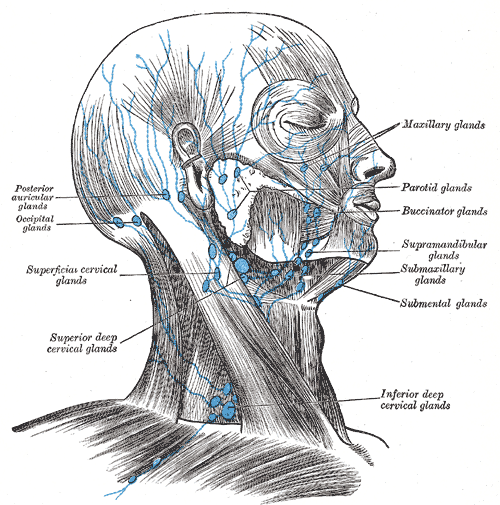
Find the submental and submandibular groups and follow drainage toward the cervical nodes. In this historical figure, ‘glands’ means lymph nodes and ‘submaxillary’ means submandibular. Use current cancer guidance for modern oncological neck levels.
Head and neck lymphatic glands (Gray's Anatomy, plate 602) · Henry Vandyke Carter; reproduced in Henry Gray, Anatomy of the Human Body (1918), plate 602 · Public domain. Unchanged published image; displayed responsively.
Understand site and risk
Oral cavity sites include the mobile tongue, floor of mouth, buccal mucosa, gingiva, retromolar region and hard palate. The tongue base and tonsillar region belong to the oropharynx and have different anatomical and oncological frameworks. HPV has a particular role in oropharyngeal cancer; it should not be used as a universal explanation for all oral cancers.
Tobacco, alcohol and areca exposure are important preventable risks, while ultraviolet exposure relates to the external lip. Ask sensitively about the actual products used. Risk history informs assessment but must not be used as a gatekeeper that excludes referral in a younger or otherwise low-risk person.
Cervical lymph nodes and anatomical levels
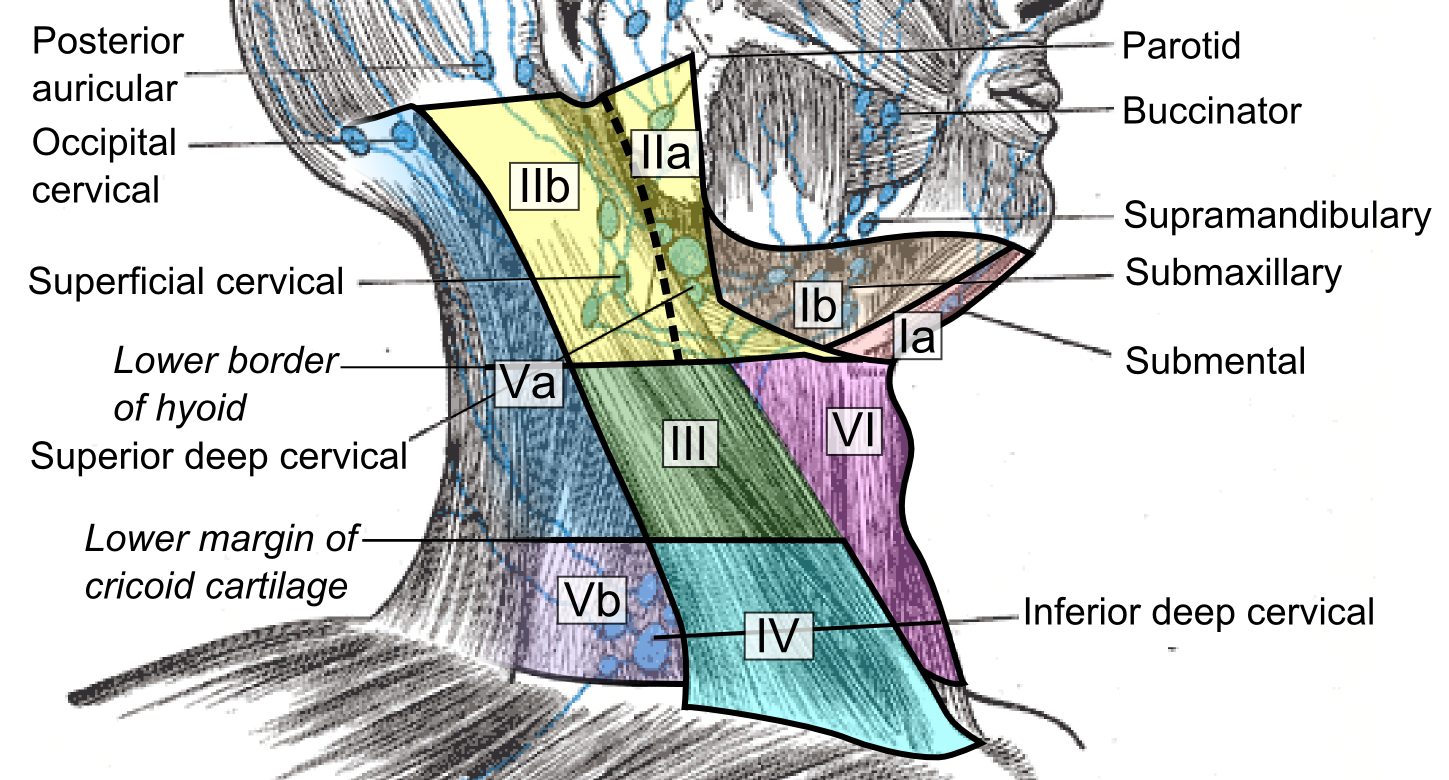
Compare the named node groups with the numbered cervical levels. This schematic does not replace cross-sectional imaging criteria for staging or treatment planning.
Cervical lymph nodes and levels.png · Mikael Häggström, M.D. · CC0. None; reproduced without alteration.
What should you record about a clinically palpable cervical node?
Its exact site and laterality, size, tenderness, consistency and mobility, alongside the relevant oral examination and history.
Refer and establish the diagnosis
Use the local suspected-cancer pathway for concerning findings, including unexplained oral ulceration beyond three weeks and relevant suspicious lumps or red/red-white patches. Do not wait for that threshold where the clinical suspicion is already strong. Explain the reason for referral and track its completion.
Definitive diagnosis requires appropriate tissue assessment, with representative biopsy planned to preserve later treatment. The report must fit the clinical lesion. A superficial or nonspecific sample cannot safely close the pathway if the lesion remains suspicious. Imaging characterises extent but does not replace histology.
Leukoplakia: a focal white plaque
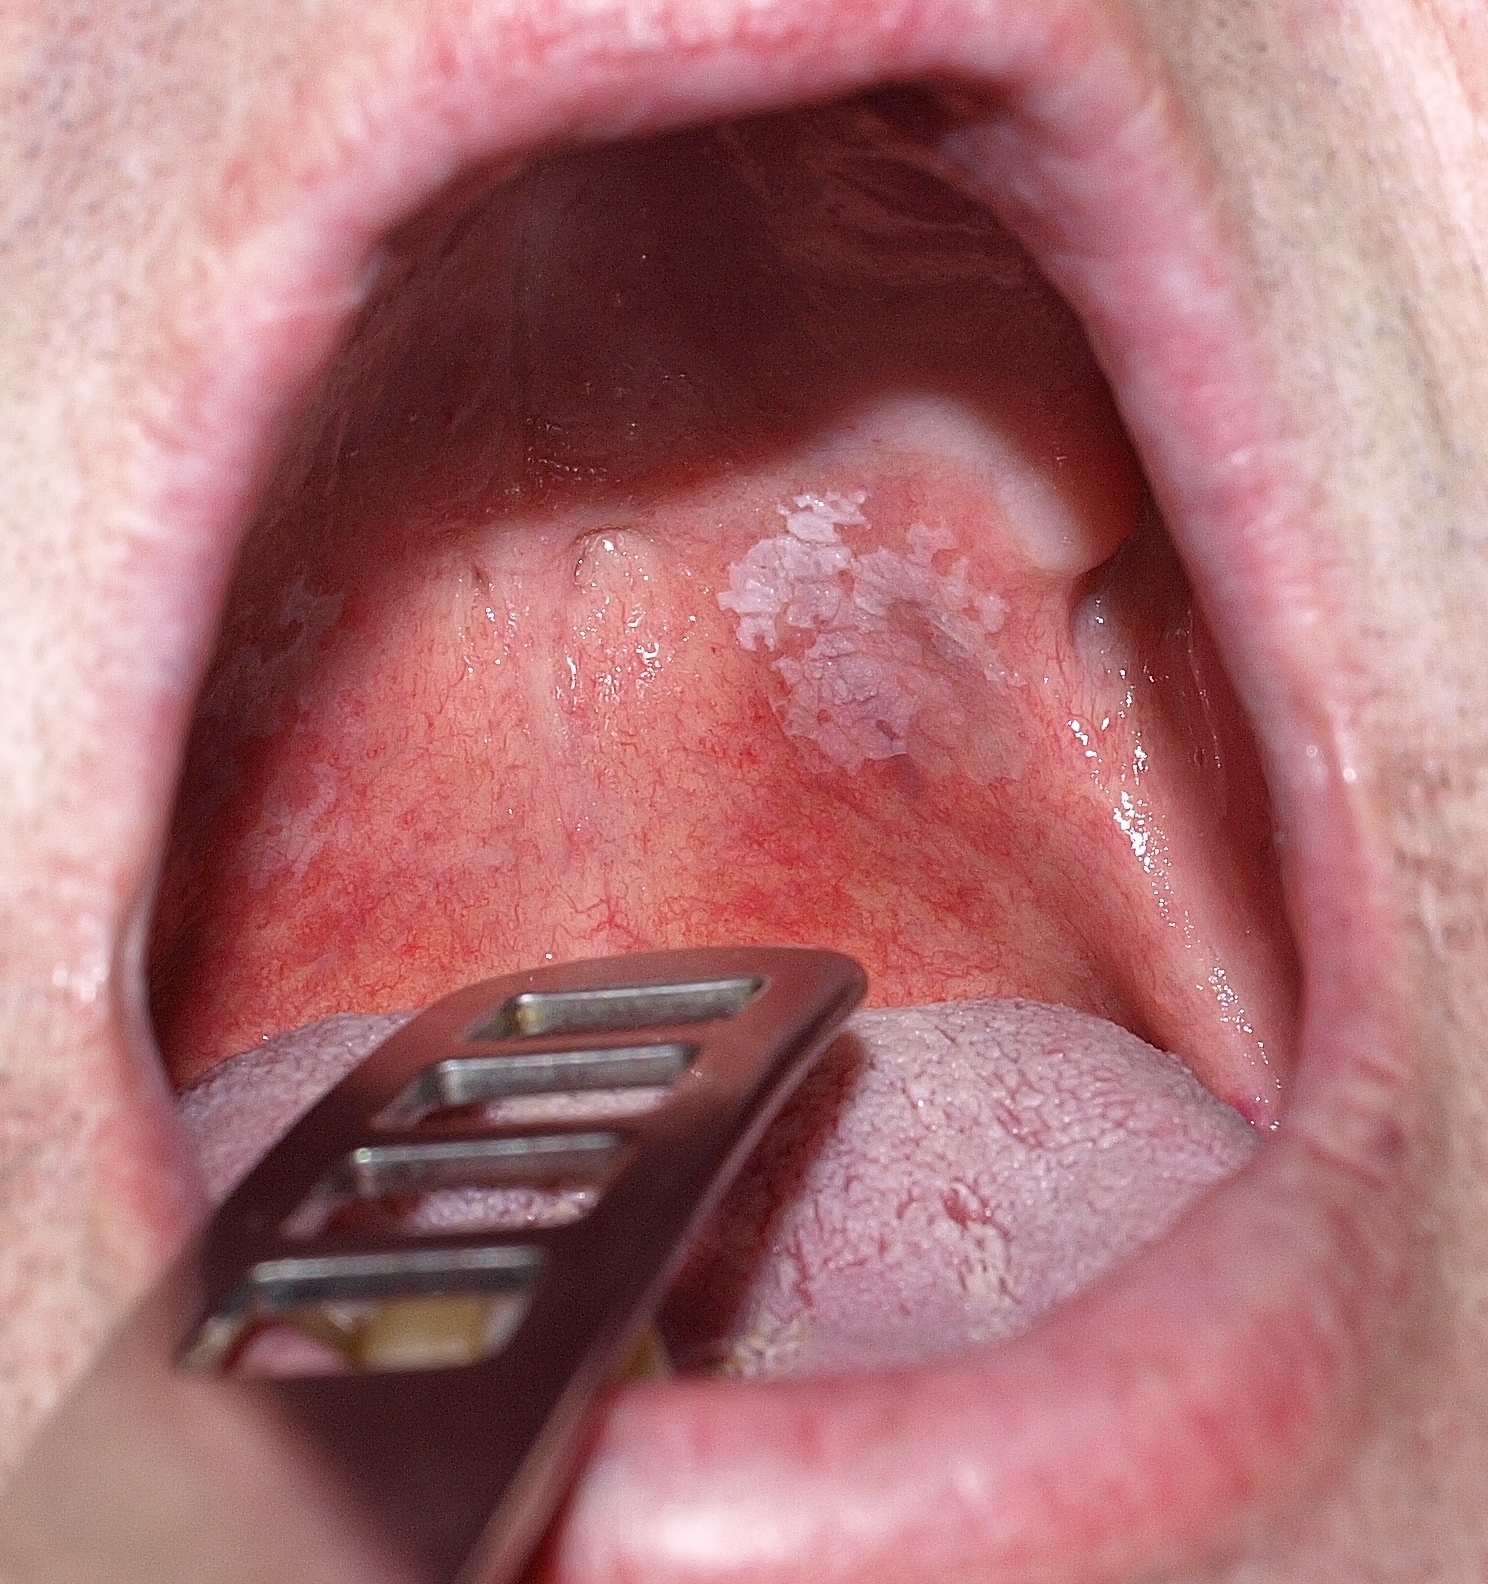
Describe the plaque’s site, outline, surface and surrounding mucosa before proposing a diagnosis. The source calls this lesion leukoplakia and reports that malignancy was excluded histologically in that case. That result cannot be inferred from its appearance or applied to another patient; white colour alone does not establish benignity.
Orale_Leukoplakie.jpg · Klaus D. Peter, Gummersbach, Germany · CC BY 3.0 DE. Source image reproduced without alteration; any arrows or circles are part of the original.
Can this photograph tell you whether the plaque contains epithelial dysplasia?
No. Dysplasia is a histological assessment. Clinical features guide the differential, urgency and sampling, but the photograph alone cannot grade or exclude it.
Distinguish stage, grade and important pathology
TNM describes the primary tumour, regional nodes and distant metastasis. Oral cavity staging incorporates size and depth of invasion, while nodal assessment includes features such as extranodal extension. Clinical stage and pathological stage use different available information and can differ after surgery.
Grade describes microscopic differentiation and is not the same as stage. Depth of invasion is not simply tumour thickness. Margins, perineural or lymphovascular invasion and nodal findings help the MDT interpret prognosis and further treatment. Use the current site-specific staging edition rather than transferring an oropharyngeal rule to an oral cavity primary.
Lower-lip squamous cell carcinoma
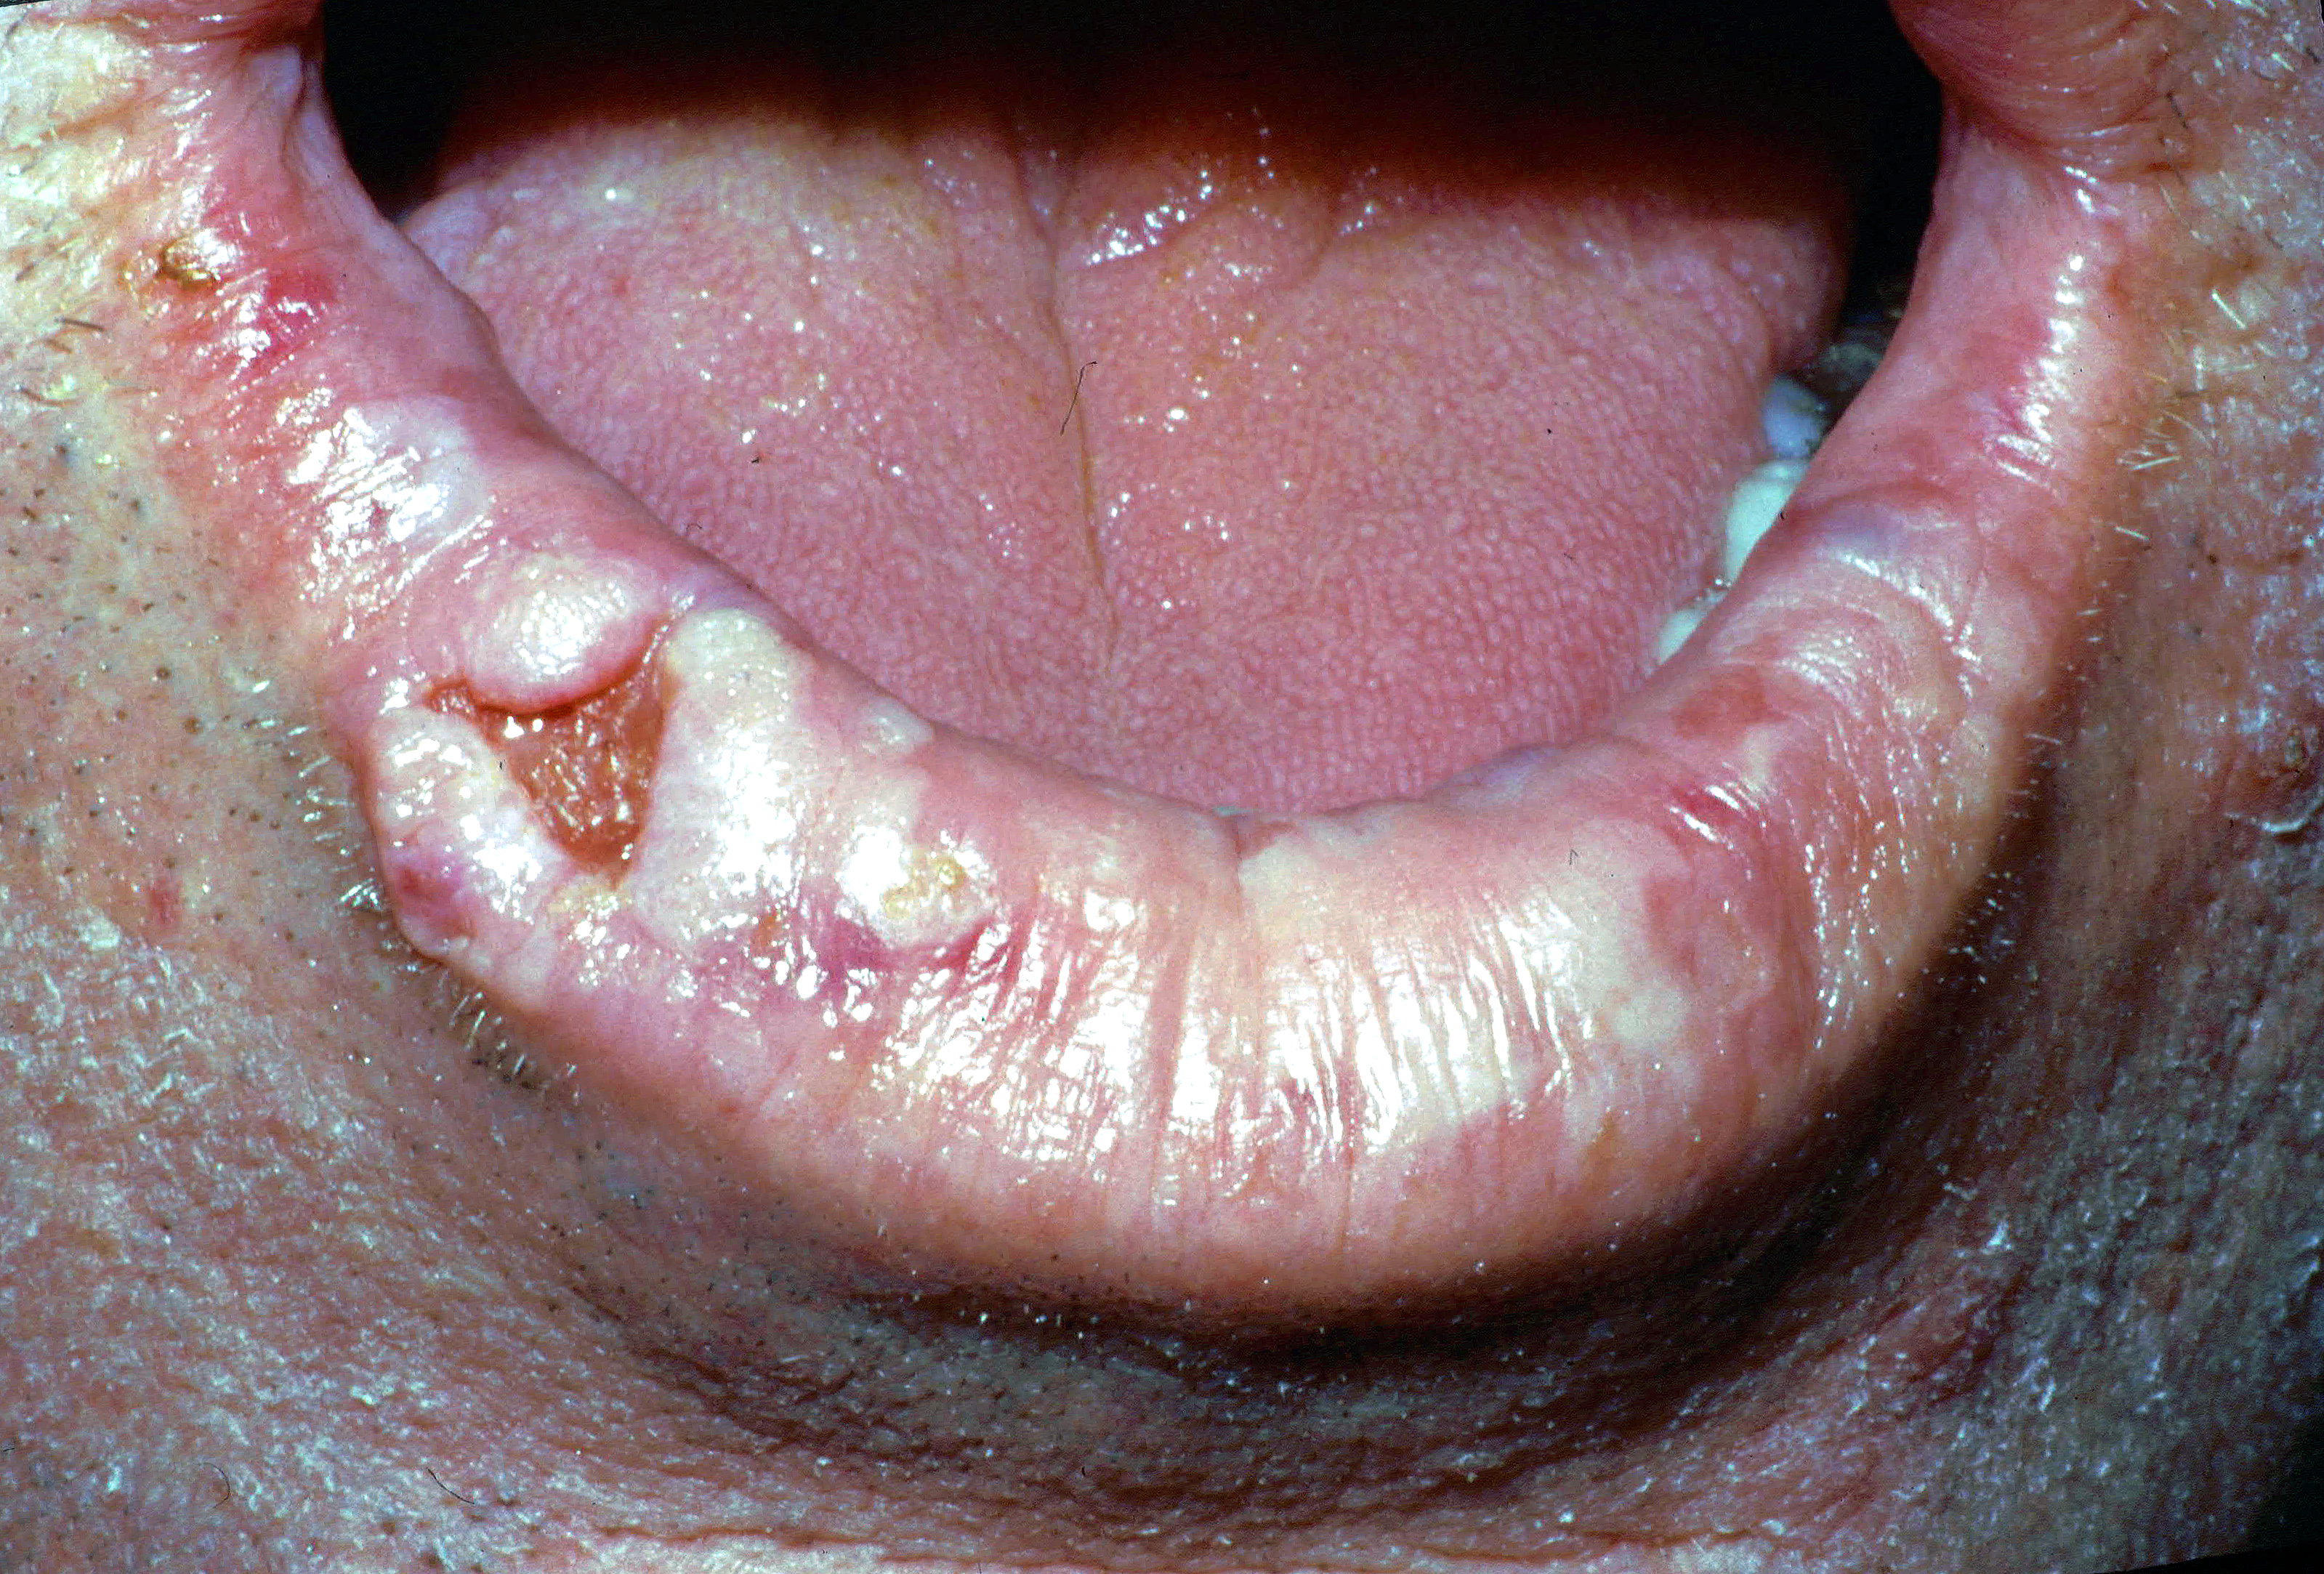
The source diagnosis is squamous cell carcinoma of the right lower lip. Describe the irregular ulcerated area, raised tissue and surrounding lip change. A clinical assessment also needs palpation, duration, progression, nodes and relevant exposures. A photograph cannot establish tumour depth or stage.
Lower lip cancer.jpg · Coronation Dental Specialty Group · CC BY-SA 4.0. Reproduced without alteration. Labels, arrows and circles, where present, belong to the source image.
Which important examination findings cannot be judged reliably from this photograph?
Induration, fixation, depth and regional lymph-node findings require clinical assessment. Tissue diagnosis and appropriate staging investigations add information that a surface photograph cannot supply.
See treatment as a multidisciplinary decision
The MDT combines site, extent, pathology, resectability, comorbidity, function and patient priorities. Surgery, radiotherapy and systemic therapy have different roles and may be combined. Neck management may be necessary even without an obvious palpable node, according to occult metastatic risk and the specialist plan.
Reconstruction, speech and swallowing rehabilitation, nutrition, psychological support and restorative dentistry belong in treatment planning. A technically successful resection is not the only outcome. Discuss likely consequences and uncertainty, and support smoking cessation and other risk reduction without implying that the patient caused their disease.
Prepare dental care around cancer treatment
Assess teeth, periodontal health, infection, restorability and the anticipated radiation field or systemic therapy. Coordinate necessary care with oncology so that preventable dental complications are reduced without an unjustified delay to cancer treatment. Decisions about extractions, healing and invasive treatment require the actual cancer plan.
The RCS February 2026 guidance emphasises coordinated care before, during and after treatment. Prevention should include effective gentle plaque control, fluoride and diet advice compatible with nutritional needs. Blood-cell abnormalities, immune suppression, mucositis and treatment timing can change what is appropriate during systemic therapy.
Support long-term recovery and surveillance
Radiotherapy can cause salivary dysfunction, increased caries risk, fibrosis, trismus and osteoradionecrosis risk; surgery can change anatomy and function. These risks vary with field, dose and individual treatment. High-risk dental care needs an agreed specialist-supported plan rather than an assumption that treatment effects end when oncology appointments stop.
Maintain risk-based preventive review and assess new lesions, unexplained pain, sensory change or progressive restriction. Distinguish recurrence, a second primary, treatment effects and ordinary dental disease through appropriate investigation. A longstanding cancer history must not make new symptoms invisible, and routine dentistry remains important after specialist discharge.
A distinction to remember
Painlessness and absence of classic exposures do not exclude oral cancer. Stage, histological grade and dysplasia are different concepts.
A painless ulcer has persisted for a month in a non-smoker. Should the lack of pain and smoking history lower referral urgency?
Reveal the reasoning
No. Assess and document the ulcer and arrange the appropriate suspected-cancer referral for unexplained persistence or suspicious features. These risk factors are not required for oral cancer. Avoid delaying referral with repeated empirical treatment simply because the patient lacks a conventional profile.
Guidance to read alongside this chapter
- NICE NG12 · Suspected oral cancer referral
- GOV.UK · Delivering better oral health: oral cancer
- NCI · Lip and oral cavity cancer: health professional treatment summary
- RCS Faculty of Dental Surgery · Oral and dental management before, during and after cancer therapy, February 2026
- RCPath · G110 oral cavity carcinoma reporting dataset
Test your recall
How does an oral cavity primary differ anatomically from an oropharyngeal primary?
Show answer
The mobile anterior tongue and oral floor are oral cavity sites, while the tongue base and tonsillar region are oropharyngeal. Their staging and biological frameworks differ. Correct site description prevents inappropriate transfer of HPV-related oropharyngeal assumptions to an oral cavity lesion.