
Facial pain and TMD
Facial pain may arise from teeth, muscles, joints, nerves or disease outside the dental field. The pain history and a reproducible examination should lead the diagnosis. TMD describes a group of musculoskeletal disorders; a click or incidental radiographic finding is not an explanation for every painful face.
THE ANATOMY LAB / INTERACTIVE 3DExplore the jaw and TMJ relationships in 3D↗Quick revision summary
Identify the pain pattern
Record onset, duration, site, triggers and functional impact. Test plausible dental causes and examine the masticatory system. Brief electric attacks, prolonged muscular pain and progressive unexplained pain require different diagnostic pathways.
Use reversible treatment for appropriate TMD
Explain the diagnosis, agree supported self-management and monitor pain and function. Appliances and medicines need a specific indication. Painless clicking alone does not justify occlusal adjustment, extensive restorative treatment or joint surgery.
Reassess atypical or worsening features
A mass, fever, neurological change, progressive trismus or jaw claudication changes the assessment. Screening tools support recognition but do not diagnose TMD. Persistent diagnostic uncertainty should prompt suitable referral before irreversible dental treatment.
Common mistake
A positive TMD screen, a joint click or an incidental dental finding does not establish the cause of pain. Repeated irreversible treatment is inappropriate without a defensible diagnosis.
Facial pain and TMD: diagnosis before irreversible treatment
Facial pain may arise from teeth, muscles, joints, nerves or disease outside the dental field. The pain history and a reproducible examination should lead the diagnosis. TMD describes a group of musculoskeletal disorders; a click or incidental radiographic finding is not an explanation for every painful face.
Build a pain history that separates mechanisms
Ask the patient to describe the pain in their own words before suggesting labels. Establish site, radiation, onset, episode duration, frequency, severity and triggers. Explore chewing, opening, touch, temperature, exertion and spontaneous episodes. Record headache symptoms and associated autonomic, sensory or systemic features. A pain diagram and diary can make a fluctuating history clearer.
Determine effects on eating, sleep, work and mood, and what treatments have already been tried. Pain can persist after the initiating tissue injury resolves, with altered processing and several contributing factors. A psychological or social contribution does not make symptoms imaginary. Avoid asking only whether a tooth is tender and assuming that tenderness establishes the primary cause.
Temporomandibular joint
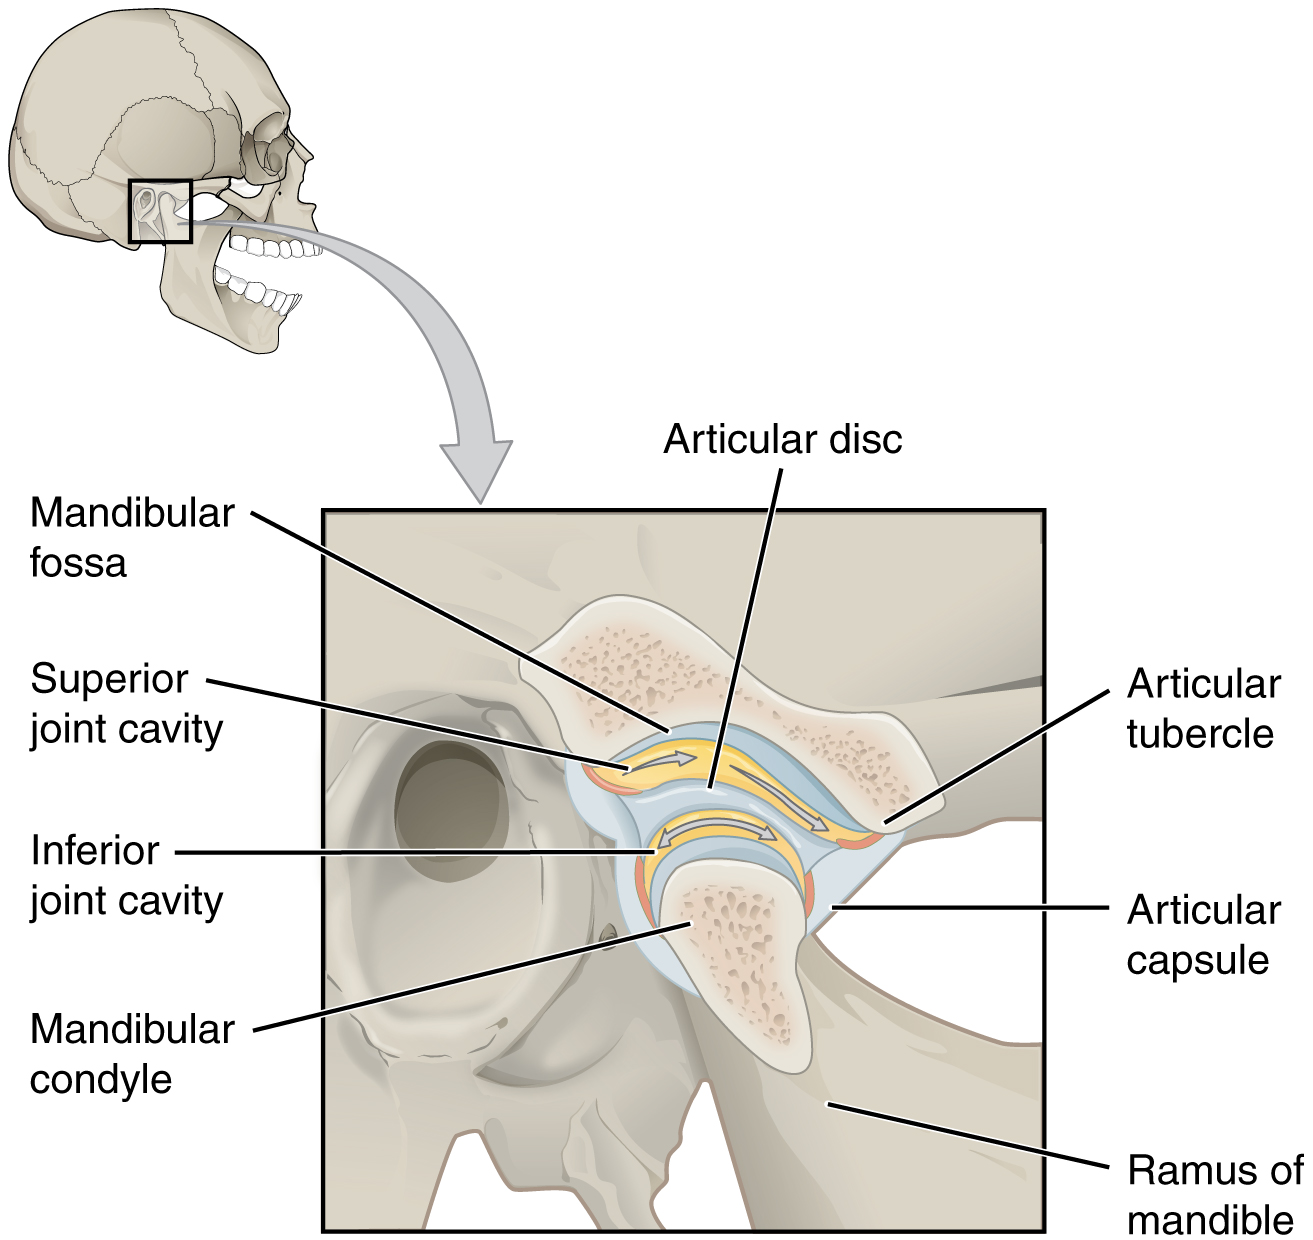
Identify the disc and the two joint compartments. Recall rotation versus translation, then connect the condyle and articular tubercle to dislocation and the disc to TMD assessment.
Temporomandibular joint · OpenStax College · CC BY 3.0. Original image; displayed at a responsive size. Original publication.
Test dental and serious alternatives first
Examine teeth, periodontium, mucosa and relevant extraoral structures, using sensibility tests, percussion and imaging when indicated. Correlate any abnormality with the actual pain. An incidental restoration or minor radiographic change may not explain widespread or intermittent symptoms. Repeated extraction or endodontic treatment without a coherent diagnosis can worsen the patient’s burden.
Fever with swelling, a mass, new neurological findings, unexplained weight loss or progressive severe trismus require an alternative pathway. New jaw claudication with headache or visual symptoms raises concern for giant cell arteritis and needs urgent medical assessment. Trauma, infection, cancer and inflammatory joint disease must not be hidden behind a TMD label.
Trigeminal divisions and facial sensory territories
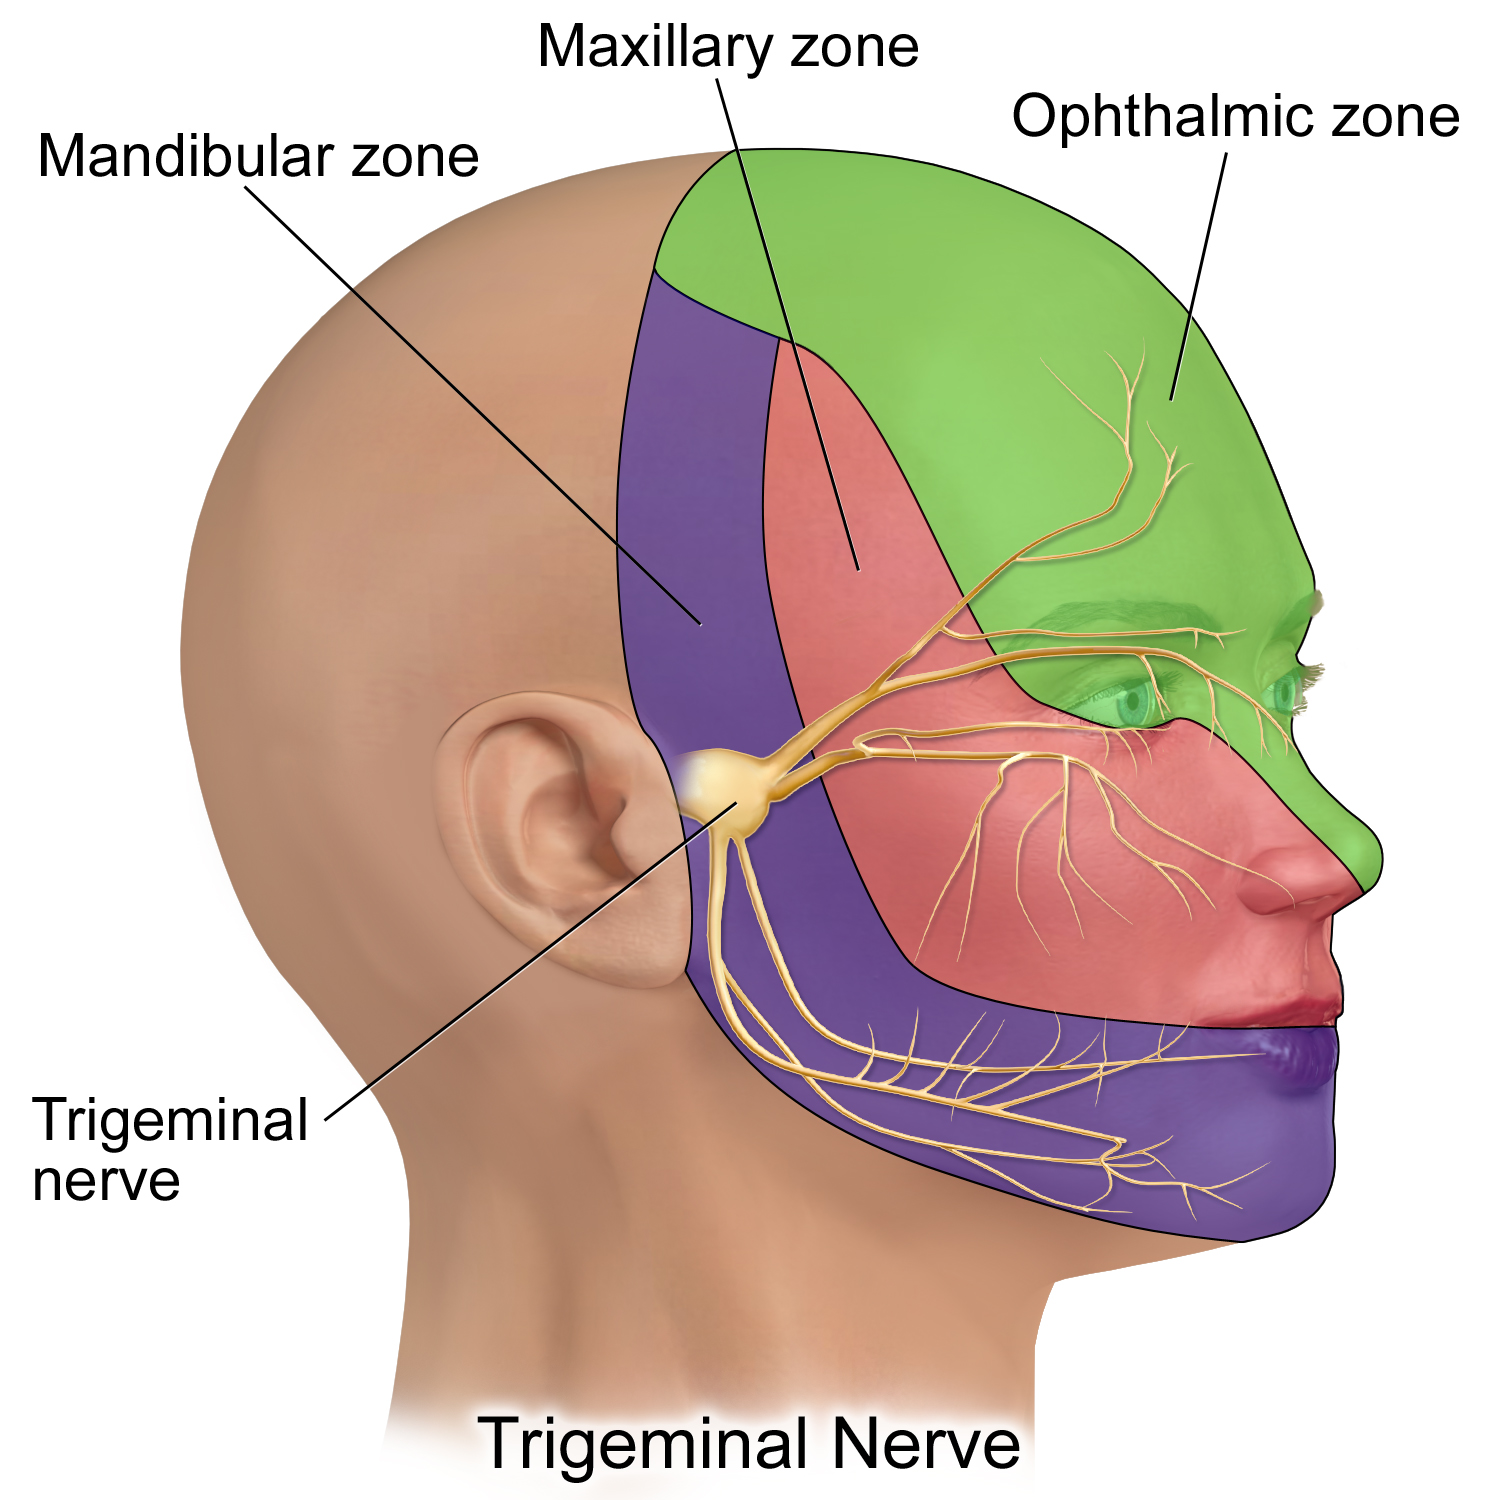
V1 is ophthalmic, V2 maxillary and V3 mandibular. This is a schematic sensory territory map, not a detailed map of every peripheral branch; V3 also carries motor fibres.
Trigeminal Nerve.png · BruceBlaus · CC BY-SA 4.0. None; reproduced without alteration.
Which division gives rise to the inferior alveolar and lingual nerves?
The mandibular division, V3. Distinguish lower lip/chin sensory change from altered tongue sensation.
Distinguish muscle pain from joint disorders
Myogenous pain arises in the masticatory muscles and may be reproduced as the patient’s familiar pain by appropriate palpation or movement. Arthralgia is joint pain associated with function and examination. These can coexist. Measure opening and excursions, document deviation or deflection, and assess the relevant muscles and joints rather than recording only that the TMJ is tender.
Disc displacement with reduction can produce clicking. Without reduction it may produce locking and restricted opening, although the relationship between disc position and symptoms is imperfect. Degenerative joint disease may produce crepitus. Dislocation, with difficulty closing after the condyle moves beyond its normal range, is a different acute problem requiring trained assessment and management.
Use screening and imaging for specific purposes
The 3Q/TMD instrument can identify people who need further assessment; it does not establish a diagnosis. Apply a structured clinical assessment and consider the broader differential. The August 2025 RCS/GIRFT guideline explicitly makes this distinction. Symptoms, disability and examination findings should determine the plan, not a screening score alone.
MRI can assess the disc and other soft-tissue questions when the result will change care. CT or CBCT may address selected bony questions. Routine imaging of every painless click is unnecessary. Severe arthrogenous symptoms with opening below 30 mm are among the guideline’s early referral considerations, but the complete clinical context and exclusion of other causes remain essential.
Start with supported self-management
For an appropriate uncomplicated TMD diagnosis, explain expected recovery and agree achievable measures: reducing aggravating load temporarily, avoiding repeated wide opening, suitable exercises and thermal measures, and addressing sleep or stress where relevant. Maintain nutrition and gradually restore function rather than prescribing indefinite avoidance of normal jaw use. Review progress with the patient’s own functional goals.
Physiotherapy and selected appliances or medicines may have a role. Check medical history, interactions and the evidence for the specific intervention. A splint is not proof that an occlusal defect caused the pain. Irreversible grinding, extensive crowns or surgery should not be offered simply to remove a click or because conservative care has not yet worked.
Recognise neuralgia and persistent non-dental pain
Trigeminal neuralgia typically causes brief, severe, electric-shock-like attacks in a trigeminal distribution, often triggered by light touch or everyday movements. Continuous pain can coexist. Dental triggers do not necessarily mean dental disease. A specialist diagnostic pathway includes assessment for secondary causes and usually MRI; sensory deficit, bilateral symptoms or other neurological signs increase concern.
Medical treatment, commonly using carbamazepine or oxcarbazepine under appropriate prescribing supervision, differs from ordinary dental analgesia. Persistent idiopathic facial pain and painful post-traumatic trigeminal neuropathy also require careful distinction and specialist support. When symptoms persist or change, revisit the diagnosis, document the examination and coordinate care rather than cycling through irreversible dental interventions.
A distinction to remember
A positive TMD screen, a joint click or an incidental dental finding does not establish the cause of pain. Repeated irreversible treatment is inappropriate without a defensible diagnosis.
Brief electric shocks across the cheek are triggered by washing the face. Dental examination is unremarkable. What diagnosis and next step should be considered?
Reveal the reasoning
Consider trigeminal neuralgia and arrange an appropriate medical or specialist facial-pain pathway, including assessment for secondary causes. Clarify the full history and neurological features. Avoid extracting or treating a tooth merely because some attacks are triggered inside the mouth.
Test your recall
What features help distinguish trigeminal neuralgia from typical TMD pain?
Show answer
Trigeminal neuralgia causes brief electric-shock-like attacks, often triggered by innocuous touch in a trigeminal distribution. TMD pain is commonly modified by jaw function and reproduced by relevant muscle or joint examination. Patterns can overlap, so neither description replaces a full assessment.