
Intraoral examination
Examine the whole mouth before narrowing to the presenting tooth. Inspection, palpation and targeted tests contribute different information; a systematic sequence prevents painful symptoms from hiding an unrelated but important finding.
Quick revision summary
Prepare, inspect systematically and record limitations
Explain the examination, obtain consent and use good lighting, a mirror, appropriate retraction and drying. Ask the patient to remove removable appliances so the supporting tissues and appliance surfaces can be examined.
Teeth, restorations, wear and structural prognosis
Chart the teeth present and distinguish primary from permanent teeth. Record caries by location, extent and clinically assessable activity, restorations and defects, fractures, developmental changes and exposed root surfaces. Use clean, dry visual assessment and indicated imaging rather than forcing a sharp probe into an early lesion to create a tactile diagnosis.
Turn findings into a problem list and next step
Integrate hard-tissue, soft-tissue, periodontal, functional and patient-reported findings. Separate definite observations from provisional diagnoses and note discrepancies. The painful tooth may need urgent care, while an unrelated mucosal finding or disease pattern needs another pathway.
Common mistake
BPE is a screen, a photograph is a surface record and a sensibility response is a neural test. Each is useful within its limits; none substitutes for the whole examination.
Intraoral examination
Examine the whole mouth before narrowing to the presenting tooth. Inspection, palpation and targeted tests contribute different information; a systematic sequence prevents painful symptoms from hiding an unrelated but important finding.
Prepare, inspect systematically and record limitations
Explain the examination, obtain consent and use good lighting, a mirror, appropriate retraction and drying. Ask the patient to remove removable appliances so the supporting tissues and appliance surfaces can be examined. Adapt the position and sequence for tolerance, restricted opening, disability or anxiety without recording inaccessible surfaces as normal.
Use a consistent route through lips, labial and buccal mucosa, gingivae, tongue, floor of mouth, palate and visible oropharynx. Inspect bilaterally and include surfaces hidden by folds or the tongue. The exact order can vary, but every relevant site needs coverage. A focused acute assessment may be necessary first, with a plan to complete what could not be examined.
Oral mucosa: epithelium, basement membrane and lamina propria
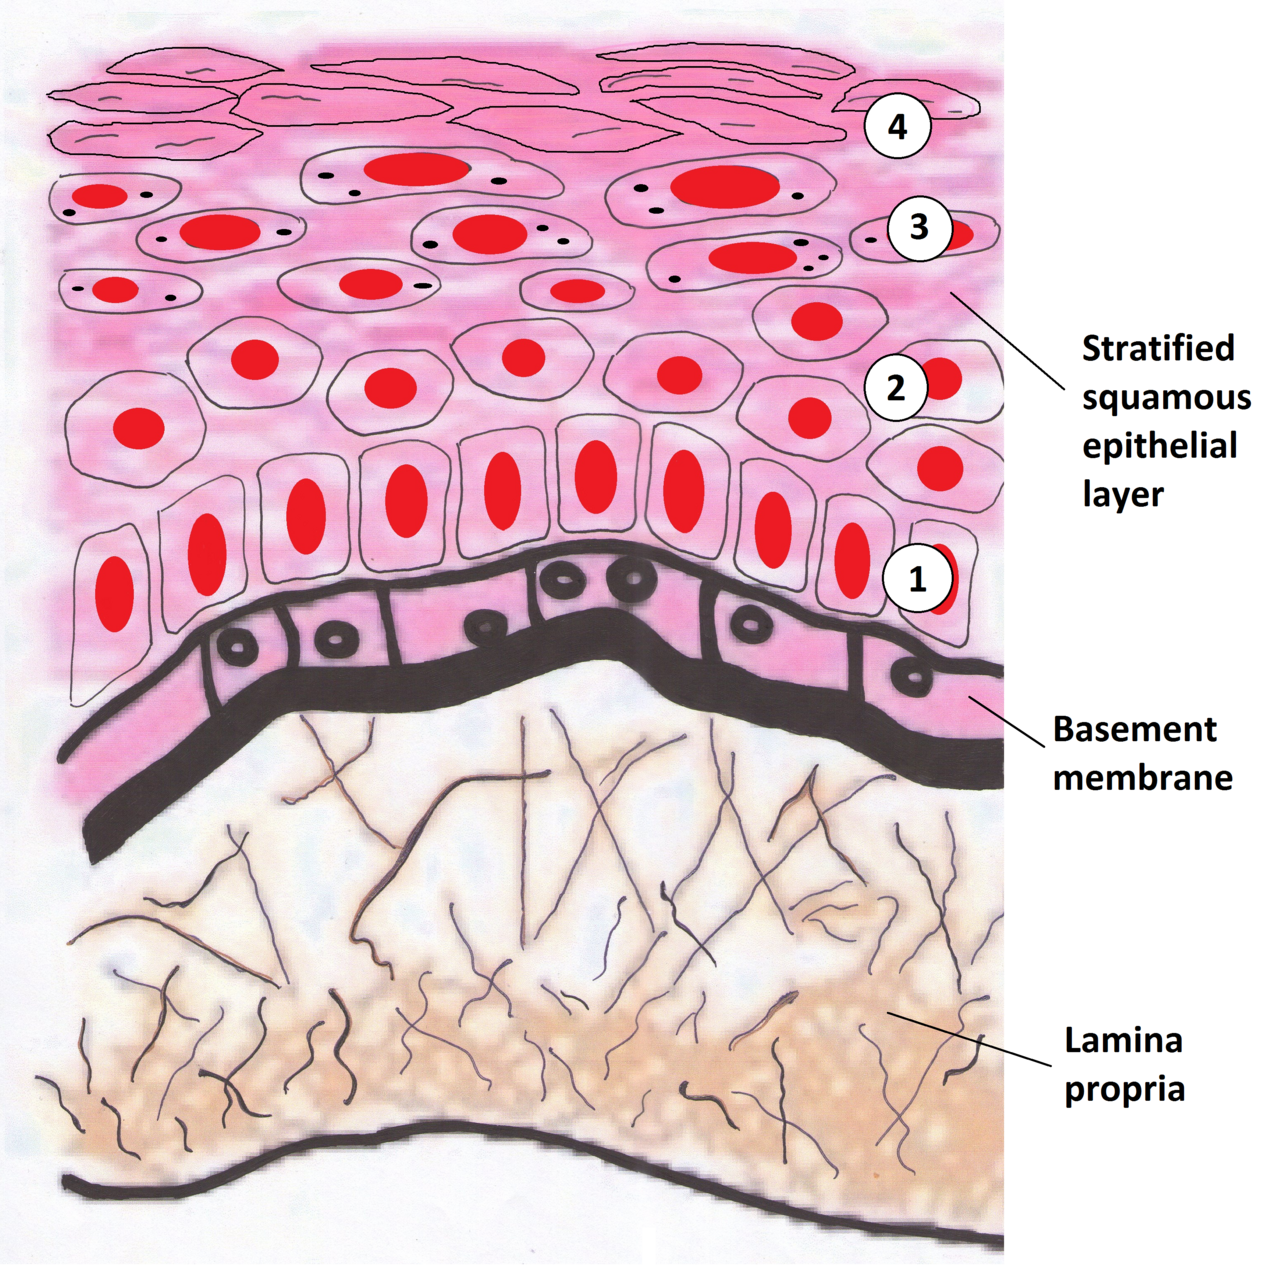
Identify the epithelium, basement membrane and lamina propria. Relate the epithelial–stromal interface to in-situ disease and invasion. This drawing represents a keratinising surface; oral sites have different keratinisation patterns. Use the printed anatomical names for revision.
Oral mucosa: epithelium, basement membrane and lamina propria · Wiki-minor (own work, 2011) · CC BY-SA 3.0. Unchanged published raster preview; displayed responsively. Original available from the source.
Describe mucosal findings before naming them
Record exact site and side, dimensions, colour, surface, border, distribution, tenderness and consistency where palpated. Use terms such as plaque, ulcer, erosion, nodule or vesicle precisely. Note whether a white deposit wipes away, whether there is a local traumatic contact and whether lesions occur at several sites. None of these features alone establishes a diagnosis.
Ask about duration, recurrence and change and relate the finding to the history. Photograph with appropriate consent and a scale where useful. A persistent indurated lesion, suspicious red or red-and-white patch or unexplained ulcer needs the appropriate prompt referral. Do not repeatedly attribute a lesion to trauma without confirming that it resolves after a plausible cause is removed.
Tongue, floor of mouth and salivary ducts
Inspect the dorsal, ventral and lateral tongue with suitable retraction. Ask for movement as indicated and distinguish limited movement caused by pain from weakness or mechanical restriction. Palpation can reveal induration or a deeper mass that is less obvious on surface inspection; perform it gently and explain what is being assessed.
Inspect floor-of-mouth symmetry, mucosal change, duct papillae and saliva. Appropriate bimanual palpation can assess submandibular tissue, the duct and some calculi. Compare gland and duct findings with meal-related swelling or dryness. Raised or tense floor-of-mouth tissues with dysphagia or rapidly spreading infection change urgency and should not be treated as a routine gland examination.
Teeth, restorations, wear and structural prognosis
Chart the teeth present and distinguish primary from permanent teeth. Record caries by location, extent and clinically assessable activity, restorations and defects, fractures, developmental changes and exposed root surfaces. Use clean, dry visual assessment and indicated imaging rather than forcing a sharp probe into an early lesion to create a tactile diagnosis.
Describe tooth wear by site, severity and pattern and consider erosion, attrition and abrasion as interacting mechanisms. Cracks, remaining cusps, root condition and margins influence restorability. A radiographic shadow or stained fissure must be interpreted with clinical findings. A chart of surfaces alone does not establish disease activity, pulp status or the prognosis of a strategic tooth.
Periodontal screening and detailed assessment
Assess plaque, gingival inflammation, bleeding, recession, mobility and relevant local factors. BPE is a screening tool for appropriate adult patients; it does not replace a periodontal diagnosis or a full examination when indicated. Patients already diagnosed with periodontitis need assessment suited to monitoring that disease rather than being returned to a screening-only pathway.
Under current SDCEP advice, scores 3, 4 or furcation involvement require further periodontal examination, with the timing and extent depending on the finding. Detailed assessment includes site-specific probing and attachment information, bleeding, furcations and appropriate radiographic interpretation. An isolated deep pocket may also reflect a crack or local defect, so interpret the distribution.
| Assessment | Main information | Limit |
|---|---|---|
| Clean, dry inspection | Surface morphology and accessible lesion features | Cannot show the full depth of every lesion |
| Palpation | Induration, depth, tenderness and consistency | Does not replace histological diagnosis |
| BPE | Periodontal screening findings by sextant | Not a full disease diagnosis or treatment-response chart |
| Targeted tooth tests | Pulpal, apical, periodontal or structural clues | No single result explains every tooth symptom |
Occlusion, appliances and targeted special tests
Assess static and functional relationships relevant to the complaint and plan: contacts, overjet, overbite, crossbites, space and excursions. For a prosthesis, examine fit, support, retention, stability, cleanliness, occlusion and the condition of supporting tissues. A denture can appear intact yet cause trauma or be difficult to clean.
Cold and electrical tests, percussion, palpation, bite testing, transillumination and periodontal probing answer different questions. Choose tests to discriminate plausible diagnoses and compare appropriate controls. Justify imaging for an unresolved question. Do not turn an examination into an indiscriminate test battery or assume that every normal radiograph excludes early disease.
Turn findings into a problem list and next step
Integrate hard-tissue, soft-tissue, periodontal, functional and patient-reported findings. Separate definite observations from provisional diagnoses and note discrepancies. The painful tooth may need urgent care, while an unrelated mucosal finding or disease pattern needs another pathway. Record both rather than allowing the presenting complaint to determine the entire scope.
For anything monitored, state what will be reviewed and when, the expected change and what requires earlier assessment. For unexamined areas, record the reason and plan for completion. A useful negative entry names what was actually examined; it should not imply that an inaccessible posterior site or a deep structure was assessed by a quick glance.
A distinction to remember
BPE is a screen, a photograph is a surface record and a sensibility response is a neural test. Each is useful within its limits; none substitutes for the whole examination.
During an appointment for molar pain you find an indurated lateral tongue ulcer present for a month. What should the problem list contain?
Reveal the reasoning
Record the dental complaint and the separate persistent suspicious mucosal lesion. The ulcer needs prompt assessment through the appropriate pathway rather than being explained by the painful tooth. Document its morphology, duration and relevant neck findings while arranging diagnosis-specific dental care.
Guidance to read alongside this chapter
Test your recall
Why should a denture be removed during an oral examination?
Show answer
The fitting surface and covered mucosa cannot otherwise be assessed adequately. Removal permits inspection for trauma, inflammation, hygiene problems and unrelated lesions. An intact-looking denture or an asymptomatic patient does not establish that its supporting tissues are healthy.