
History taking
A useful history establishes the patient’s problem in their own words and then tests possible explanations. It also identifies medical, practical and communication factors that change how assessment and treatment can be delivered.
Quick revision summary
Open the consultation and agree the agenda
Confirm identity, introduce the team and establish how the patient prefers to communicate. Ask an open question about the reason for attending, allow the initial account and then clarify the main concern.
Medical history: ask what is active now
Record diagnoses, stability, relevant hospital care and the actual effect of disease on activity. A condition’s name alone rarely establishes procedural risk. Ask about cardiovascular and respiratory disease, diabetes, renal or liver impairment, bleeding, immune suppression, cancer treatment and other conditions relevant to the proposed care.
Summarise, verify and make the record useful
Summarise the important chronology back to the patient and invite corrections. Separate what the patient reports, what a carer or record supplies and what remains uncertain. Identify the leading diagnostic questions and the examination needed to resolve them.
Common mistake
The symptom label “toothache” is not a diagnosis. Record the episode duration, triggers, chronology and patient priorities before narrowing the explanation.
History taking
A useful history establishes the patient’s problem in their own words and then tests possible explanations. It also identifies medical, practical and communication factors that change how assessment and treatment can be delivered.
Open the consultation and agree the agenda
Confirm identity, introduce the team and establish how the patient prefers to communicate. Ask an open question about the reason for attending, allow the initial account and then clarify the main concern. A patient requesting an extraction may be seeking relief from pain rather than having made an informed choice between treatment options.
Ask what they think is happening, what worries them and what they hope treatment will achieve. Check for additional concerns before concentrating on one tooth. Privacy, an interpreter, accessible language or support may be needed to obtain a reliable account. Address the patient directly even when a relative or carer helps provide information.
Trigeminal nerve & dental branches
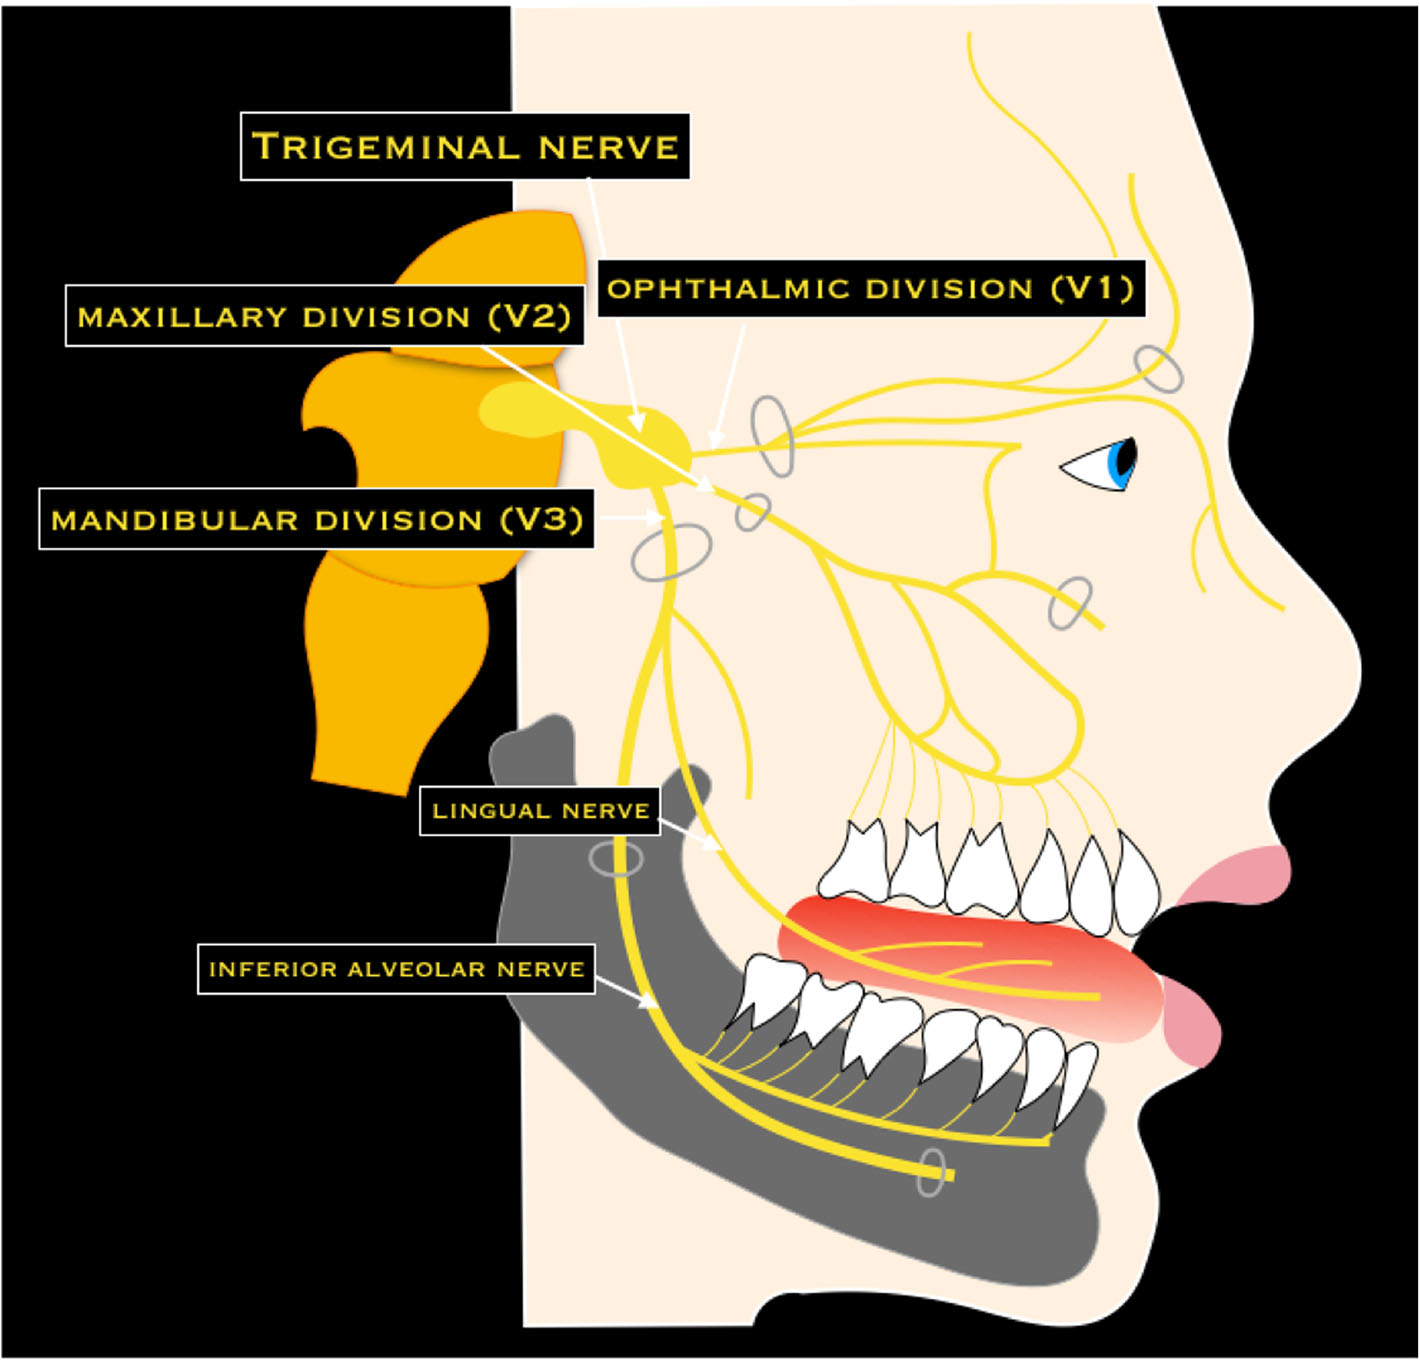
Trace V1, V2 and V3, then the lingual and inferior alveolar nerves. Connect each to the sensory examination after lower third-molar surgery. This is a branch overview, rather than an injection-placement diagram.
Trigeminal nerve & dental branches · Nicola Romano, Margherita Federici and Antonio Castaldi · CC BY 4.0. Original image; displayed at a responsive size. Original publication.
Build a chronological account of the presenting problem
Establish onset, progression and previous episodes. For pain, distinguish the date symptoms began from the duration of each episode; ask about site, radiation, quality, severity, triggers, relief and effects on sleep, eating and daily function. Ask the patient to point to the location without assuming that their localisation identifies the diseased tooth.
For swelling, ask whether it fluctuates, relates to meals, grows progressively or follows an infection or injury. For a mucosal lesion, ask about persistence versus recurrence, whether sites change and whether complete healing occurs between episodes. Previous investigations and treatments matter, but response to an antibiotic or restoration does not by itself prove the original diagnosis.
Head and neck lymphatic glands (Gray's Anatomy, plate 602)
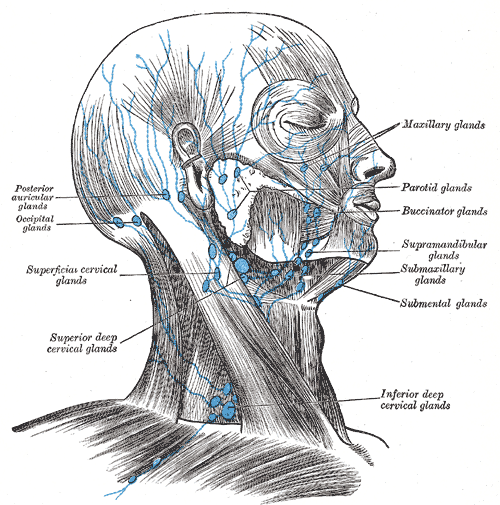
Find the submental and submandibular groups and follow drainage toward the cervical nodes. In this historical figure, ‘glands’ means lymph nodes and ‘submaxillary’ means submandibular. Use current cancer guidance for modern oncological neck levels.
Head and neck lymphatic glands (Gray's Anatomy, plate 602) · Henry Vandyke Carter; reproduced in Henry Gray, Anatomy of the Human Body (1918), plate 602 · Public domain. Unchanged published image; displayed responsively.
Use focused questions to separate mechanisms
Brief pain on cold, lingering pain after the stimulus, pain on biting, meal-related gland swelling and short electric-shock attacks suggest different questions. They are patterns to investigate rather than diagnoses made from a phrase. Clarify spontaneous pain, precise triggers and any symptom-free interval rather than translating every account into a memorised template.
Ask about associated fever, malaise, altered sensation, bleeding, discharge, jaw restriction and relevant skin, eye or gastrointestinal symptoms. When infection or a serious lesion is possible, specifically ask about breathing, swallowing, voice change, rapidly progressive swelling, persistent neck lumps and weight loss. A negative answer is most useful when the question was actually asked and is recorded accurately.
| Symptom pattern | Useful clarification | Question it raises |
|---|---|---|
| Pain with cold | Does it stop promptly or linger? | Dentine sensitivity versus a pulpal inflammatory pattern |
| Pain on chewing | On pressure, release or sustained muscle use? | Tooth structure, apical tissues or musculoskeletal cause |
| Swelling at meals | Which gland region, how long, and does it settle? | Possible salivary obstruction |
| Recurrent ulceration | Same site or new sites; fully healed between episodes? | Persistent local lesion versus recurrent process |
Medical history: ask what is active now
Record diagnoses, stability, relevant hospital care and the actual effect of disease on activity. A condition’s name alone rarely establishes procedural risk. Ask about cardiovascular and respiratory disease, diabetes, renal or liver impairment, bleeding, immune suppression, cancer treatment and other conditions relevant to the proposed care. Identify recent changes rather than relying only on a previously completed form.
Clarify previous anaesthetic problems, hospital admissions and relevant pregnancy information where appropriate. For cancer treatment, transplant care or complex disease, identify the treating team and timing of treatment. Liaison is useful when it answers a defined question, such as current disease stability or treatment-related blood counts, rather than requesting blanket permission for dentistry.
Reconcile medicines and describe reactions
List medicine names, dose, frequency, route and indication, including non-prescribed analgesics, supplements, herbal products and recreational substances where relevant. Ask what is actually taken, not only what appears on a repeat list. Drug indication can materially change risk assessment, for example osteoporosis treatment versus higher-intensity oncological antiresorptive therapy.
For a reported allergy, record the exact medicine, symptoms, timing, severity, treatment and subsequent exposure. Immediate swelling or breathing difficulty, a severe delayed rash and isolated nausea are different histories. Do not compress them into an uninformative label. Ask about duplicate analgesic ingredients and previous treatment response when planning a new prescription.
Dental, behavioural and social context
Previous dental attendance, treatment experience, trauma, pain, bleeding and reasons for tooth loss help establish disease patterns and expectations. Ask about daily cleaning, fluoride exposure, dietary frequency, tobacco, alcohol and other relevant habits without blame. Explore what the patient can realistically change and whether an apparently ineffective routine reflects technique, access or competing needs.
Anxiety, previous traumatic care, disability, dexterity, transport, finances and home support can alter attendance and maintenance. These are treatment-planning facts, not reasons to stereotype motivation. Where safeguarding concerns arise, follow the relevant process and document factual observations and disclosures rather than unsupported conclusions.
Summarise, verify and make the record useful
Summarise the important chronology back to the patient and invite corrections. Separate what the patient reports, what a carer or record supplies and what remains uncertain. Identify the leading diagnostic questions and the examination needed to resolve them. A structured mnemonic can prevent omissions but should not make the conversation sound like a checklist being read aloud.
Document decisive positives and relevant negatives, medicines and reactions, communication adjustments and the patient’s priorities. Update the history when the medical situation, procedure or symptoms change. In an acute presentation, act on deterioration before completing a lengthy routine history; record what could be obtained and what information remains outstanding.
A distinction to remember
The symptom label “toothache” is not a diagnosis. Record the episode duration, triggers, chronology and patient priorities before narrowing the explanation.
Two patients both say their jaw pain began a week ago. One has two-second attacks triggered by light touch; the other has continuous pain with swelling. Why are these different histories?
Reveal the reasoning
The duration of individual episodes, trigger and associated swelling point towards different mechanisms and urgency. The shared onset date does not make the presentations equivalent. Focus the examination and differential on each pattern instead of treating both as undifferentiated toothache.
Test your recall
Why record the presenting complaint in the patient’s own words?
Show answer
It preserves the concern before clinical interpretation changes it. Their wording can reveal expectations and fears as well as symptoms. Then clarify the account into precise clinical features rather than using the initial phrase as a final diagnosis.