
Extraoral examination
A systematic extraoral examination links the patient’s symptoms to facial, glandular, joint, neurological and cervical findings. Inspect before palpating, compare sides and describe abnormalities so another clinician can reproduce the assessment.
Quick revision summary
Begin with general observation and consent
Observe the patient’s overall appearance, breathing, speech, posture and ability to manage saliva before focusing on a tooth. Distress, stridor, altered consciousness or rapidly increasing swelling changes the priority to acute assessment.
Examine salivary regions with the oral findings
Inspect and palpate the parotid and submandibular regions for asymmetry, tenderness or a discrete mass. Ask about meal-related symptoms and dryness. Intraoral duct examination and appropriate bimanual palpation add information that extraoral inspection cannot provide; document the quality of saliva expressed where assessed.
Integrate, document and determine urgency
Combine the findings with the oral examination and history. A neck lump, unexplained sensory change or progressive trismus can remain important even if a diseased tooth is present. Record normal findings that address the actual differential and avoid documenting an entire system as normal when it was not examined.
Common mistake
A tender tooth does not explain every facial or neck finding. Clicking, tenderness and node size are pieces of evidence, not standalone diagnoses.
Extraoral examination
A systematic extraoral examination links the patient’s symptoms to facial, glandular, joint, neurological and cervical findings. Inspect before palpating, compare sides and describe abnormalities so another clinician can reproduce the assessment.
Begin with general observation and consent
Observe the patient’s overall appearance, breathing, speech, posture and ability to manage saliva before focusing on a tooth. Distress, stridor, altered consciousness or rapidly increasing swelling changes the priority to acute assessment. Where indicated, record observations such as temperature and pulse rather than using the vague description “looks well” as the entire systemic assessment.
Explain the examination and gain consent, arrange comfortable positioning and expose only what is needed. Good lighting and a consistent sequence reduce omissions. Explain palpation before touching a painful region, and adapt for disability, communication needs and tolerance. A routine dental examination does not automatically constitute a complete neurological or ENT examination.
Head and neck lymphatic glands (Gray's Anatomy, plate 602)
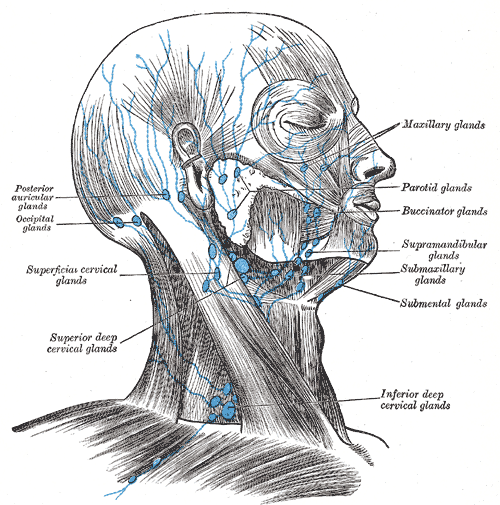
Find the submental and submandibular groups and follow drainage toward the cervical nodes. In this historical figure, ‘glands’ means lymph nodes and ‘submaxillary’ means submandibular. Use current cancer guidance for modern oncological neck levels.
Head and neck lymphatic glands (Gray's Anatomy, plate 602) · Henry Vandyke Carter; reproduced in Henry Gray, Anatomy of the Human Body (1918), plate 602 · Public domain. Unchanged published image; displayed responsively.
Inspect the face, skin and lips
Compare facial symmetry at rest and during expression. Locate swelling relative to the orbit, zygoma, parotid, mandibular border and neck. Note erythema, scars, bruising, sinus openings and skin lesions. Inspect lips and commissures, including the vermilion and visible skin, because a dental complaint can coexist with an unrelated lesion.
For an abnormality, record exact site and side, dimensions, surface change and relation to nearby landmarks. Ask whether it is new or changing and compare reliable prior photographs where available. Photographs can document surface appearance but do not assess deep consistency, fixation, tenderness or the full extent of a mass.
Major salivary glands & ducts
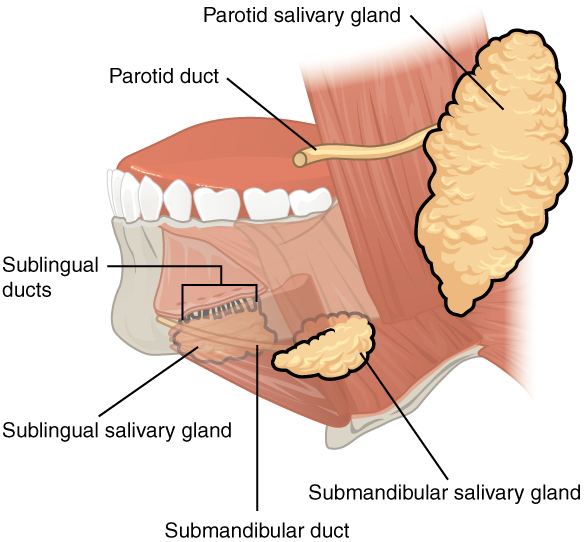
Name each gland and its duct opening. Relate duct obstruction to meal-related swelling and the sublingual gland to a ranula. This overview does not depict every lingual-nerve or facial-nerve relationship.
Major salivary glands & ducts · OpenStax College · CC BY 3.0. Original image; displayed at a responsive size. Original publication.
Palpate swelling and assess cervical nodes
Palpate systematically using finger pads and compare sides. Describe tenderness, temperature, consistency, mobility, fluctuation, attachment to skin or deeper structures and any pulsation. Do not aggressively manipulate an unexplained pulsatile swelling. The examination should establish whether the finding is gland, node, skin or deeper soft tissue rather than calling every lump a lymph node.
Assess submental, submandibular and relevant cervical chains, including supraclavicular regions when indicated. Record the location or neck level, number, approximate size and characteristics of abnormal nodes. A tender mobile node during infection may be reactive, but neither tenderness nor small size alone proves benignity. Persistent unexplained nodes require an appropriate diagnostic pathway.
Major salivary glands
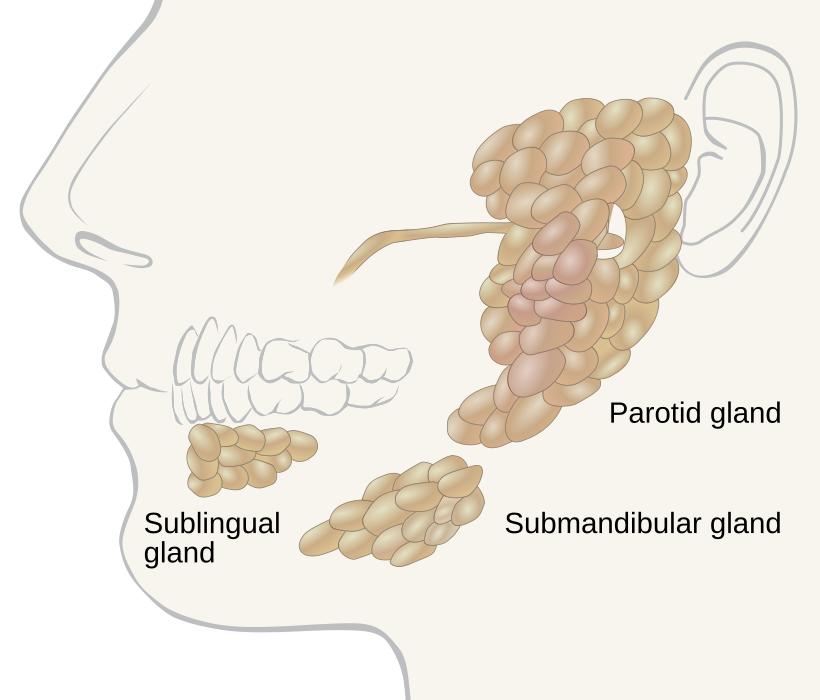
Locate the parotid, submandibular and sublingual glands. Use the gland distribution to relate swelling to the history; the diagram alone does not establish the cause of a mass.
Salivary glands labeled.svg · Goran tek-en, following request by and knowledge from Tom (LT) · CC BY-SA 4.0. None; reproduced without alteration.
Which major gland sits in the anterior floor of the mouth?
The sublingual gland. The submandibular duct also opens into the anterior floor of the mouth, near the lingual frenulum.
Examine salivary regions with the oral findings
Inspect and palpate the parotid and submandibular regions for asymmetry, tenderness or a discrete mass. Ask about meal-related symptoms and dryness. Intraoral duct examination and appropriate bimanual palpation add information that extraoral inspection cannot provide; document the quality of saliva expressed where assessed.
Distinguish diffuse gland enlargement from a focal mass and a neighbouring node. Facial weakness associated with a parotid-region mass, skin fixation or progressive symptoms changes concern. A meal-related history supports considering obstruction but does not establish that every persistent swelling is a stone. Imaging or specialist assessment should answer the specific unresolved question.
Temporomandibular joint anatomy
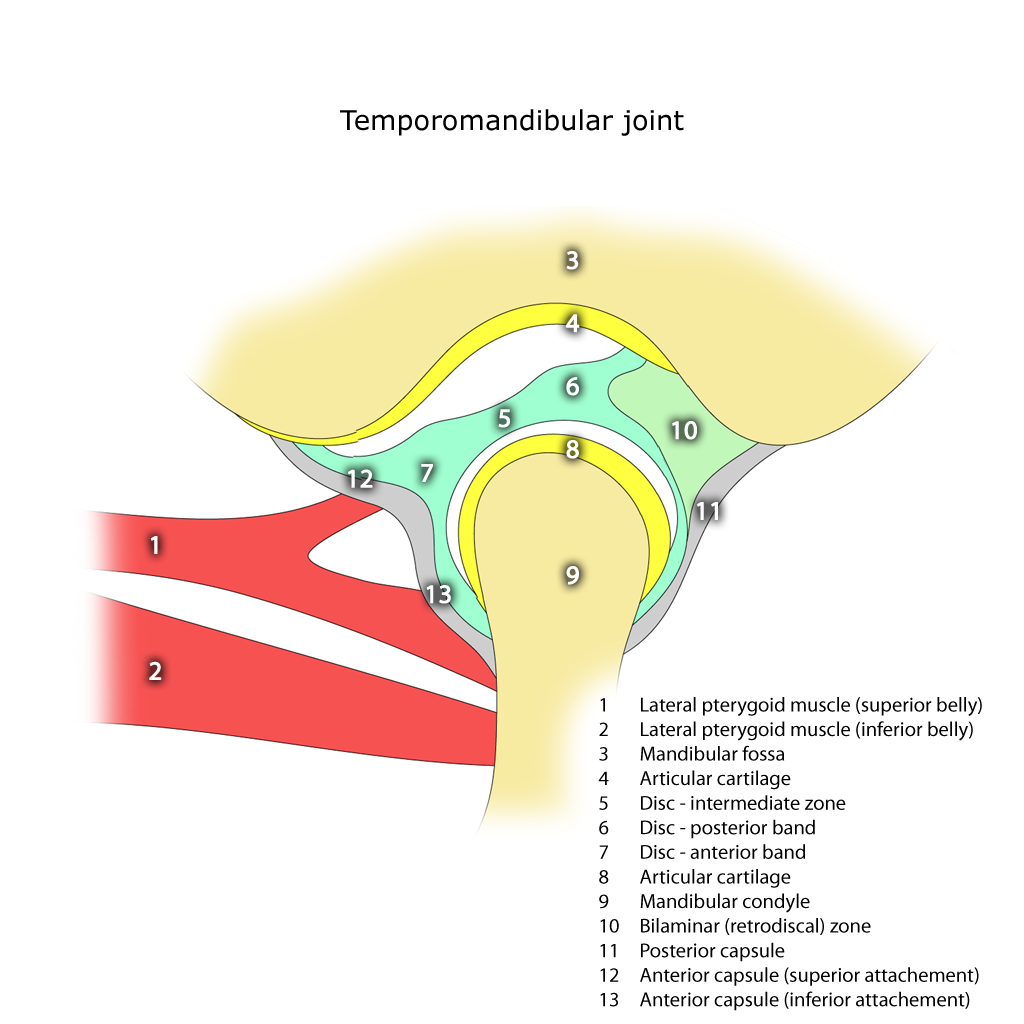
Identify the mandibular condyle, articular disc, articular eminence and mandibular fossa. The disc separates the upper and lower joint compartments.
Temporomandibular joint.png · Frank Gaillard · CC BY-SA 3.0. None; reproduced without alteration.
In which compartment does the main translational movement occur?
The superior compartment. Rotation predominantly occurs in the inferior compartment; normal opening combines both movements.
Jaw movement, TMJ and masticatory muscles
Observe opening, closing, protrusion and lateral excursions as tolerated. Record maximum interincisal opening in millimetres and whether this is painful, assisted or unassisted where assessed; state if overbite is accounted for. Describe deviation, deflection, locking and limitation rather than writing only “TMJ normal”.
Palpate the joints and accessible muscles while asking whether the provoked pain resembles the patient’s familiar pain. Record side, movement-related symptoms and reproducible sounds. Clicking can occur without significant symptoms; it does not by itself establish treatment need. Acute trismus may arise from infection, trauma or other disease, so a muscle explanation needs a matching history and examination.
| Finding | Useful record | Interpretive caution |
|---|---|---|
| Neck lump | Site, size, mobility, consistency, tenderness and duration | Tenderness alone does not classify the cause |
| Restricted opening | Measured opening, pain, movement pattern and time course | Do not automatically label it TMD |
| Joint sound | Side, reproducibility, movement and symptoms | A click alone is not a treatment indication |
| Facial swelling | Anatomical extent, skin findings and deep palpation | Surface size may underestimate deeper spread |
Cervical lymph nodes and anatomical levels
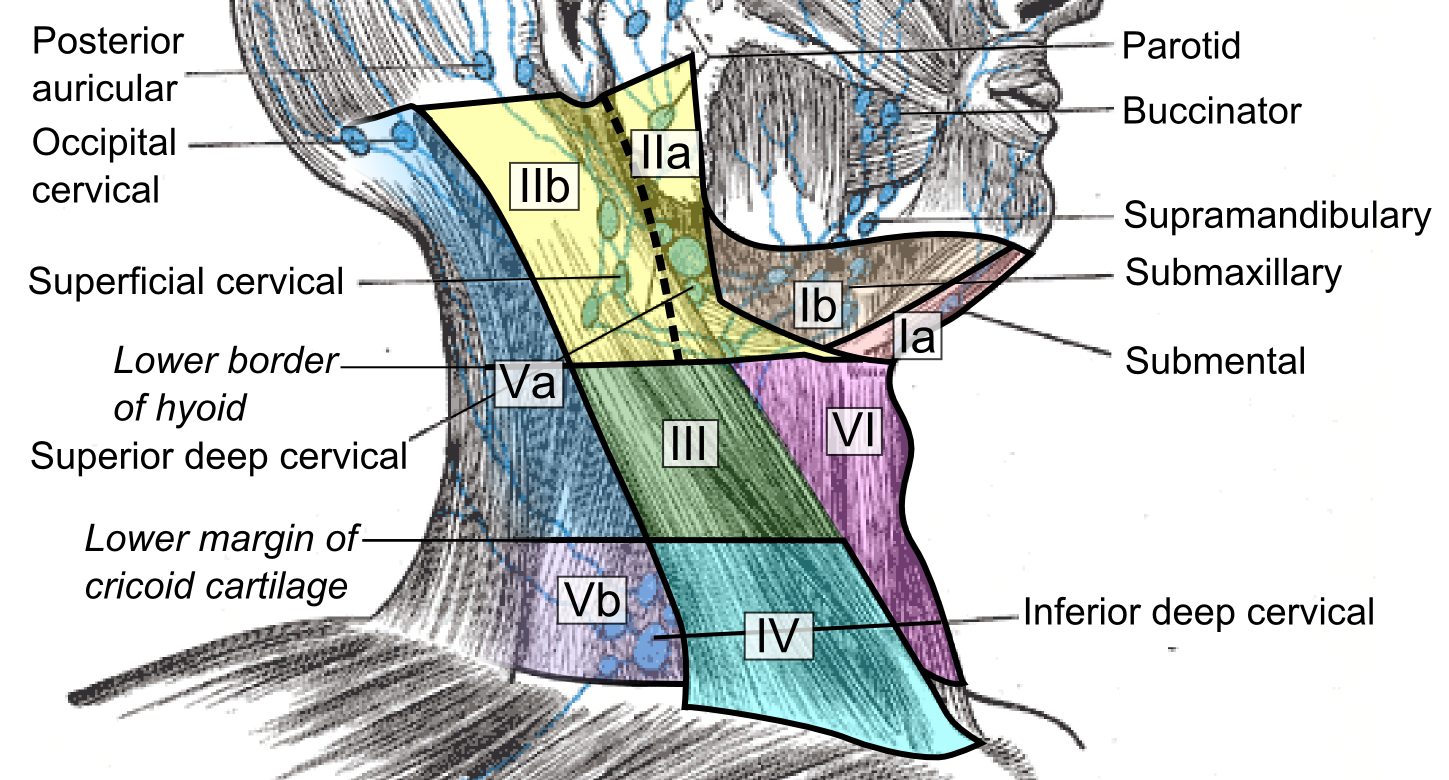
Compare the named node groups with the numbered cervical levels. This schematic does not replace cross-sectional imaging criteria for staging or treatment planning.
Cervical lymph nodes and levels.png · Mikael Häggström, M.D. · CC0. None; reproduced without alteration.
What should you record about a clinically palpable cervical node?
Its exact site and laterality, size, tenderness, consistency and mobility, alongside the relevant oral examination and history.
Perform a focused cranial nerve assessment when indicated
Map light-touch sensation in relevant V1, V2 and V3 territories when numbness, injury or a suspicious lesion warrants it. Compare sides and specify the tested territory. Assess facial expression through movements such as brow raise, eye closure and smile separately from facial sensation. Lower lip weakness is not the same finding as mental nerve numbness.
If relevant, assess tongue movement, palatal movement, voice, shoulder function or eye movements within competence and scope. Document the tests actually performed and their limitations. A new unexplained neurological deficit, especially with several nerves involved, requires broader assessment rather than assuming a peripheral dental cause.
Cranial nerves at the base of the brain
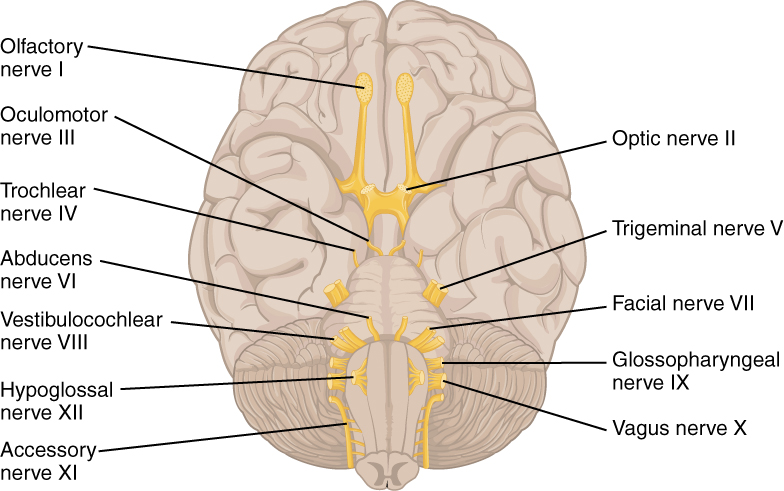
Orientate the inferior brain surface, then locate V, VII, IX, X and XII. Connect them to facial sensation and mastication, facial expression, swallowing and palatal function, and tongue movement. This is a brain-surface overview, rather than a map of the skull foramina.
1320 The Cranial Nerves.jpg · OpenStax · CC BY 4.0. None; original image reproduced without alteration.
Which cranial nerve principally controls tongue movement?
The hypoglossal nerve, XII. Palatoglossus is the exception among the tongue muscles and is supplied through the vagus nerve.
Integrate, document and determine urgency
Combine the findings with the oral examination and history. A neck lump, unexplained sensory change or progressive trismus can remain important even if a diseased tooth is present. Record normal findings that address the actual differential and avoid documenting an entire system as normal when it was not examined.
Breathing difficulty, rapidly progressive infection, eye involvement or major neurological deterioration can require emergency care. A persistent unexplained neck mass or suspicious lip lesion needs the appropriate prompt referral. Where observation is suitable, define the expected change, review timing and action if it persists; a measurement and clear description make that review meaningful.
Submandibular duct stone at the opening
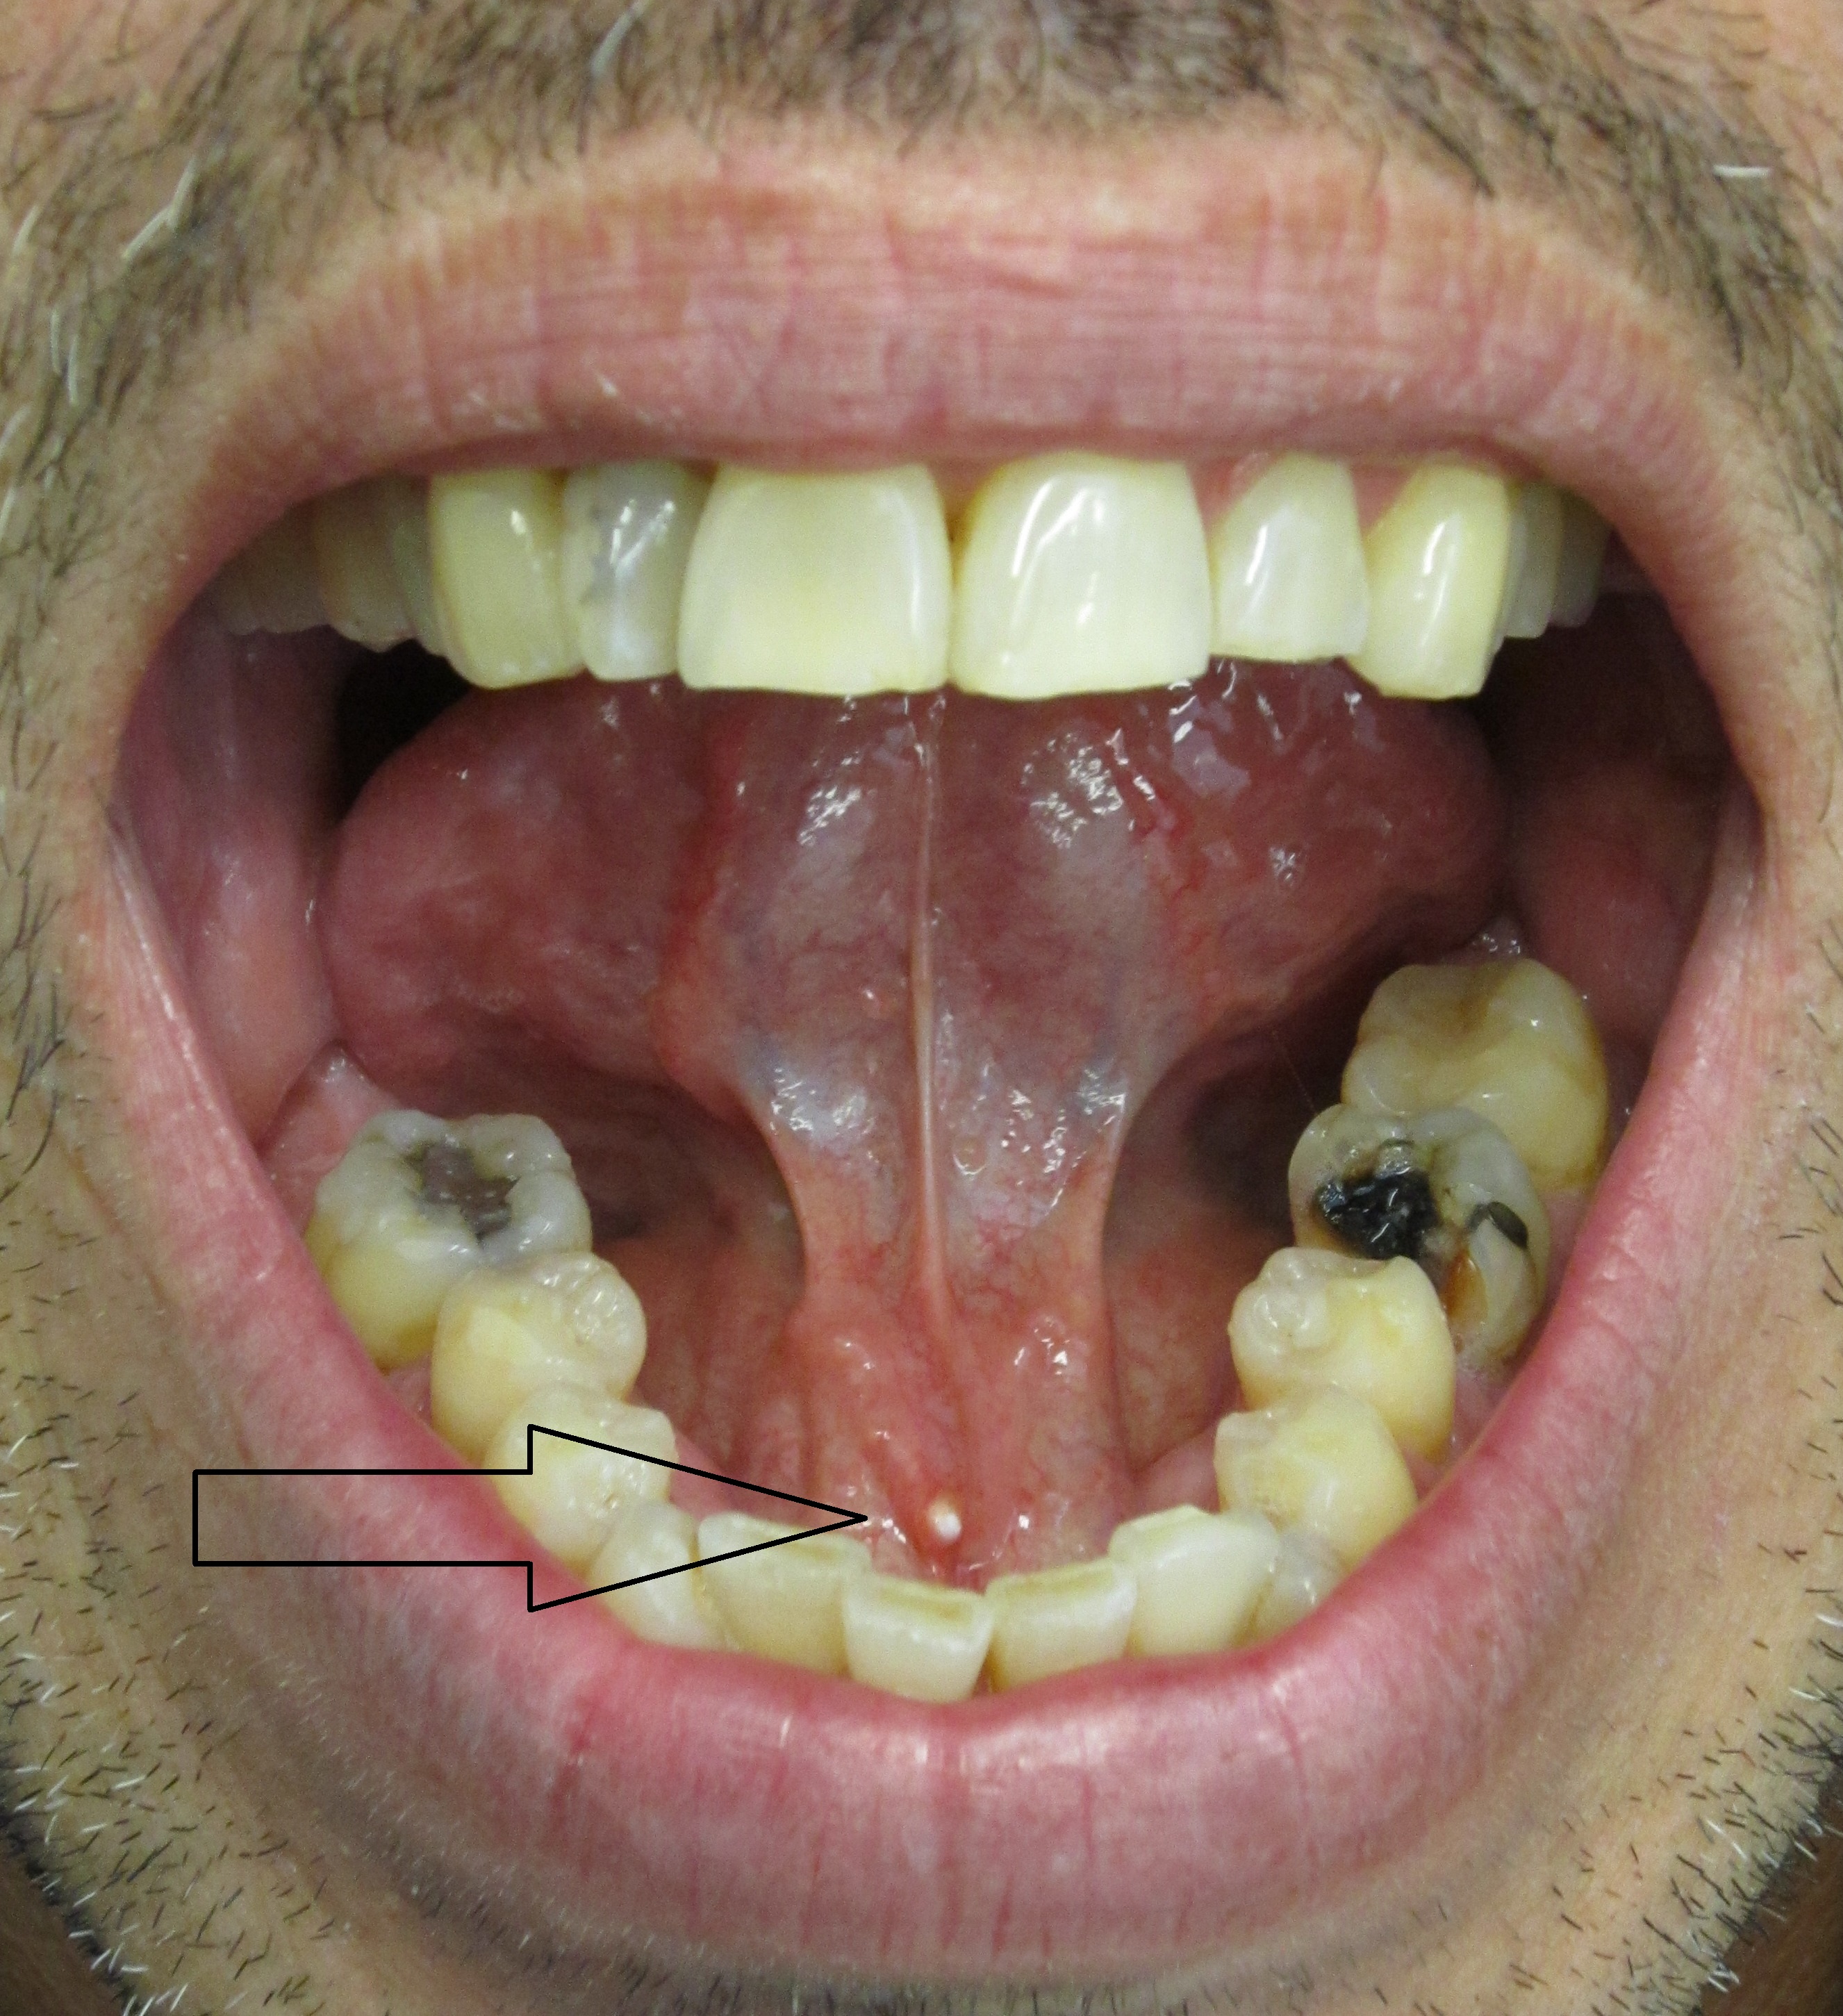
Use the original arrow to locate the pale stone at the submandibular duct opening. Relate the position to the lingual frenulum. Ask about meal-related swelling and assess the gland, duct and saliva. A visible distal calculus does not exclude another obstruction or associated infection elsewhere in the system.
Salivary stone in submandibular salivary duct.jpg · James Heilman, MD · CC BY-SA 3.0. Reproduced without alteration. Labels, arrows and circles, where present, belong to the source image.
Why can gland swelling become more noticeable around meals?
Salivary stimulation increases flow against an obstruction, which can produce swelling and pain. Correlate the timing with examination rather than diagnosing every meal-related swelling as a stone.
A distinction to remember
A tender tooth does not explain every facial or neck finding. Clicking, tenderness and node size are pieces of evidence, not standalone diagnoses.
A patient has a painless firm neck lump for six weeks and also a fractured molar. Can the lump be attributed to the tooth without further assessment?
Reveal the reasoning
No. Establish the lump’s site and characteristics and examine the oral cavity and relevant head-and-neck structures. Persistence and lack of a coherent acute dental explanation require prompt assessment through the appropriate pathway, even if the molar also needs treatment.
Test your recall
Which observations should precede a routine extraoral checklist?
Show answer
Assess general appearance, breathing, speech, alertness and ability to handle saliva. These can identify acute deterioration before detailed examination. A patient with airway compromise needs immediate action rather than completion of a routine sequence.