
Post-extraction complications
Pain, swelling and mild blood-stained saliva can occur during normal healing, but a changing pattern may indicate a complication. Assess timing, severity, progression and physiological stability. Treatment depends on whether the problem is haemorrhage, alveolar osteitis, infection, sinus communication, tissue injury or a non-socket cause.
Quick revision summary
Establish the recovery trajectory
Ask when treatment occurred, what was removed, whether roots were retained and whether the patient initially improved. Review operative difficulty, medicines, smoking and aftercare. Pain should be related to examination findings rather than assumed to originate from the socket.
Assess postoperative infection and deeper spread
Increasing swelling, purulent discharge, cellulitis, lymphadenopathy, fever or systemic symptoms support infection. Examine opening, floor of mouth, neck, swallowing and airway. A retained infected fragment, collection or neighbouring source can require intervention; antibiotics alone may not provide source control.
Provide an explicit review and prevention plan
Give a realistic explanation of the diagnosis, planned local treatment, suitable analgesia and expected response. Check contraindications and duplicate analgesics. Tailor hygiene advice and smoking support, and ensure pressure instructions for recurrent bleeding are practical.
Common mistake
Severe socket pain does not automatically mean infection. Progressive swelling or systemic illness must not be dismissed as dry socket.
Post-extraction complications: diagnose the pattern and act
Pain, swelling and mild blood-stained saliva can occur during normal healing, but a changing pattern may indicate a complication. Assess timing, severity, progression and physiological stability. Treatment depends on whether the problem is haemorrhage, alveolar osteitis, infection, sinus communication, tissue injury or a non-socket cause.
Establish the recovery trajectory
Ask when treatment occurred, what was removed, whether roots were retained and whether the patient initially improved. Review operative difficulty, medicines, smoking and aftercare. Pain should be related to examination findings rather than assumed to originate from the socket. Examine adjacent teeth and relevant soft tissues.
Early swelling and restricted opening may be expected after surgery, but progressive swelling, fever, dysphagia, voice change, floor-of-mouth elevation or breathing difficulty need urgent assessment. A minor original procedure does not make subsequent deterioration benign. Significant bleeding or systemic illness requires physiological assessment before a detailed local differential.
Vascular spasm, platelet plug and blood-clotting cascade
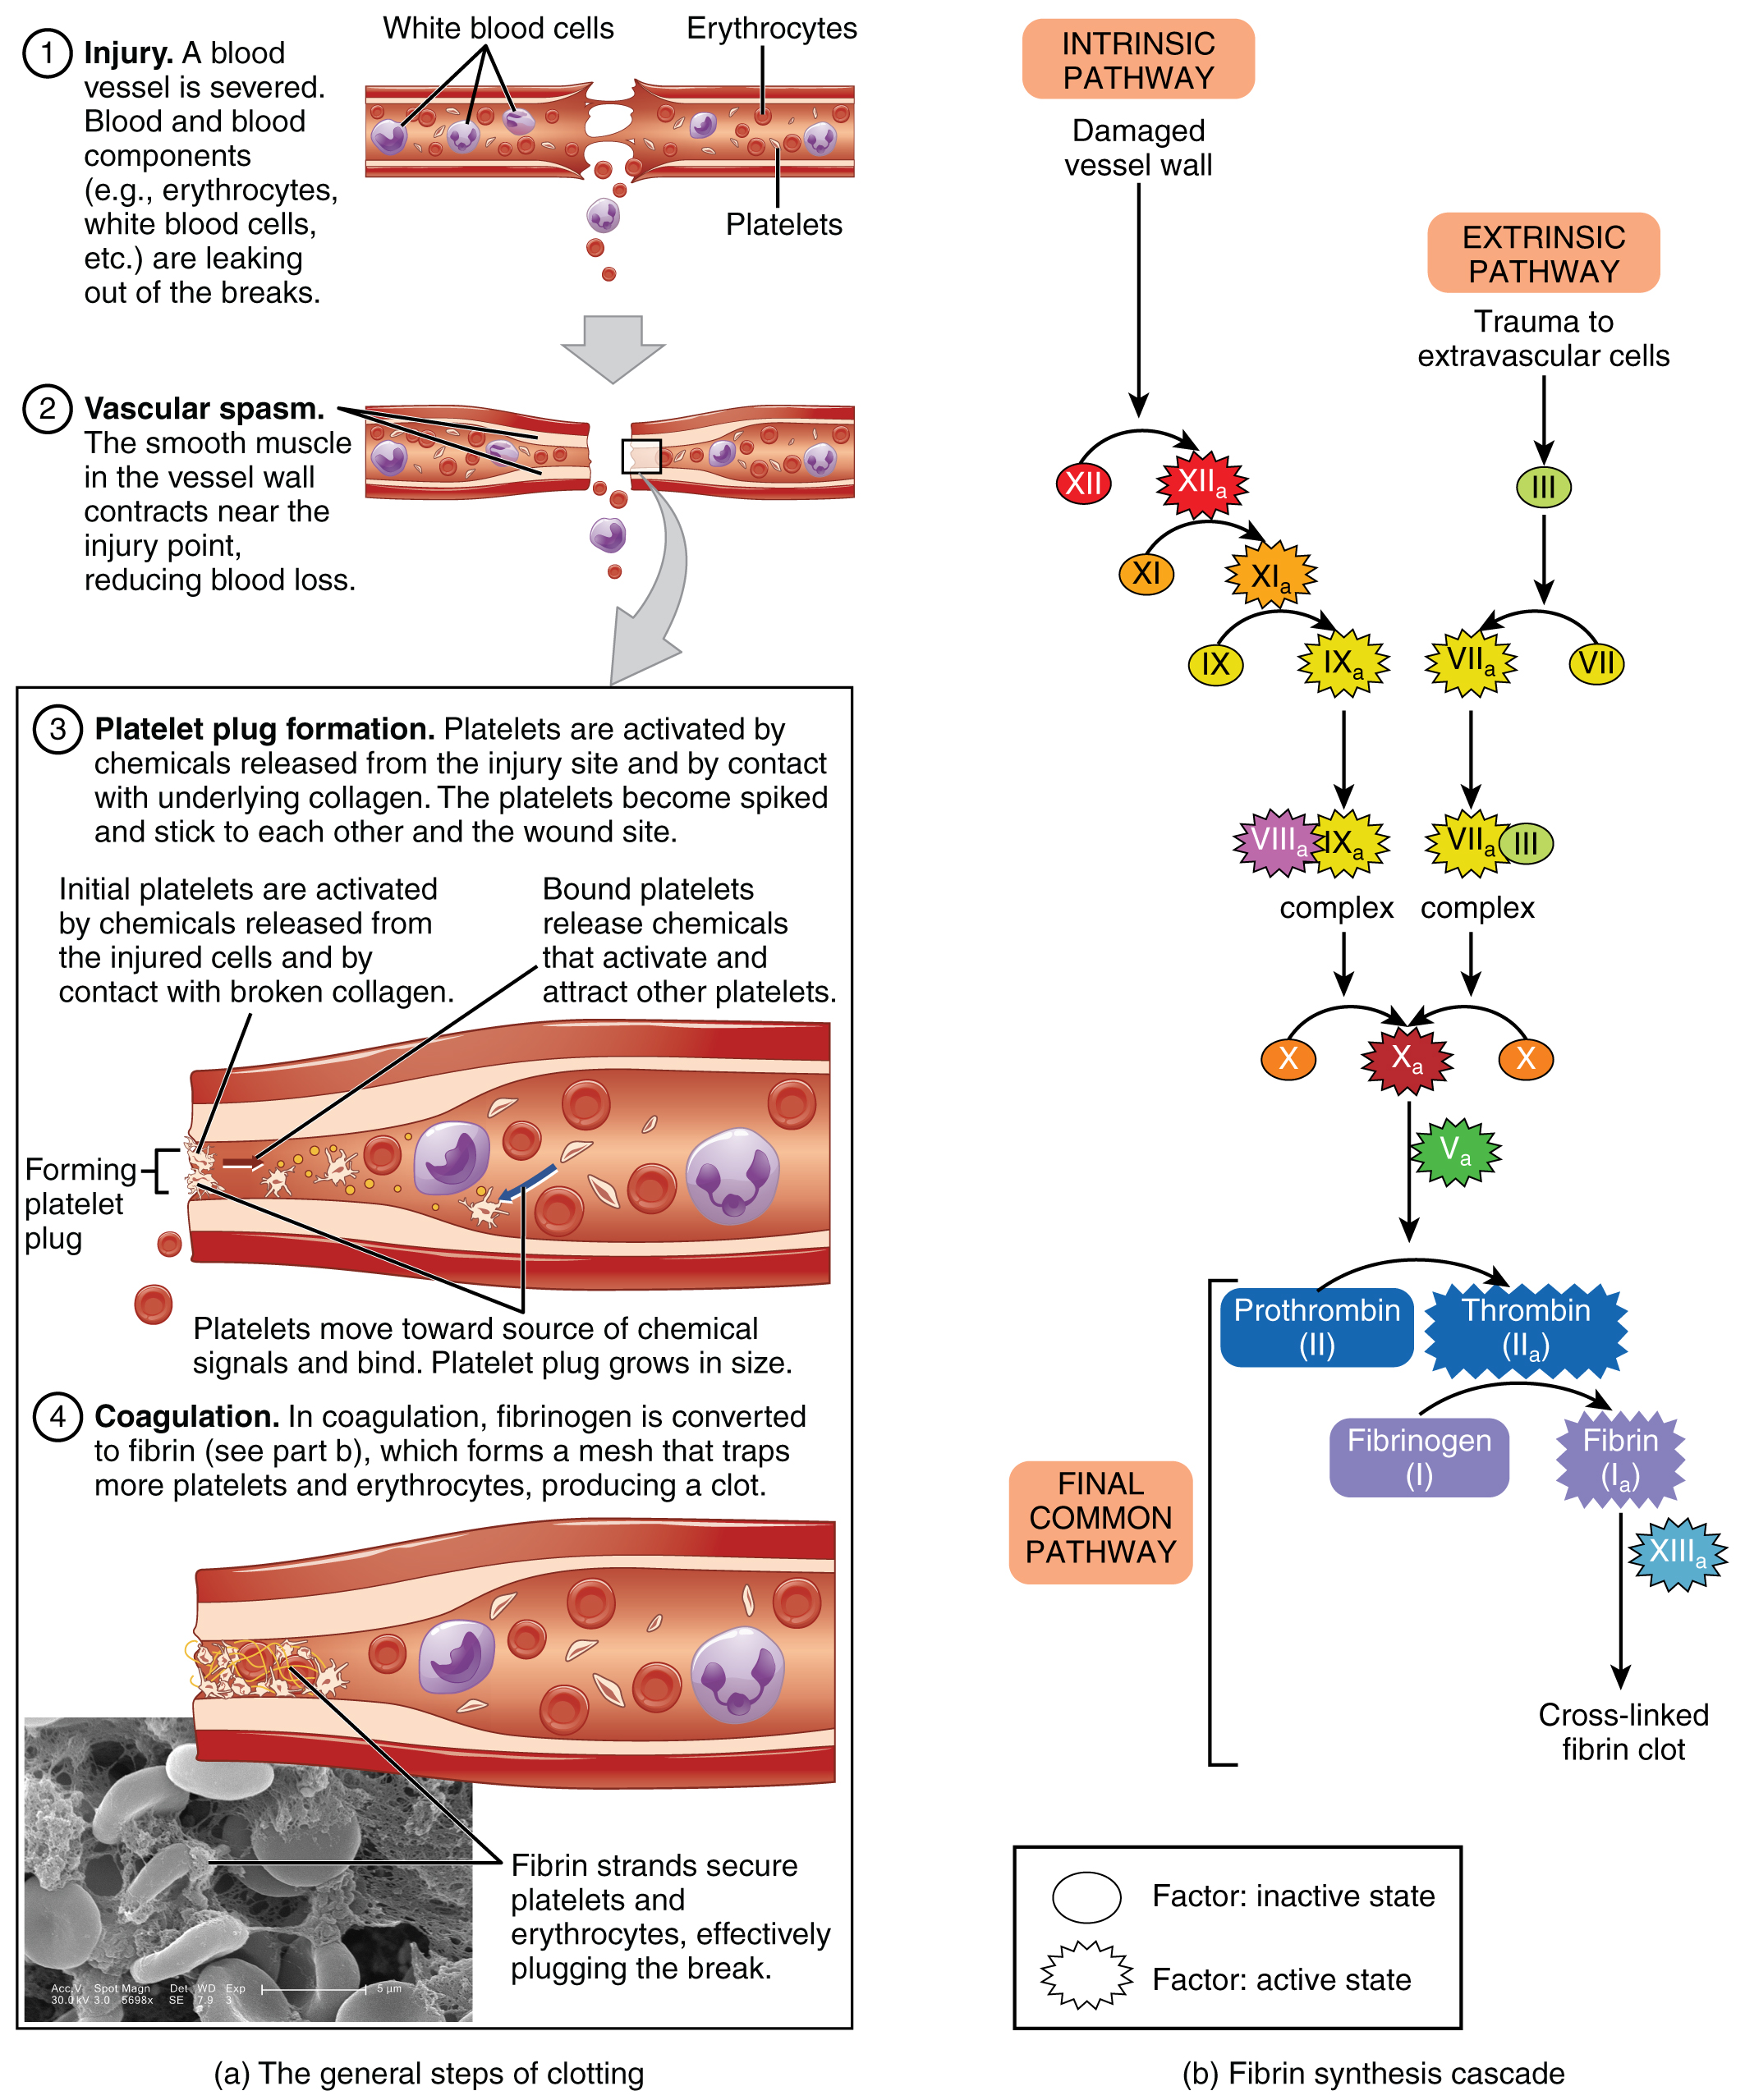
Compare platelet adhesion and plug formation with the development of a fibrin-stabilised clot. Use the labelled intrinsic, extrinsic and common pathways to revise factor deficiencies and laboratory tests. The cascade simplifies the more interconnected process in vivo.
Vascular spasm, platelet plug and blood-clotting cascade · OpenStax College (2013); source micrograph credited to Kevin MacKenzie · CC BY 3.0. Unchanged published image; displayed responsively. Original publication.
Recognise and control haemorrhage
Assess airway contamination, circulation, observations and the history of blood loss, including swallowed blood. Identify whether bleeding is from soft tissue, a socket or another source under suitable lighting and suction. Clot removal, when needed to find the source, should be controlled rather than repeated blind disturbance.
Direct sustained pressure, local haemostatic material and suturing are common measures. Review antithrombotic drugs, coagulopathy and liver or systemic disease if bleeding is disproportionate. Do not independently discontinue medically necessary anticoagulation. Uncontrolled bleeding, instability or failure of adequate local measures requires escalation and appropriate investigation.
Distinguish dry socket from infection
Alveolar osteitis typically presents with significant delayed socket pain after clot breakdown, often with exposed tender bone and an unpleasant taste or odour. Pain may radiate, yet purulence and systemic illness are usually absent. This is not equivalent to a spreading bacterial infection.
Assess the socket gently, exclude another cause and use appropriate local irrigation or dressing and analgesia according to the clinical pathway. Antibiotics are not a routine treatment for dry socket. Repeated curettage or antibiotic escalation can add morbidity without treating the mechanism. Persistent atypical pain should trigger reassessment.
Assess postoperative infection and deeper spread
Increasing swelling, purulent discharge, cellulitis, lymphadenopathy, fever or systemic symptoms support infection. Examine opening, floor of mouth, neck, swallowing and airway. A retained infected fragment, collection or neighbouring source can require intervention; antibiotics alone may not provide source control.
Apply SDCEP principles to decide whether spreading infection, systemic involvement or inability to achieve drainage justifies antibiotics. Reassess response and the diagnosis, using the current review pathway. Deep-space signs, significant trismus or physiological deterioration need emergency care rather than another routine oral prescription.
Identify oroantral and displacement complications
An oroantral communication connects an extraction socket with the maxillary sinus. Passage of fluid to the nose, altered airflow, sinus symptoms and the operative anatomy can raise suspicion. A persistent epithelialised tract is an oroantral fistula. Do not repeatedly probe or force pressure through a suspected communication.
Assessment and management depend on timing, defect characteristics, sinus health and local tissues; not every case requires the same flap. Give sinus precautions and arrange appropriate specialist care. A lost root or fragment requires localisation; blind pursuit can enlarge a communication or displace tissue more deeply.
Consider bone, soft-tissue and nerve problems
Sharp bone edges, a mobile sequestrum, suture irritation and wound dehiscence can produce local discomfort. Persistent exposed bone needs assessment in the context of antiresorptive drugs, radiotherapy, infection and other pathology. A non-healing socket can also be a presentation of malignancy and should not be repeatedly relabelled as infection.
Map new numbness or dysaesthesia and review the mechanism of injury. Pain with electric, burning or stimulus-evoked features may be neuropathic. Persistent pain without supportive dental findings should not lead automatically to further extraction or repeated socket surgery.
Provide an explicit review and prevention plan
Give a realistic explanation of the diagnosis, planned local treatment, suitable analgesia and expected response. Check contraindications and duplicate analgesics. Tailor hygiene advice and smoking support, and ensure pressure instructions for recurrent bleeding are practical. Written advice should identify where and when to seek help.
Record findings, treatment and the safety net, including a route for out-of-hours deterioration. Review a patient who is not following the expected course; reassessment should establish whether the working diagnosis remains adequate. Surface closure alone does not confirm that a deeper complication has resolved.
A distinction to remember
Severe socket pain does not automatically mean infection. Progressive swelling or systemic illness must not be dismissed as dry socket.
Three days after extraction, a patient has severe radiating pain but no swelling, fever or purulence. What is the likely approach?
Reveal the reasoning
Assess for alveolar osteitis and exclude retained material, adjacent tooth disease or another source. Appropriate gentle local care and analgesia are usually central. Antibiotics are not automatic without evidence of infection; persistent or atypical symptoms require a revised assessment.
Guidance to read alongside this chapter
Test your recall
Which features favour alveolar osteitis over spreading infection?
Show answer
Delayed severe socket pain with a disrupted clot or exposed tender bone, often without fever, purulence or progressive cellulitis, supports alveolar osteitis. Examine the patient because alternative or coexisting problems remain possible. Pain intensity alone cannot distinguish the two conditions.