
Fixed bridges
Learn the bridge designs as different ways of transferring load and retaining a replacement tooth. Then compare their biological cost, failure patterns and maintenance needs for a particular space.
Quick revision summary
Choose support and retention deliberately
Distinguish conventional crown retainers, resin-bonded wings and implant support. The condition of adjacent teeth, span, loading, available enamel and maintenance needs determine which options deserve comparison.
Design for forces and cleaning
Pontics, connectors and retainers form one mechanical system. Compare cantilever leverage, differential tooth movement and tissue-contact forms, with adequate material geometry and an accessible route for daily plaque removal.
Investigate the failed interface
One secure retainer can conceal another’s failure. Check biological disease, substrate, fit, resistance and loading before recementing; repeated attachment without addressing the mechanism can reproduce the problem.
Common mistake
Evidence supporting selected single-wing resin-bonded bridges does not mean that a conventional crown-retained cantilever is preferable for every missing tooth.
Fixed bridges
Learn the bridge designs as different ways of transferring load and retaining a replacement tooth. Then compare their biological cost, failure patterns and maintenance needs for a particular space.
Know the vocabulary and the question being answered
The pontic replaces a missing tooth. A retainer attaches the bridge to an abutment tooth or implant. A connector joins the retainer and pontic, or joins adjacent units. A three-unit conventional bridge replacing one tooth often has two retainers and one pontic; unit count is not the same as the number of teeth replaced.
First establish why the space should be restored. Discuss appearance, function, speech and the patient’s priorities, then compare no replacement, a removable prosthesis, resin-bonded or conventional bridgework and implant treatment where feasible. Stabilise caries and periodontal disease. A bridge links the prognosis of its supporting units, so an uncertain abutment can threaten the whole restoration.
Types of bridge: distinguish support from retention
| Design | Arrangement | Main selection issue |
|---|---|---|
| Conventional fixed–fixed | Rigidly connected retainers on teeth at both ends of a pontic span | Needs suitable abutments, a feasible common insertion path and acceptance of tooth preparation. |
| Conventional cantilever | A pontic extends from support on one side | Creates a bending moment; span, load direction and abutment support are critical. |
| Fixed–movable | A non-rigid connector permits specified movement between parts of the bridge | Selected alignment or long-span situations may justify it; connector position and loading require careful planning. |
| Resin-bonded bridge | A bonded retainer, commonly a wing, attaches mainly to suitable enamel | Substrate, isolation, adhesive protocol, available space and loading determine suitability. |
| Implant-supported bridge | A connected restoration is supported by implants rather than prepared natural teeth | Requires restoratively driven implant position, suitable tissues and accessible maintenance. |
Conventional fixed–fixed bridge: when crown preparation is justified
Conventional retainers may be reasonable when adjacent teeth already need suitable indirect restorations and have a sound long-term prognosis. Assess each abutment’s periodontal support, mobility, root morphology, restorability, pulp/endodontic status, clinical crown height and remaining tissue. A large existing restoration is not by itself proof that a tooth is a dependable bridge abutment.
Preparations must provide adequate retention/resistance and material clearance while preserving tissue. The common path of insertion can become difficult when abutments are tilted; aggressive preparation to force alignment adds biological cost. Span length, connector geometry, occlusal space and material properties affect deflection and fracture risk. Historical surface-area rules can prompt assessment but do not substitute for a complete biomechanical and clinical evaluation.
Conventional three-unit fixed-fixed bridge on a cast
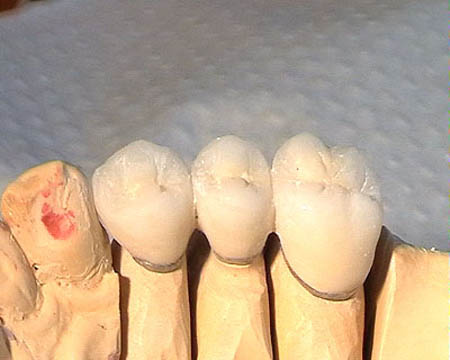
A three-unit posterior bridge on a laboratory cast: two crown retainers flank a central pontic. This small photograph shows tooth support but does not identify the cement or detailed pontic–ridge contact.
Conventional three-unit fixed-fixed bridge on a cast · RosarioVanTulpe · CC BY-SA 3.0. Downloaded current Commons file unchanged.
Conventional cantilever: understand the lever
A load applied to a pontic beyond the supporting abutment produces a moment rather than being shared in the same way as a bounded span. A longer lever arm or an unfavourable contact increases the demand on the retainer and abutment. Evaluate periodontal support, tooth structure, retainer geometry, pontic position, opposing dentition and parafunction together.
The published clinical cantilever photograph is a selected case. It demonstrates the arrangement, not a universal recommendation for canine support or a claim that zirconia prevents lever-related problems. A conventional full-coverage cantilever and a single-wing resin-bonded cantilever have different preparation, bonding and failure mechanisms. Do not transfer the indications of one to the other.
Canine-supported crown-retained zirconia cantilever
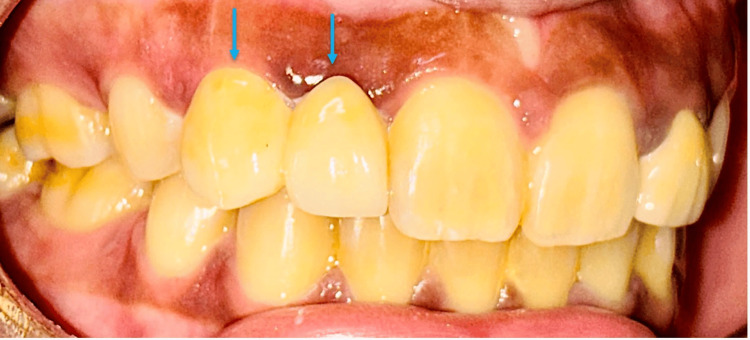
A zirconia cantilever replacing the upper right lateral incisor from a prepared canine crown, shown after cementation. The original blue arrows identify the two connected units. The fitting surface is not visible.
Canine-supported crown-retained zirconia cantilever · Madhurima Sharma, Rohit Nandan, Rohit Sharma, Shalabh Kumar, Akash Gopi, Raina Agarwal, Samra Ashraf, Srijita Mahata and Papan Barman · CC BY 4.0. Original image and blue arrows preserved; no added labels. Original publication.
Resin-bonded bridges: one wing versus two
Assess enamel quantity and quality, the size and location of existing restorations, abutment alignment, space for the retainer, the planned insertion path and the ability to isolate. A wing is not simply glued to any convenient tooth surface. Retainer design, material surface treatment and adhesive selection must form a compatible system. Retainer visibility or greying may matter aesthetically, especially with metal wings.
A single-abutment cantilever resin-bonded bridge can be advantageous in selected single-tooth spaces, particularly anteriorly: it avoids tying teeth with different mobility together. With a two-wing fixed–fixed resin-bonded design, one wing may debond while the other remains attached, allowing an unnoticed plaque-retentive interface. This does not make every two-wing design wrong; selected circumstances may justify it. Diagnose the case and discuss the specific trade-offs.
Use the clinical figures to locate the wing, pontic and direction of extension. The posterior single-wing example illustrates another selected application; it does not show that all posterior spaces can be treated by the same design. Occlusal planning must consider the pontic and wing during closure and excursions, with the design matched to the site and material.
Two-wing Maryland bridge, rear view
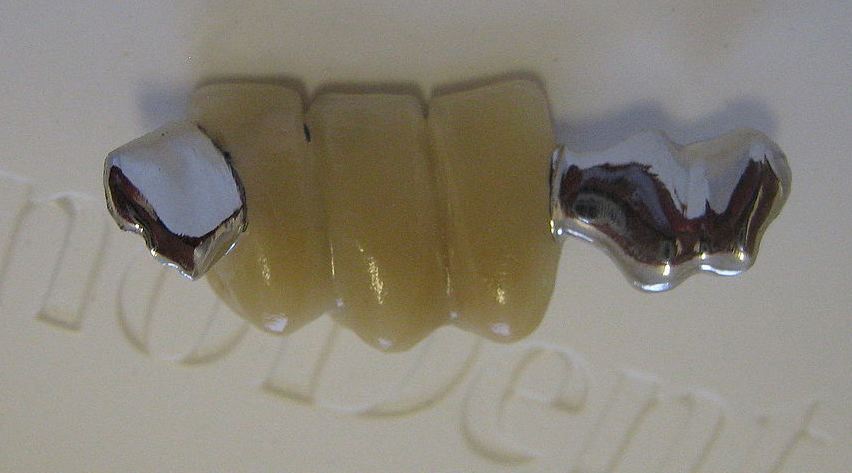
A detached lower anterior Maryland bridge with three pontic units and metal retainers at both ends. This is a multi-pontic, two-wing example; it should not be labelled as the usual single-pontic design.
Two-wing Maryland bridge, rear view · Richard Avery; current crop by Partynia · CC BY-SA 3.0. Downloaded existing Commons crop unchanged.
Anterior resin-bonded bridge with seating hooks
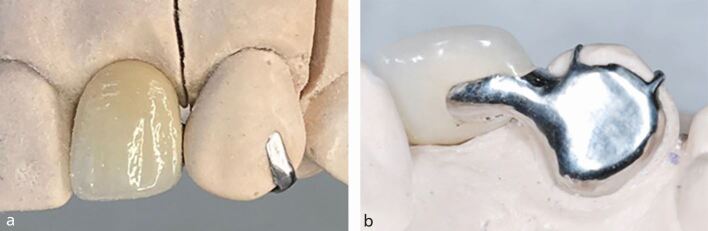
Anterior resin-bonded bridge views demonstrating temporary seating hooks for accurate placement during cementation. Panel b clearly shows one broad metal wing; the number of hooks does not represent the number of retainers.
Anterior resin-bonded bridge with seating hooks · Stephanie King, Banoo Sood and Martin P. Ashley · CC BY 4.0. Original complete labelled figure preserved. Original publication.
Posterior single-wing resin-bonded bridge on a cast
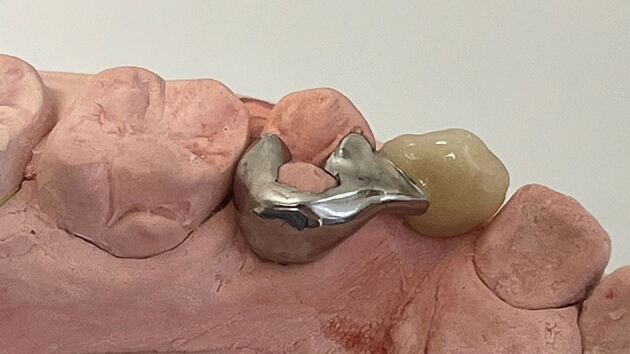
A posterior resin-bonded bridge with one non-perforated wing, proximal wrap-around, rest seats and a substantial connector to the pontic. This cast view illustrates the retainer design; it does not show the clinical bonding interface.
Posterior single-wing resin-bonded bridge on a cast · Stephanie King, Banoo Sood and Martin P. Ashley · CC BY 4.0. Original complete image preserved. Original publication.
Pontic forms: balance appearance, tissue contact and access
Pontic tissue contact should be intentional and the surface smooth and accessible. Avoid pressure-induced blanching as an accepted endpoint. Ridge deficiency may require a compromise, tissue management or a different replacement option; adding bulk to hide every defect can obstruct hygiene.
| Form | Typical contact relationship | Practical implication |
|---|---|---|
| Modified ridge lap | Contact is concentrated towards the facial crest with a cleansable, convex tissue surface | Often balances appearance and hygiene; avoid a concave underside that traps plaque. |
| Ovate | A rounded pontic extends into a suitably shaped soft-tissue site | Can create an emergence appearance but requires planned tissue form, access and maintenance. |
| Hygienic / sanitary | No ridge contact, with sufficient clearance underneath | May suit selected non-aesthetic posterior locations; verify functional and cleaning space. |
| Conical | A small rounded contact area | Selected ridge forms may permit cleansing, but shape and location can create food traps. |
| Full ridge lap / saddle | Broad facial and palatal/lingual contact around the ridge | A concave tissue surface is difficult to clean and is generally an unfavourable definitive design. |
Connectors, materials and the failure mechanism
| Feature | Why it matters | What to verify |
|---|---|---|
| Rigid connector dimensions and contour | Cross-section and geometry affect stiffness and stress concentration | Use material- and system-specific requirements; allow access for cleaning. |
| Non-rigid connector | Allows a defined relationship between components | Its indication, position and direction must fit the entire bridge plan. |
| Metal–ceramic | Combines a metal framework with veneering ceramic | Framework support, ceramic clearance, appearance and possible veneer damage. |
| Zirconia or other ceramic systems | Properties differ by material formulation and restoration design | Do not apply one connector size or bonding protocol to every ceramic. |
| Bonding substrate / surface treatment | Retention depends on both tooth and restoration surfaces | Follow the compatible material protocol and maintain isolation. |
Implant bridges: support position is part of the restoration
Plan the desired teeth and cleansable contours before deciding implant positions. Implant support can avoid preparation of adjacent teeth, but adds surgery, tissue and maintenance considerations. The number and distribution of implants, span and any cantilever affect loading. The supplied three-implant framework photograph shows its support arrangement; it does not establish an implant-number formula for other cases.
Screw access, retrievability, passive fit, restorative space and emergence contour matter. Distinguish a loose component from a mobile implant. Explain possible screw loosening, fracture, chipping, peri-implant inflammation and the need for long-term maintenance. Teeth and implants differ in mobility and support; connecting them requires a specific rationale and is not an interchangeable routine design.
Implant-supported bridge on three implants, laboratory view
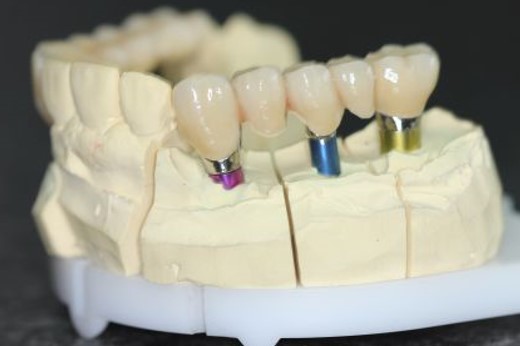
Laboratory view of an implant-supported bridge on three implant components. The coloured components make the support points visible; this is a cast, so the image does not show implants within bone.
Implant-supported bridge on three implants, laboratory view · Drmscmuc · CC BY-SA 4.0. Original complete image preserved.
Worked selection: the same space can have different answers
| Clinical situation | Reasoned options | Decisive questions |
|---|---|---|
| Missing upper lateral incisor; neighbouring teeth largely intact | Consider an enamel-bonded bridge, implant assessment or another patient-preferred option | Is enamel suitable, can loading be controlled, is growth complete for implant consideration, and what does the patient value? |
| Missing posterior tooth; adjacent teeth already need crowns | Conventional bridgework may form part of the restorative plan | Are both teeth sound abutments and is the span/material/occlusion feasible? |
| Space beside a heavily restored tooth with uncertain endodontic prognosis | Avoid treating bridge preparation as a way to bypass the uncertain diagnosis | Can the tooth be retained predictably, and how would its failure affect the proposed prosthesis? |
| Long span with poor support or limited hygiene access | Compare removable rehabilitation, implant options, specialist assessment or accepting the space | Can the proposed fixed design be maintained and can its load pathway be defended? |
Clinical stages and verification
Complete diagnosis, disease control and an agreed design before preparation or bonding. Use diagnostic records or a trial arrangement where they help verify appearance, space and function. Communicate the retainers, pontic contour, material, connector requirements, shade, tissue relationship and occlusal objectives to the laboratory. Provisionals for conventional work should protect teeth and preserve useful relationships while allowing tissue health.
At try-in, assess seating, margins, contacts, passive fit where relevant, pontic access, appearance and the planned occlusion before definitive cementation or bonding. For resin-bonded work, rehearse seating and isolation and follow the selected surface-treatment system. Check for residual cement or adhesive and confirm the patient can clean underneath the pontic with a suitable aid.
When a bridge fails: identify what failed
Loss of retention, caries, periodontal deterioration, pulp disease, framework fracture and veneer chipping are different diagnoses. Assess the entire bridge and all abutments before proposing recementation or rebonding. A debonded resin-bonded bridge may be repairable, but first ask why the bond failed and whether the remaining substrate and restoration are suitable.
If a conventional retainer loosens while another remains attached, disease can develop beneath the unsealed retainer. New sensitivity, a bad taste, altered contacts or movement deserves assessment. Repeated rebonding without revisiting substrate, design or occlusion may postpone the same failure. A maintenance plan should make cleaning, review and the route for a problem explicit.
A distinction to remember
Evidence supporting selected single-wing resin-bonded bridges does not mean that a conventional crown-retained cantilever is preferable for every missing tooth.
One wing of a two-wing resin-bonded bridge debonds but the bridge feels secure. Why does that matter?
Reveal the reasoning
The remaining wing can conceal failure at the other interface. Plaque and caries may develop beneath the unsealed retainer. Assess both bonds, the substrate and the failure mechanism rather than assuming the secure pontic proves the whole bridge is intact.
Test your recall
What are the components of a three-unit fixed–fixed bridge replacing one tooth?
Show answer
Two retainers attach to the abutment teeth, a pontic replaces the missing tooth and connectors join the units. Three units do not mean three missing teeth. Assess each component as part of the support, loading and maintenance system.