
Oral cancer awareness
Oral cancer awareness means recognising a concerning pattern and acting on it. A painless lesion, young age or an absent tobacco history should not prevent appropriate assessment.
Quick revision summary
Risk informs vigilance, not exclusion
Tobacco, smokeless tobacco, areca products and alcohol are important oral-cancer exposures, with combined tobacco and alcohol use increasing risk. Ask about current and previous use, duration and the products involved.
Recognise a pattern requiring urgent action
Unexplained oral ulceration persisting for more than three weeks is a NICE suspected-cancer referral consideration. A dentist should also consider the pathway for a suspicious oral or lip lump or a red or red-white patch consistent with erythroplakia or erythroleukoplakia.
Use short review only when it answers a question
A clinically plausible traumatic lesion without suspicious features may be reviewed after removing the cause, provided the plan includes a definite date and an action if it persists. Do not reset the observation clock each time a new irritant is suggested.
Common mistake
A risk-factor history cannot rule out cancer, and a suspected traumatic cause must not justify repeated observation of a persistent or suspicious lesion.
Oral cancer awareness
Oral cancer awareness means recognising a concerning pattern and acting on it. A painless lesion, young age or an absent tobacco history should not prevent appropriate assessment.
Risk informs vigilance, not exclusion
Tobacco, smokeless tobacco, areca products and alcohol are important oral-cancer exposures, with combined tobacco and alcohol use increasing risk. Ask about current and previous use, duration and the products involved. Human papillomavirus has an important association with some oropharyngeal cancers, but this should not be used to explain every lesion in the oral cavity or replace examination.
Patients without recognised risk factors can still develop malignancy. A clinician should respond to the appearance and behaviour of a lesion rather than offer reassurance based only on age or lifestyle. Lip ultraviolet exposure, previous cancer and treatment history may also matter. Preventive discussion should accompany assessment and must not delay a referral while a patient attempts behaviour change.
Cervical lymph nodes and anatomical levels
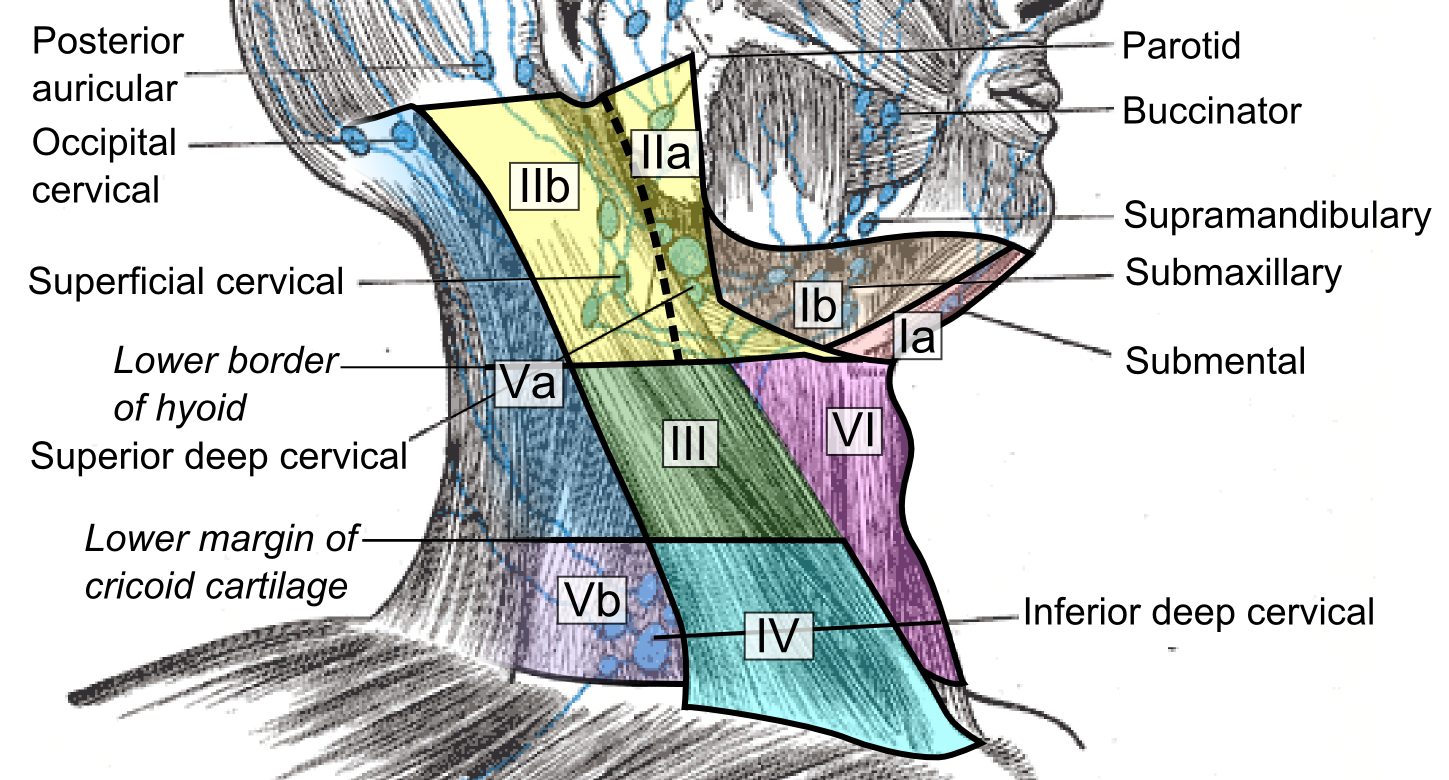
Compare the named node groups with the numbered cervical levels. This schematic does not replace cross-sectional imaging criteria for staging or treatment planning.
Cervical lymph nodes and levels.png · Mikael Häggström, M.D. · CC0. None; reproduced without alteration.
What should you record about a clinically palpable cervical node?
Its exact site and laterality, size, tenderness, consistency and mobility, alongside the relevant oral examination and history.
Take a focused lesion history
Establish onset, persistence, change in size or texture, bleeding, pain, trauma and previous episodes. Ask about swallowing difficulty, persistent throat symptoms, altered speech, unexplained numbness, weight change and neck lumps as relevant. A patient may call a lump an ulcer or describe intermittent symptoms imprecisely, so clarify what has actually persisted and examine the identified site.
Review dentures, sharp teeth, recent treatment, medicines and systemic illness without allowing a plausible benign cause to end the assessment prematurely. Document the response to previous treatment and whether the lesion ever fully resolved. Repeated empirical courses that never resolve an unexplained lesion can create delay and obscure its evolution.
Examine and describe the finding
Perform a systematic extraoral and intraoral visual and tactile examination, including lips, tongue borders and ventral surface, floor of mouth and relevant neck nodes. Use adequate light, remove dentures and manipulate tissues sufficiently to see concealed surfaces. Palpation can identify induration, fixation or a deeper component that a photograph alone misses.
Record exact site and laterality, dimensions, colour, surface, border, number, tenderness and consistency. Describe an ulcer’s base and surrounding tissue rather than writing only mouth ulcer. A dated photograph with consent and an orientation record helps follow change and support a referral. Compare regional nodes and neurological or functional findings when the presentation makes these relevant.
Recognise a pattern requiring urgent action
Unexplained oral ulceration persisting for more than three weeks is a NICE suspected-cancer referral consideration. A dentist should also consider the pathway for a suspicious oral or lip lump or a red or red-white patch consistent with erythroplakia or erythroleukoplakia. Persistent unexplained neck lumps need appropriate assessment. Strong suspicion is a reason to act promptly before a duration threshold has elapsed.
An unexplained indurated ulcer, fixation, progressive numbness or suspicious nodes changes the urgency even if the patient thinks they bit the site. Not all white lesions are cancer, and not all cancers are ulcerated. Form a differential that explains the observed features while prioritising conditions where delay could cause harm.
| Finding | Why it matters | Action principle |
|---|---|---|
| Unexplained ulcer beyond 3 weeks | Persistence meets a referral consideration | Use suspected-cancer assessment pathway |
| Suspicious induration or fixation | Concern may exist before 3 weeks | Do not wait for a time threshold |
| Red or red-white patch | Potentially malignant appearance | Assess and refer appropriately |
| Persistent unexplained neck lump | May have no obvious oral primary | Appropriate head and neck assessment |
Refer with information that supports triage
Use the local urgent suspected-cancer route when indicated and explain the reason in clear, calm language. Include duration, evolution, exact site, dimensions, description, relevant risks and examination findings, with a photograph where suitable. State the suspected diagnosis or concern rather than expecting the recipient to infer urgency from a vague request for advice.
A specialist team generally plans biopsy of a suspicious lesion, selecting viable representative tissue and the appropriate procedure. Histology is the diagnostic standard; a light-based adjunct or staining device does not provide an equivalent exclusion test. Do not carry out an unplanned excision that could compromise definitive assessment merely because the lesion appears small.
Use short review only when it answers a question
A clinically plausible traumatic lesion without suspicious features may be reviewed after removing the cause, provided the plan includes a definite date and an action if it persists. Do not reset the observation clock each time a new irritant is suggested. If the history already meets a referral criterion or the findings are concerning, observation should not postpone the appropriate pathway.
Confirm the patient knows who will arrange the referral, how results will be communicated and whom to contact for deterioration. Track outstanding appointments and histology through the local process. Oral-cancer prevention also includes supporting tobacco cessation, lower-risk alcohol choices and continuing oral care after treatment, particularly where dry mouth, restricted opening or radiotherapy changes raise dental risk.
A distinction to remember
A risk-factor history cannot rule out cancer, and a suspected traumatic cause must not justify repeated observation of a persistent or suspicious lesion.
A non-smoker has a painless indurated lateral-tongue ulcer for two weeks. Should referral wait another week?
Reveal the reasoning
No. The induration and site create clinical concern, so use the appropriate urgent pathway promptly rather than waiting to satisfy a duration threshold. Document the lesion and associated findings, explain the concern calmly and track the referral.
Test your recall
Which lesion details make a referral useful?
Show answer
Record exact site and laterality, dimensions, duration, evolution, colour, surface, border and consistency, with relevant nodes and functional findings. Include the clinical concern and a suitable photograph where available. A note saying only oral lesion gives little basis for triage.