
Non-surgical therapy
Non-surgical care combines daily biofilm control, risk management and targeted professional instrumentation. Judge it by a measurable tissue response and a workable maintenance plan, rather than the duration of scaling or the smoothness of every root.
Quick revision summary
Combine patient and professional care
Daily plaque control and risk management support targeted instrumentation. The first step includes useful professional treatment as well as advice; subsequent care follows the diagnosis and response.
Preserve the root surface
Use appropriate instruments and adaptation for concavities and furcations. Remove biofilm and calculus without unnecessarily sacrificing cementum. A smooth accessible surface does not prove that every difficult site has been treated.
Measure the response
Compare site-level inflammation, pocketing and cleaning after healing. Persistent sites need an explanation and a focused plan, while successful control leads to continuing risk-based supportive care.
Common mistake
Persistent pocketing needs reassessment of its cause before repeated instrumentation, surgery or antibiotic prescribing.
Non-surgical therapy
Non-surgical care combines daily biofilm control, risk management and targeted professional instrumentation. Judge it by a measurable tissue response and a workable maintenance plan, rather than the duration of scaling or the smoothness of every root.
Diagnose and agree the aim
Record baseline pockets, bleeding, plaque, attachment information and indicated images. Establish which teeth are restorable and maintainable and whether an acute infection, fracture or endodontic problem requires a different intervention. A diagnosis should precede a prescribed number of scaling sessions.
Discuss outcomes the patient values, such as less bleeding, retained function and easier cleaning, alongside prevention of further support loss. Explain that recession, root sensitivity and open interdental spaces may become more apparent as swelling resolves. These changes should be part of consent rather than unexpected effects reported only after treatment.
Periodontitis: pocket formation and loss of support
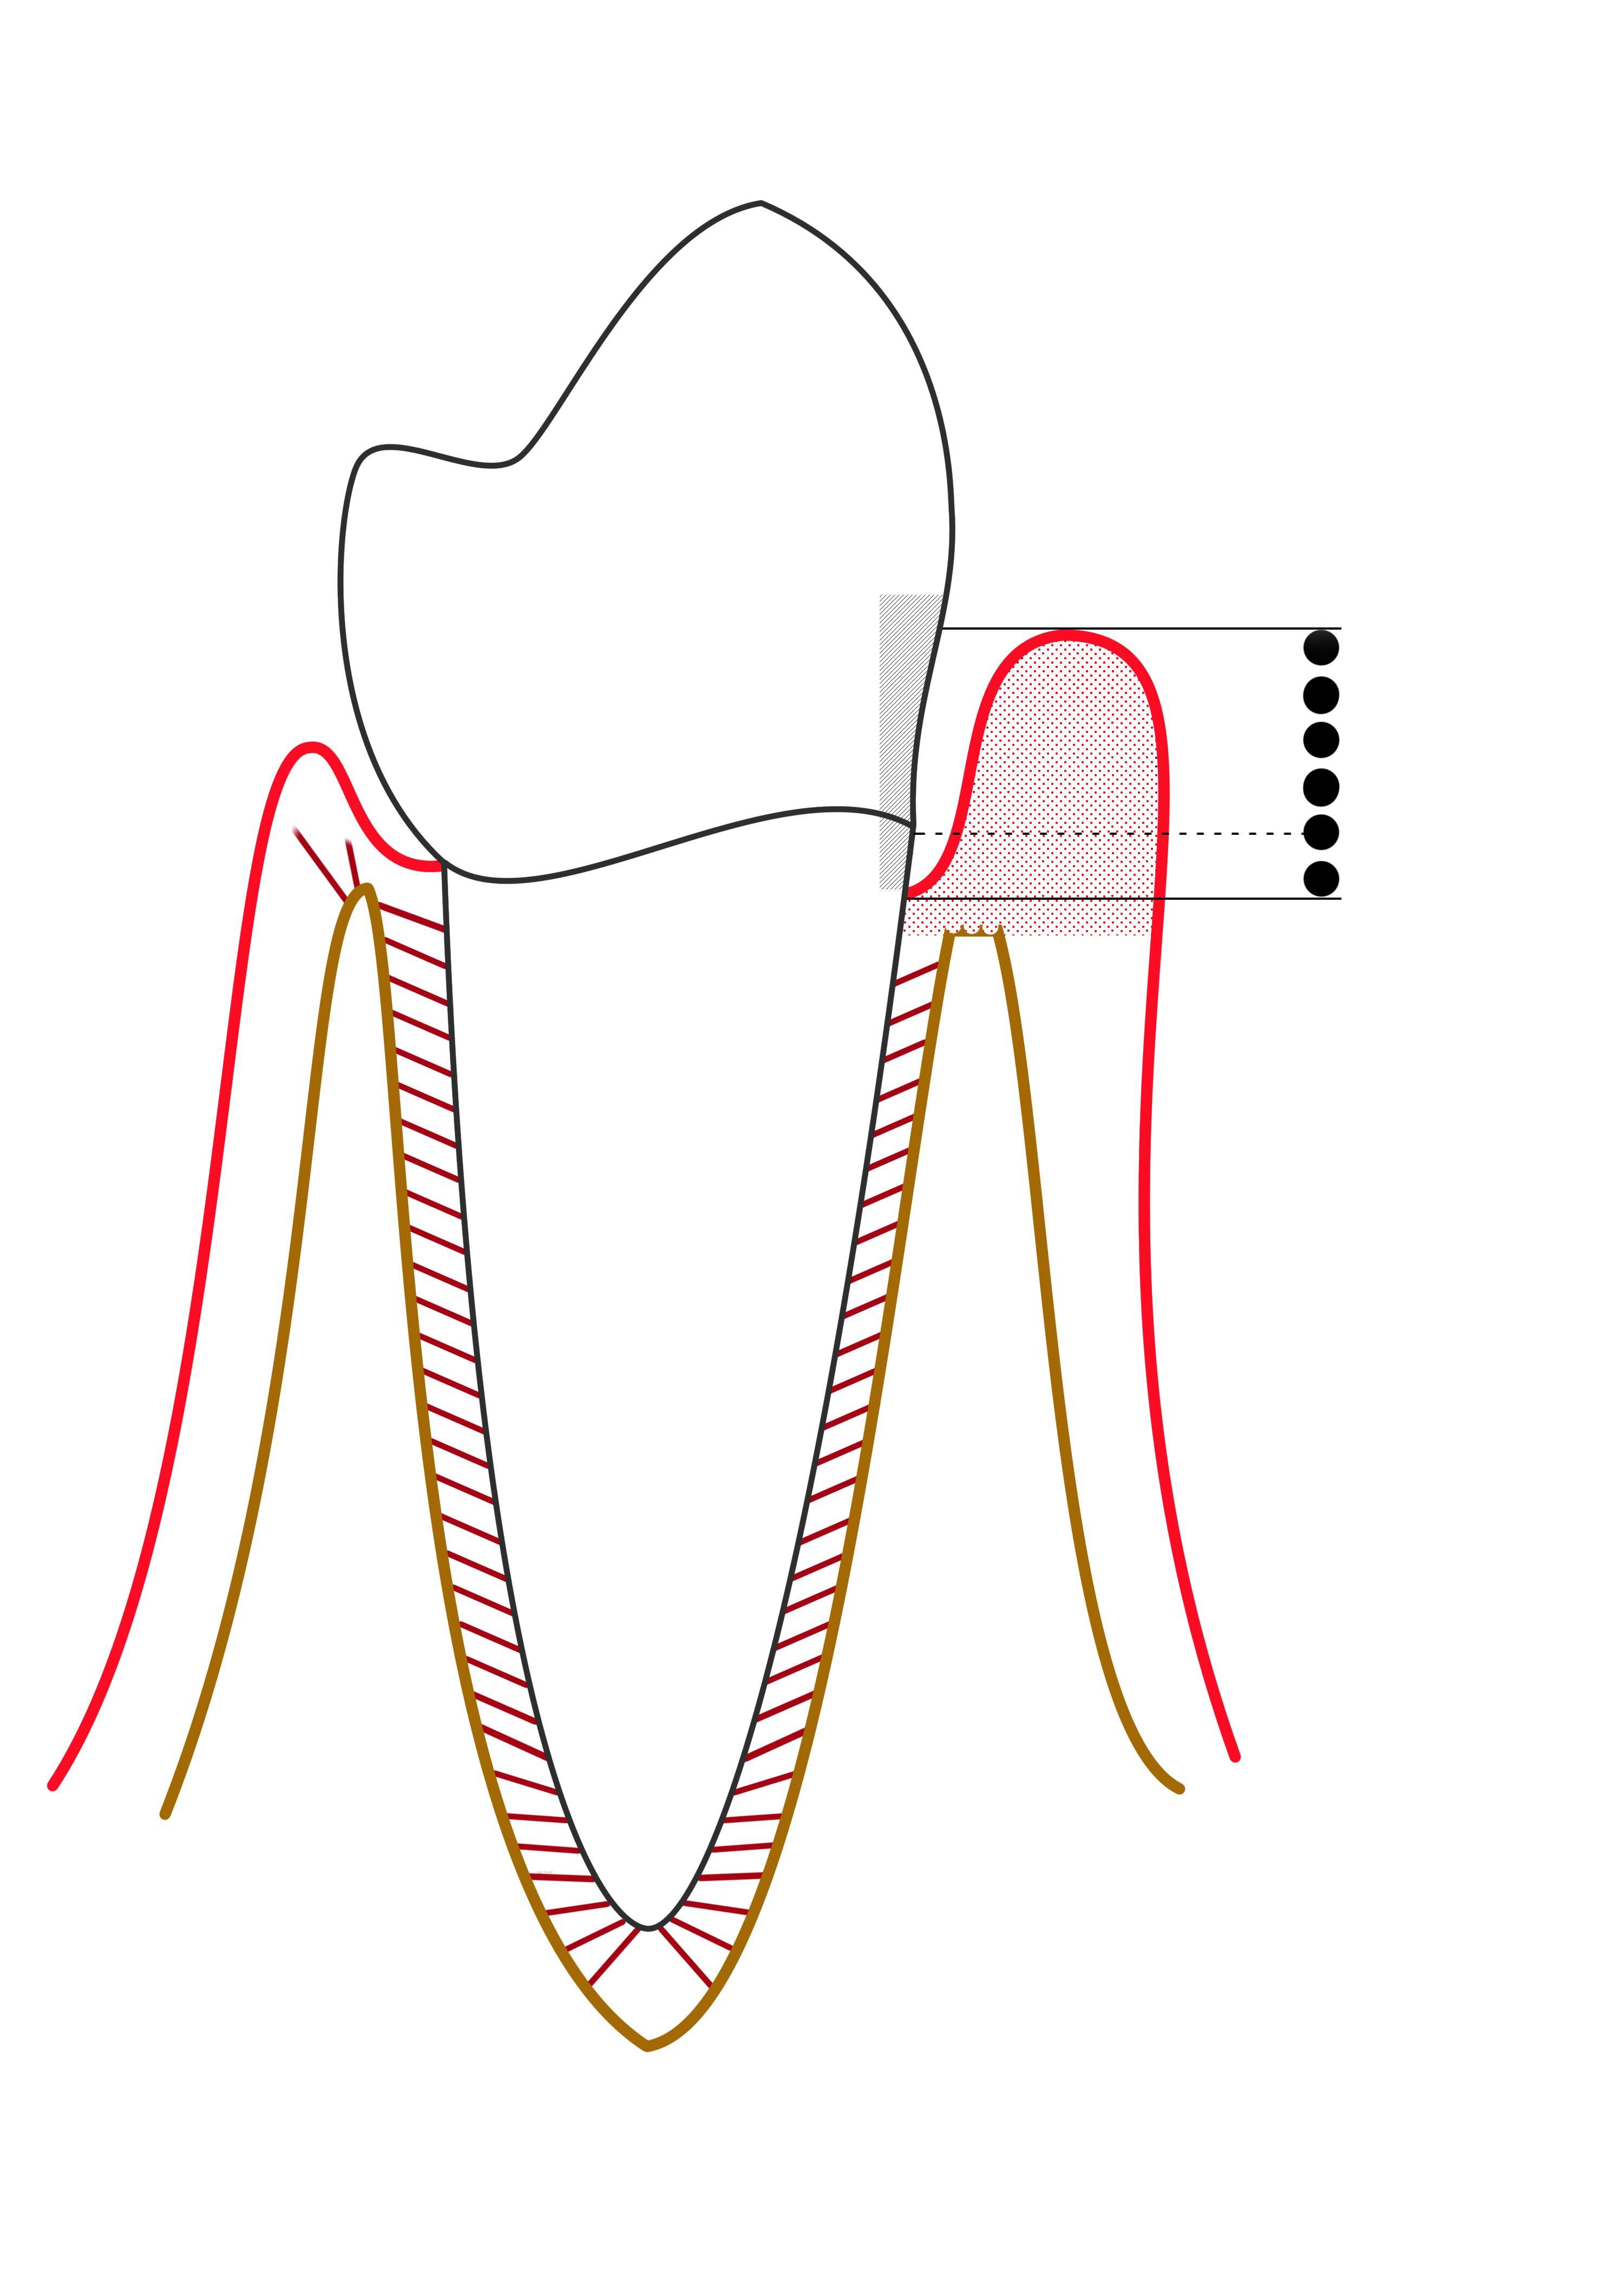
Compare the apical extent of the pocket and the reduced supporting bone on the affected side. This simplified diagram is labelled “mild periodontitis” by its author; it is not a modern stage/grade classification chart.
Mild periodontitis.png · Ian Furst · CC BY-SA 4.0. None; reproduced without alteration.
Why is probing depth different from clinical attachment level?
Probing depth runs from the gingival margin to the pocket base. Clinical attachment level uses the cemento-enamel junction as its reference; recession or enlargement changes their relationship.
Make daily control effective
Demonstrate brushing at the margin and interdental cleaning matched to actual spaces. Use the patient’s attempt to identify access, comfort or understanding problems. Include smoking and diabetes support where relevant. A theoretical routine that cannot be reproduced is unlikely to support lasting professional treatment.
The first treatment step includes practical professional measures as well as motivation and risk control. Remove supragingival and accessible subgingival deposits and improve plaque-retentive margins where appropriate. It should not be reduced to advice alone or delayed until an arbitrary plaque target has been reached without individual clinical reasoning.
Instrument roots with an anatomical plan
Hand instruments and powered scalers can both disrupt deposits. Select tips, adaptation and access for the root surface, furcation or concavity. Provide appropriate anaesthesia, suction and comfort. Work systematically so a difficult distal surface is not missed while the easy facial surface is instrumented repeatedly.
The aim is removal of biofilm and calculus with preservation of tooth tissue. Excessive force or aggressive repeated root planing can sacrifice cementum and increase sensitivity without improving disease control. Tactile smoothness is an incomplete endpoint: a smooth exposed surface does not establish that a hidden concavity or furcation has been adequately treated.
Use adjuncts for an identified purpose
Systemic antibiotics are not routine additions to every periodontal course. Their selected use requires a clinical indication, consideration of evidence and stewardship and, where appropriate, specialist input. Antiseptic and local antimicrobial products also have specific limitations and cannot correct inaccessible anatomy or an ineffective daily routine.
Provide appropriate sensitivity and symptom advice. Repeatedly offering a rinse for a bleeding 7 mm pocket may postpone investigation of remaining deposits, furcation involvement, endodontic disease or fracture. Acute swelling and systemic illness require an acute assessment; they should not be processed as an ordinary maintenance problem.
Reassess after healing
Review after an appropriate healing period, often several weeks to a few months according to the treatment course and clinical circumstances. Compare site-level pocketing, bleeding, suppuration, plaque and symptoms. Review the daily routine and risks before attributing every residual site to resistant bacteria or operator failure.
Pocket reduction can reflect reduced swelling, recession and attachment change in different proportions. It does not prove regeneration. Persistent sites may need focused reinstrumentation, a different access approach or specialist assessment. The amount of inflammation and feasibility of future maintenance matter as well as the measured depth.
Choose the next step from the response
Good self-care with shallow non-bleeding pockets can support transition to supportive care at a risk-based interval. Other patients need further early-step support, correction of a local barrier, focused treatment or referral. Explain the reason for each intervention and the findings that will define improvement.
For example, one non-responding distal molar site after otherwise successful care may reflect a furcation or difficult root form. Probe and review the relevant image before repeating an entire whole-mouth course. Where further improvement is unlikely or declined, acknowledge residual risk and agree a realistic supportive plan rather than describing cure.
A distinction to remember
Persistent pocketing needs reassessment of its cause before repeated instrumentation, surgery or antibiotic prescribing.
One site still bleeds at 7 mm after an otherwise successful course. What would you reassess?
Reveal the reasoning
Check deposits, access, root form, furcation involvement and the quality of previous treatment. An atypical defect may need assessment for endodontic disease or fracture. Focus further treatment or referral on the cause rather than automatically repeating whole-mouth instrumentation.
Test your recall
What is the aim of subgingival instrumentation?
Show answer
Reduce the biofilm and calculus sustaining inflammation while preserving the root surface. A healthier maintainable site is the goal, rather than extensive cementum removal. Success depends on access, daily cleaning, risk control and the tissue response after healing.