
Eruption and development
Read eruption as a sequence of developmental events. Tooth identity, symmetry, space and root maturity are more useful than deciding that every child should match a single eruption chart.
Quick revision summary
Read development as a pattern
Compare eruption sequence, symmetry and dental development with earlier findings. Chronological ages are guides; a missing bulge, retained primary tooth or unexplained asymmetry can be more informative than a single birthday.
Protect the permanent successors
Primary teeth maintain function and contribute to space and development. Consider the successor, root resorption and remaining useful lifespan before treatment, while ensuring that current pain and infection are actively managed.
Investigate an unexpected finding
Count teeth and assess form, position and occlusion. Use justified imaging to answer the specific developmental question, and seek advice when delayed eruption, hypodontia, supernumerary teeth or abnormal resorption changes planning.
Common mistake
Eruption charts describe populations. Do not dismiss unilateral failure of eruption because the child is still within a broad normal age range.
Eruption and development
Read eruption as a sequence of developmental events. Tooth identity, symmetry, space and root maturity are more useful than deciding that every child should match a single eruption chart.
How a tooth reaches the mouth
Tooth development proceeds through initiation, morphogenesis, crown mineralisation and root formation. Enamel defects reflect injury during formation; enamel does not remodel after eruption. Root formation continues after a permanent crown emerges, so a newly erupted incisor can have a wide canal, thin dentinal walls and an open apex. This distinction explains why preserving living pulp after injury can strengthen the eventual root.
Eruption is coordinated with alveolar bone remodelling and dental follicle activity. It is not simply a completed root pushing the crown upwards. Primary roots undergo physiological resorption as successors develop and approach. Retention, ankylosis or absence of a successor can alter this pattern; apparent immobility of an overdue primary tooth deserves a diagnosis.
Tooth development: cap, bell and root formation
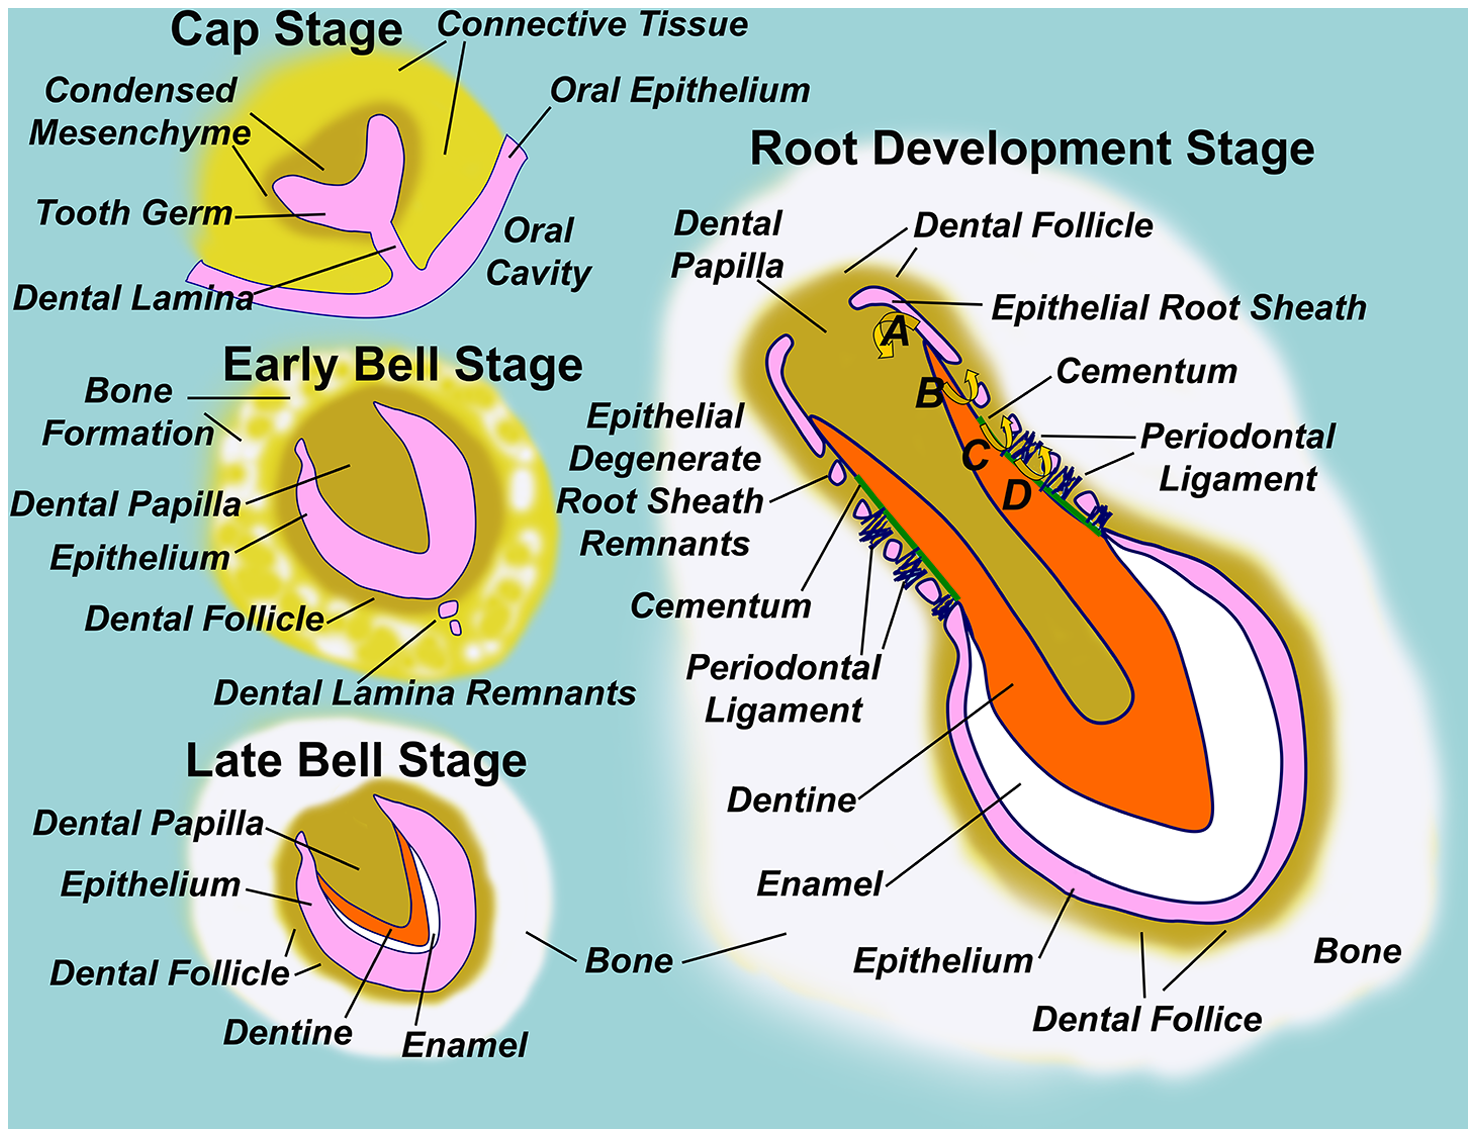
Follow the dental lamina, enamel organ, dental papilla and dental follicle through development. Locate the epithelial root sheath in the root-development panel.
Diagram illustrating normal tooth formation.png · Sarrafpour B, Swain M, Li Q, Zoellner H · CC BY 4.0. None; reproduced without alteration.
Which structure gives rise to dentine and pulp?
The dental papilla. The enamel organ gives rise to enamel; the dental follicle contributes to supporting periodontal tissues.
Recognise the normal sequence
The primary dentition contains 20 teeth: incisors, canines and molars, with no premolars. Most children develop their first primary incisors in infancy and complete the primary dentition in the toddler years. Permanent first molars erupt behind the primary second molars, usually around six to seven years; no primary tooth is shed to make way for them. Families can therefore mistake a vulnerable permanent molar for a baby tooth.
Mixed dentition commonly extends from approximately six to twelve years, but ranges vary. Lower incisors and first molars appear early; replacement of primary canines and molars occurs later. Record actual teeth rather than assuming identity from age. The primary second molar is replaced by a second premolar, not by a permanent molar.
Mixed dentition on a panoramic radiograph
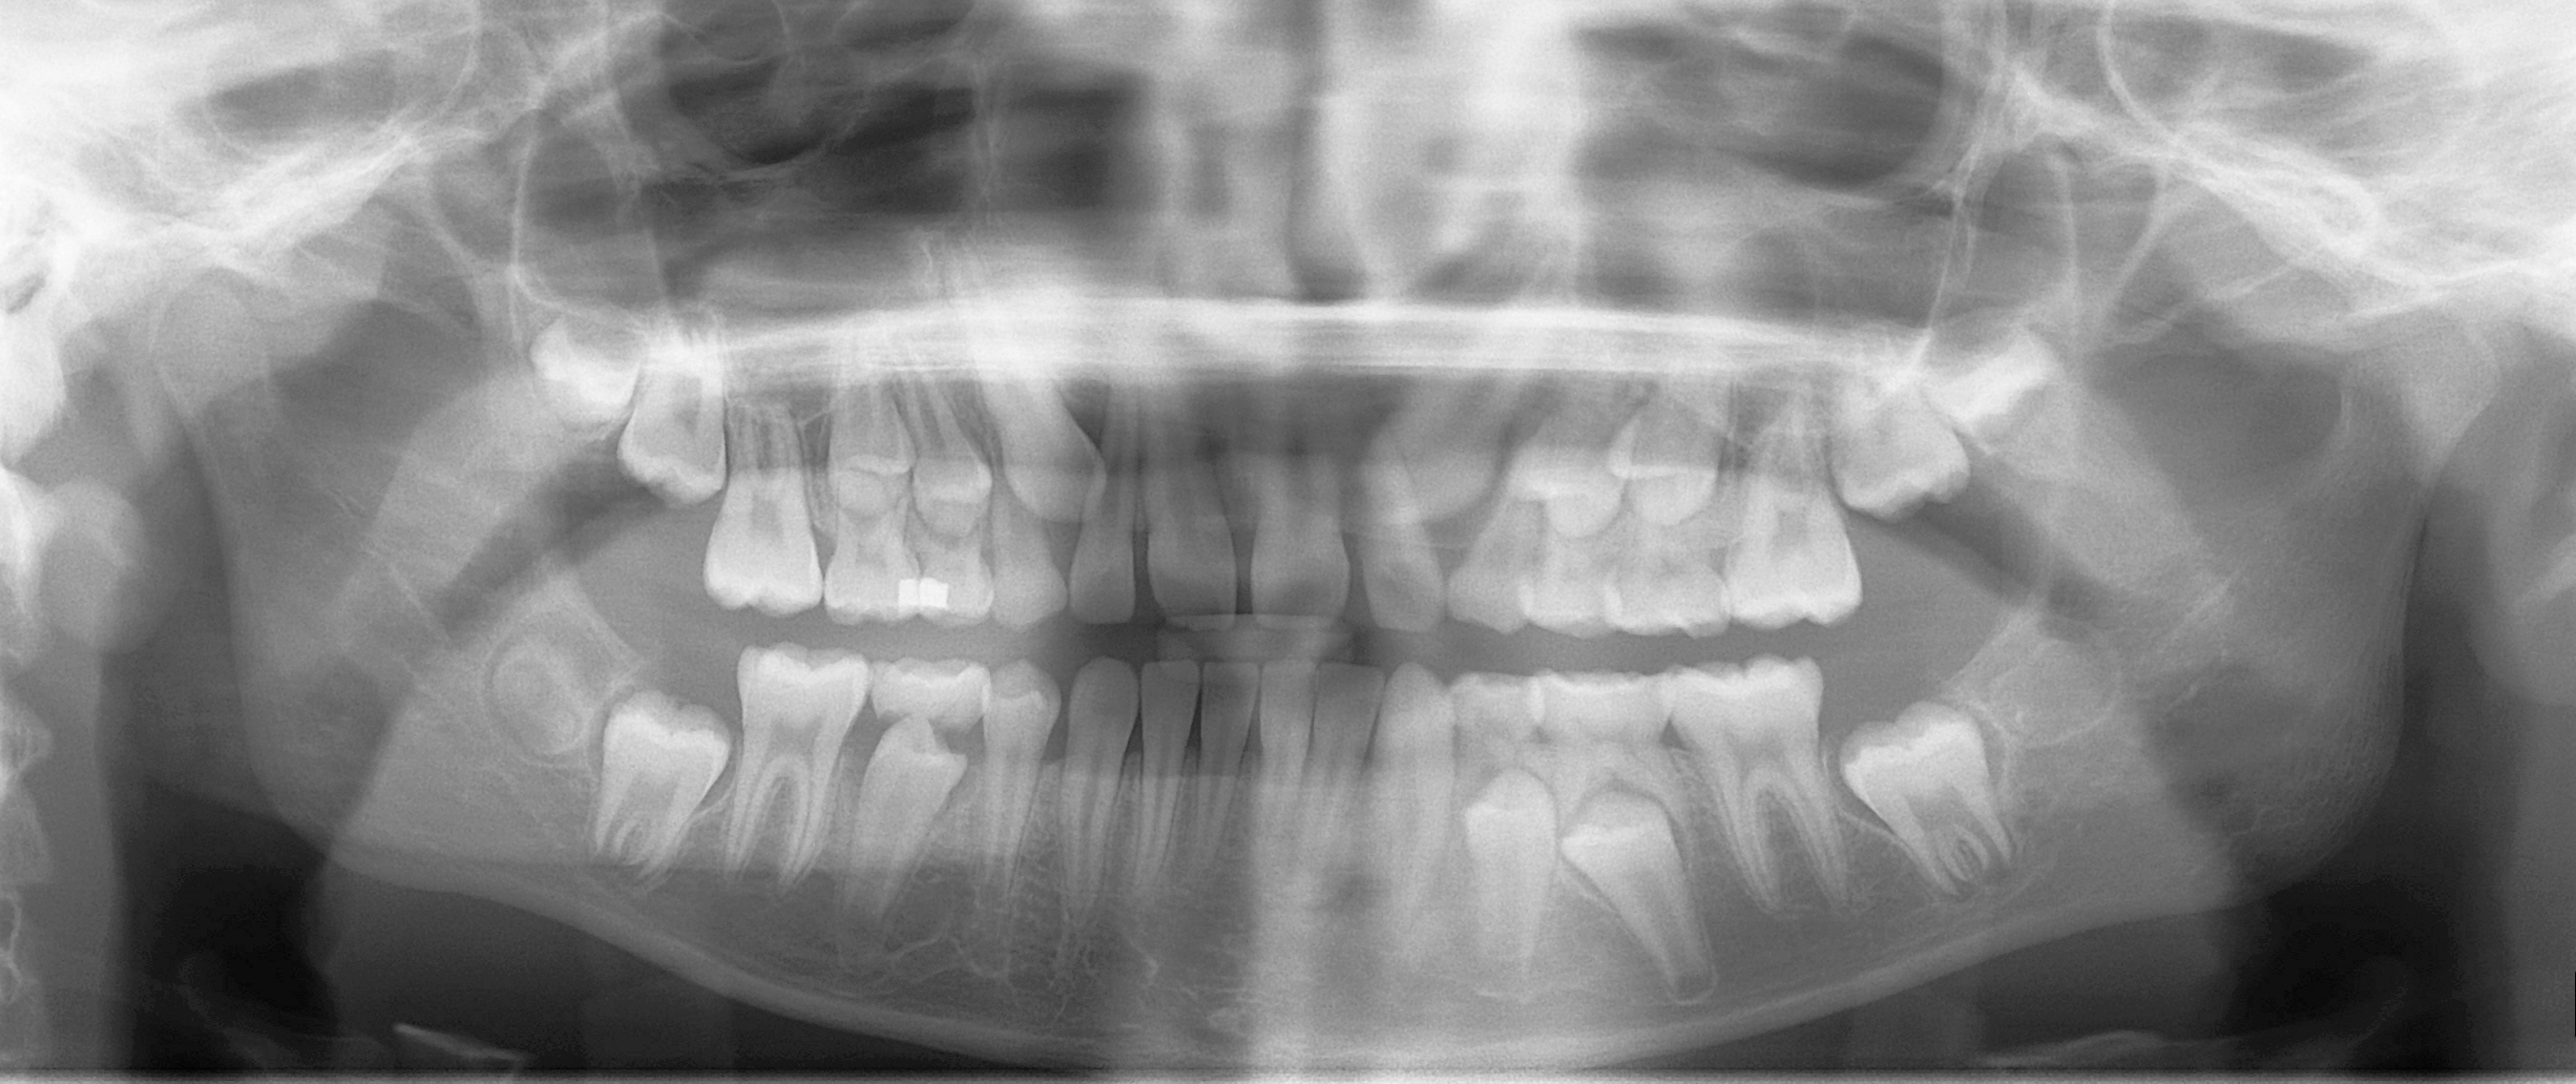
Distinguish erupted permanent teeth, retained primary teeth and unerupted successors. Compare development on the two sides and account for every permanent tooth. This is one published example of mixed dentition, not a fixed age-based template for every child.
Mixed dentition pan.jpg · Coronation Dental Specialty Group · CC BY 3.0. None; original image reproduced without alteration.
Which permanent teeth erupt without replacing primary teeth?
The permanent molars. Premolars replace the primary molars; permanent incisors and canines replace their primary predecessors.
Space and the transition between dentitions
Spacing in primary dentition provides room for larger permanent incisors. Leeway space is the combined size difference between primary canine/molar segments and their permanent successors, and is generally greater in the mandible. Mesial migration of molars can consume it. Early primary molar loss may therefore worsen crowding, especially when a first permanent molar is erupting.
A space assessment includes arch length, tooth widths, existing crowding, molar relationship and successor position. A space maintainer preserves selected space; it does not create space already lost or guarantee ideal alignment. Appliance benefit must exceed plaque retention, breakage, follow-up and eruption-interference risks. It is a planned intervention rather than an automatic consequence of extraction.
When an eruption pattern warrants investigation
Compare matching teeth, retained predecessors and the sequence across each arch. Marked unilateral delay, an upper lateral incisor appearing before the central incisor, a retained primary tooth with no successor evident clinically, or a palpable swelling can indicate obstruction or displacement. Ask about earlier trauma or infection, previous extractions and familial missing teeth.
Local causes include supernumerary teeth, odontomes, dilaceration, ectopia, inadequate space and ankylosed primary teeth. Generalised delay may accompany an overall developmental variation or a systemic disorder. Distinguish these patterns clinically before requesting images. Inspect and palpate canine regions during mixed-dentition review; an absent or asymmetric bulge at the expected developmental stage warrants further assessment.
Choose imaging to answer the question
A periapical or occlusal view can assess an unerupted incisor, obstruction or root shape; parallax from suitable views can establish buccopalatal position. A panoramic image may be appropriate when the full developing dentition is relevant, for example multiple missing teeth or coordinated extraction planning. Check existing images before repeating exposure.
Identify the tooth, successor, root stage, eruption path, space and relation to neighbouring roots on the report. CBCT is reserved for a question conventional images cannot adequately resolve when the answer will alter care. Age alone, a routine orthodontic assessment or the wish for a three-dimensional picture does not justify it.
Plan and monitor development
Removing an obstruction can permit spontaneous eruption if space and the eruption path are favourable, but some teeth also need exposure and orthodontic traction. Severe displacement, dilaceration or ankylosis reduces predictability. Agree the objective and review interval with the relevant team, and explain the possible need for further treatment before intervening.
Follow-up must document movement, symmetry, space and any new symptoms rather than simply “still waiting”. Preserving pulp in an immature permanent tooth, retaining a useful primary tooth without a successor, and extracting a poor-prognosis molar are different developmental decisions. A symptom-free interval is not proof that eruption will correct itself.
A distinction to remember
Eruption charts describe populations. Do not dismiss unilateral failure of eruption because the child is still within a broad normal age range.
An eight-year-old has an erupted upper lateral incisor beside a retained primary central incisor. What needs checking?
Reveal the reasoning
Investigate the unerupted permanent central incisor rather than simply waiting for the primary tooth to fall out. Examine space, the predecessor and trauma history, then use justified imaging to assess obstruction, position and root form. Specialist input may be needed.
Test your recall
Which primary teeth are replaced by premolars?
Show answer
The primary first and second molars are replaced by the permanent first and second premolars. Permanent molars erupt behind the primary dentition. Counting and identifying teeth prevents an erupting first permanent molar being mistaken for a primary second molar.