
Oral lichen planus
Oral lichen planus is a chronic immune-mediated mucosal disorder with appearances ranging from symptom-free white striae to painful erosions. Lichenoid reactions can resemble it. Management combines diagnosis, symptom control and surveillance for focal change; treatment aims for useful function and comfort rather than a guaranteed permanent cure.
Quick revision summary
Connect mechanism with the clinical pattern
An interface inflammatory response damages basal epithelial cells, producing white keratotic changes, erythema and sometimes erosion. Reticular, plaque-like, atrophic and erosive patterns can coexist. Buccal mucosa, tongue and gingiva are commonly involved, often in a bilateral or multifocal distribution.
Start with local measures and education
Explain the chronic fluctuating course and that it is not a contagious infection. Identify individual food or product irritants without imposing an unnecessary restrictive diet. Support gentle plaque control with suitable aids and a tolerable fluoride toothpaste; gingival soreness can otherwise create a cycle of plaque accumulation and further inflammation.
Monitor for focal change and explain uncertainty
There is a small long-term malignant transformation risk associated with the lichen planus/lichenoid framework, although estimates depend on definitions and cohorts. Regular review should be risk-based and assess the whole mouth.
Common mistake
Known lichen planus must not become an explanation for every new ulcer. Focal persistent change needs a fresh assessment even when surrounding striae are familiar.
Oral lichen planus and lichenoid disease: diagnosis and control
Oral lichen planus is a chronic immune-mediated mucosal disorder with appearances ranging from symptom-free white striae to painful erosions. Lichenoid reactions can resemble it. Management combines diagnosis, symptom control and surveillance for focal change; treatment aims for useful function and comfort rather than a guaranteed permanent cure.
Connect mechanism with the clinical pattern
An interface inflammatory response damages basal epithelial cells, producing white keratotic changes, erythema and sometimes erosion. Reticular, plaque-like, atrophic and erosive patterns can coexist. Buccal mucosa, tongue and gingiva are commonly involved, often in a bilateral or multifocal distribution.
A reticular pattern can be asymptomatic, whereas erythematous or erosive areas may sting with food or make brushing difficult. Desquamative gingivitis describes the red, peeling gingival appearance rather than the underlying diagnosis. Blistering disorders and other inflammatory disease can produce a similar gingival pattern.
Oral lichen planus: reticular white striae
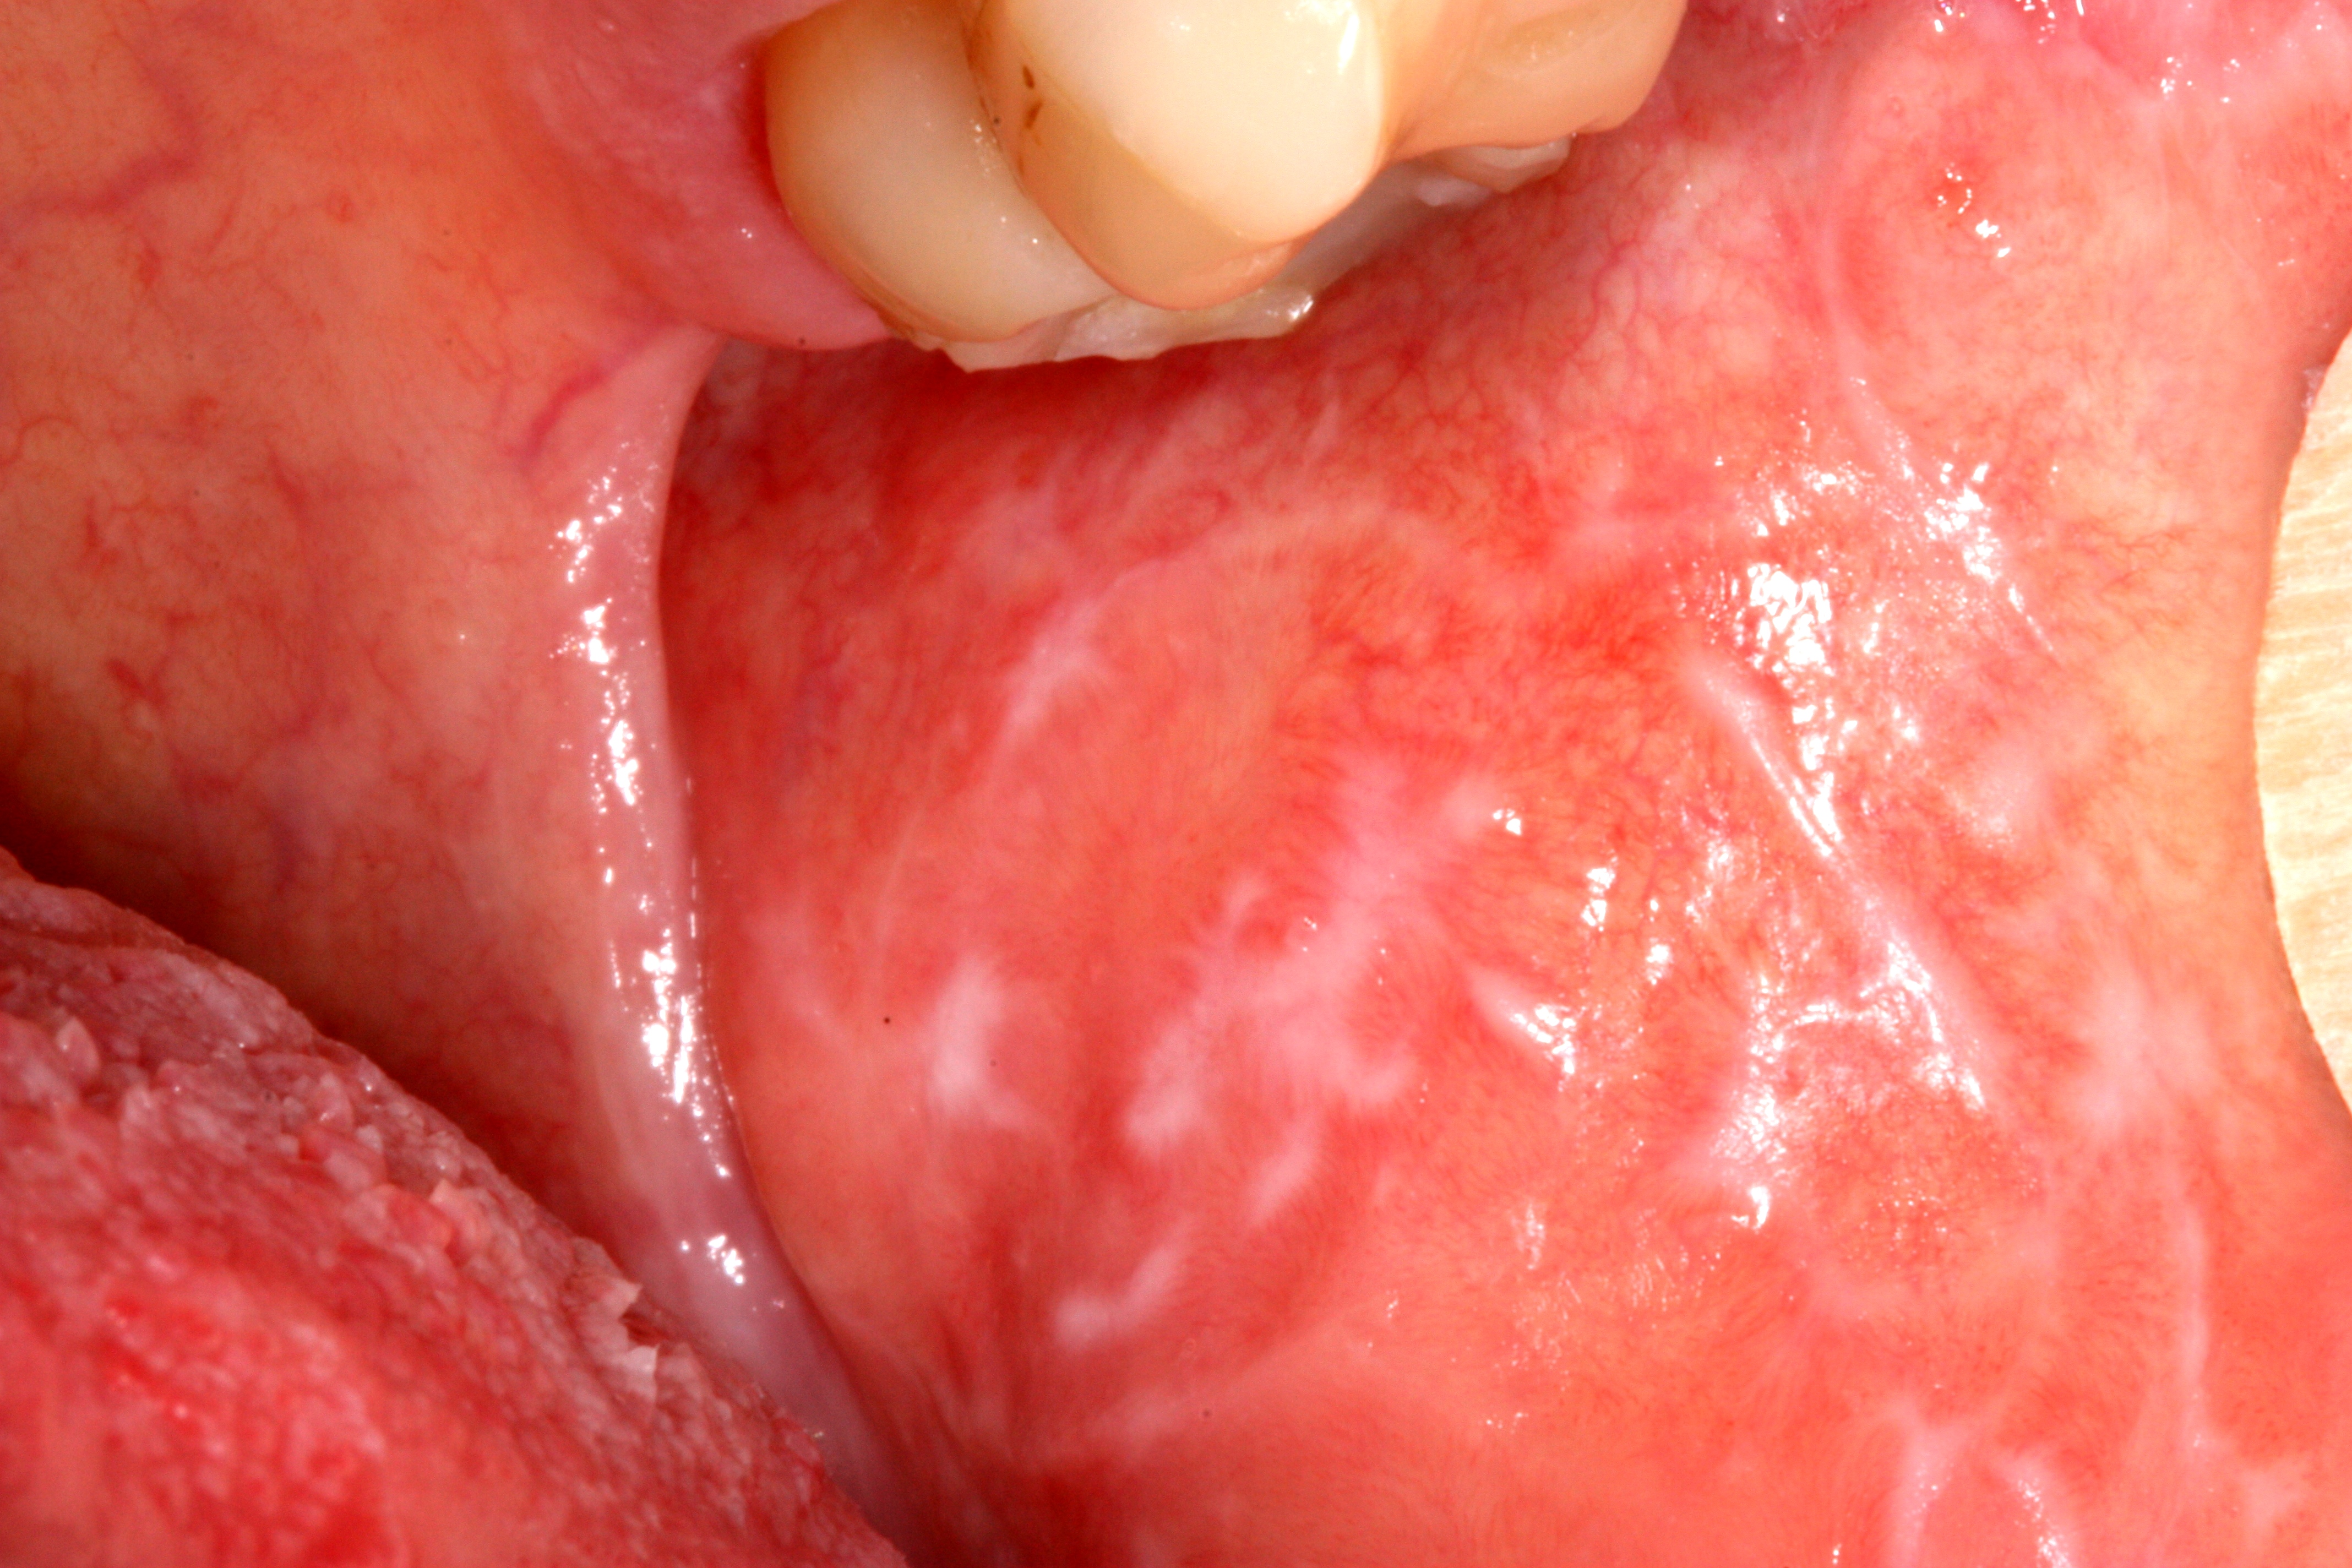
Follow the fine, intersecting white lines across the buccal mucosa. The source identifies this as non-erosive oral lichen planus. In practice, examine the distribution elsewhere in the mouth and consider lichenoid reactions; a photograph cannot establish the full clinical or histological diagnosis.
Lichen_planus.jpg · Ian Furst · CC BY-SA 4.0. Source image reproduced without alteration; any arrows or circles are part of the original.
Which visible feature gives this lesion a reticular pattern?
The interlacing white striae form a lace-like network. Describe that pattern before interpreting it, then correlate with distribution, history and appropriate clinical assessment.
Take a focused mucocutaneous history
Ask about duration, fluctuation, food sensitivity, bleeding, oral hygiene and effects on nutrition. Record skin, scalp, nail, genital or other mucosal symptoms and previous treatments. Medicine history and chronology matter because some drug-related lichenoid reactions can resemble the disorder.
Record dental materials and whether a lesion is localised in a plausible contact relationship. A unilateral contact lesion can support a different discussion from widespread bilateral disease, but proximity to a restoration is not proof of causation. Do not stop prescribed medicines or replace all restorations simply because a lichenoid appearance is present.
Oral lichen planus: a mixed red and white appearance
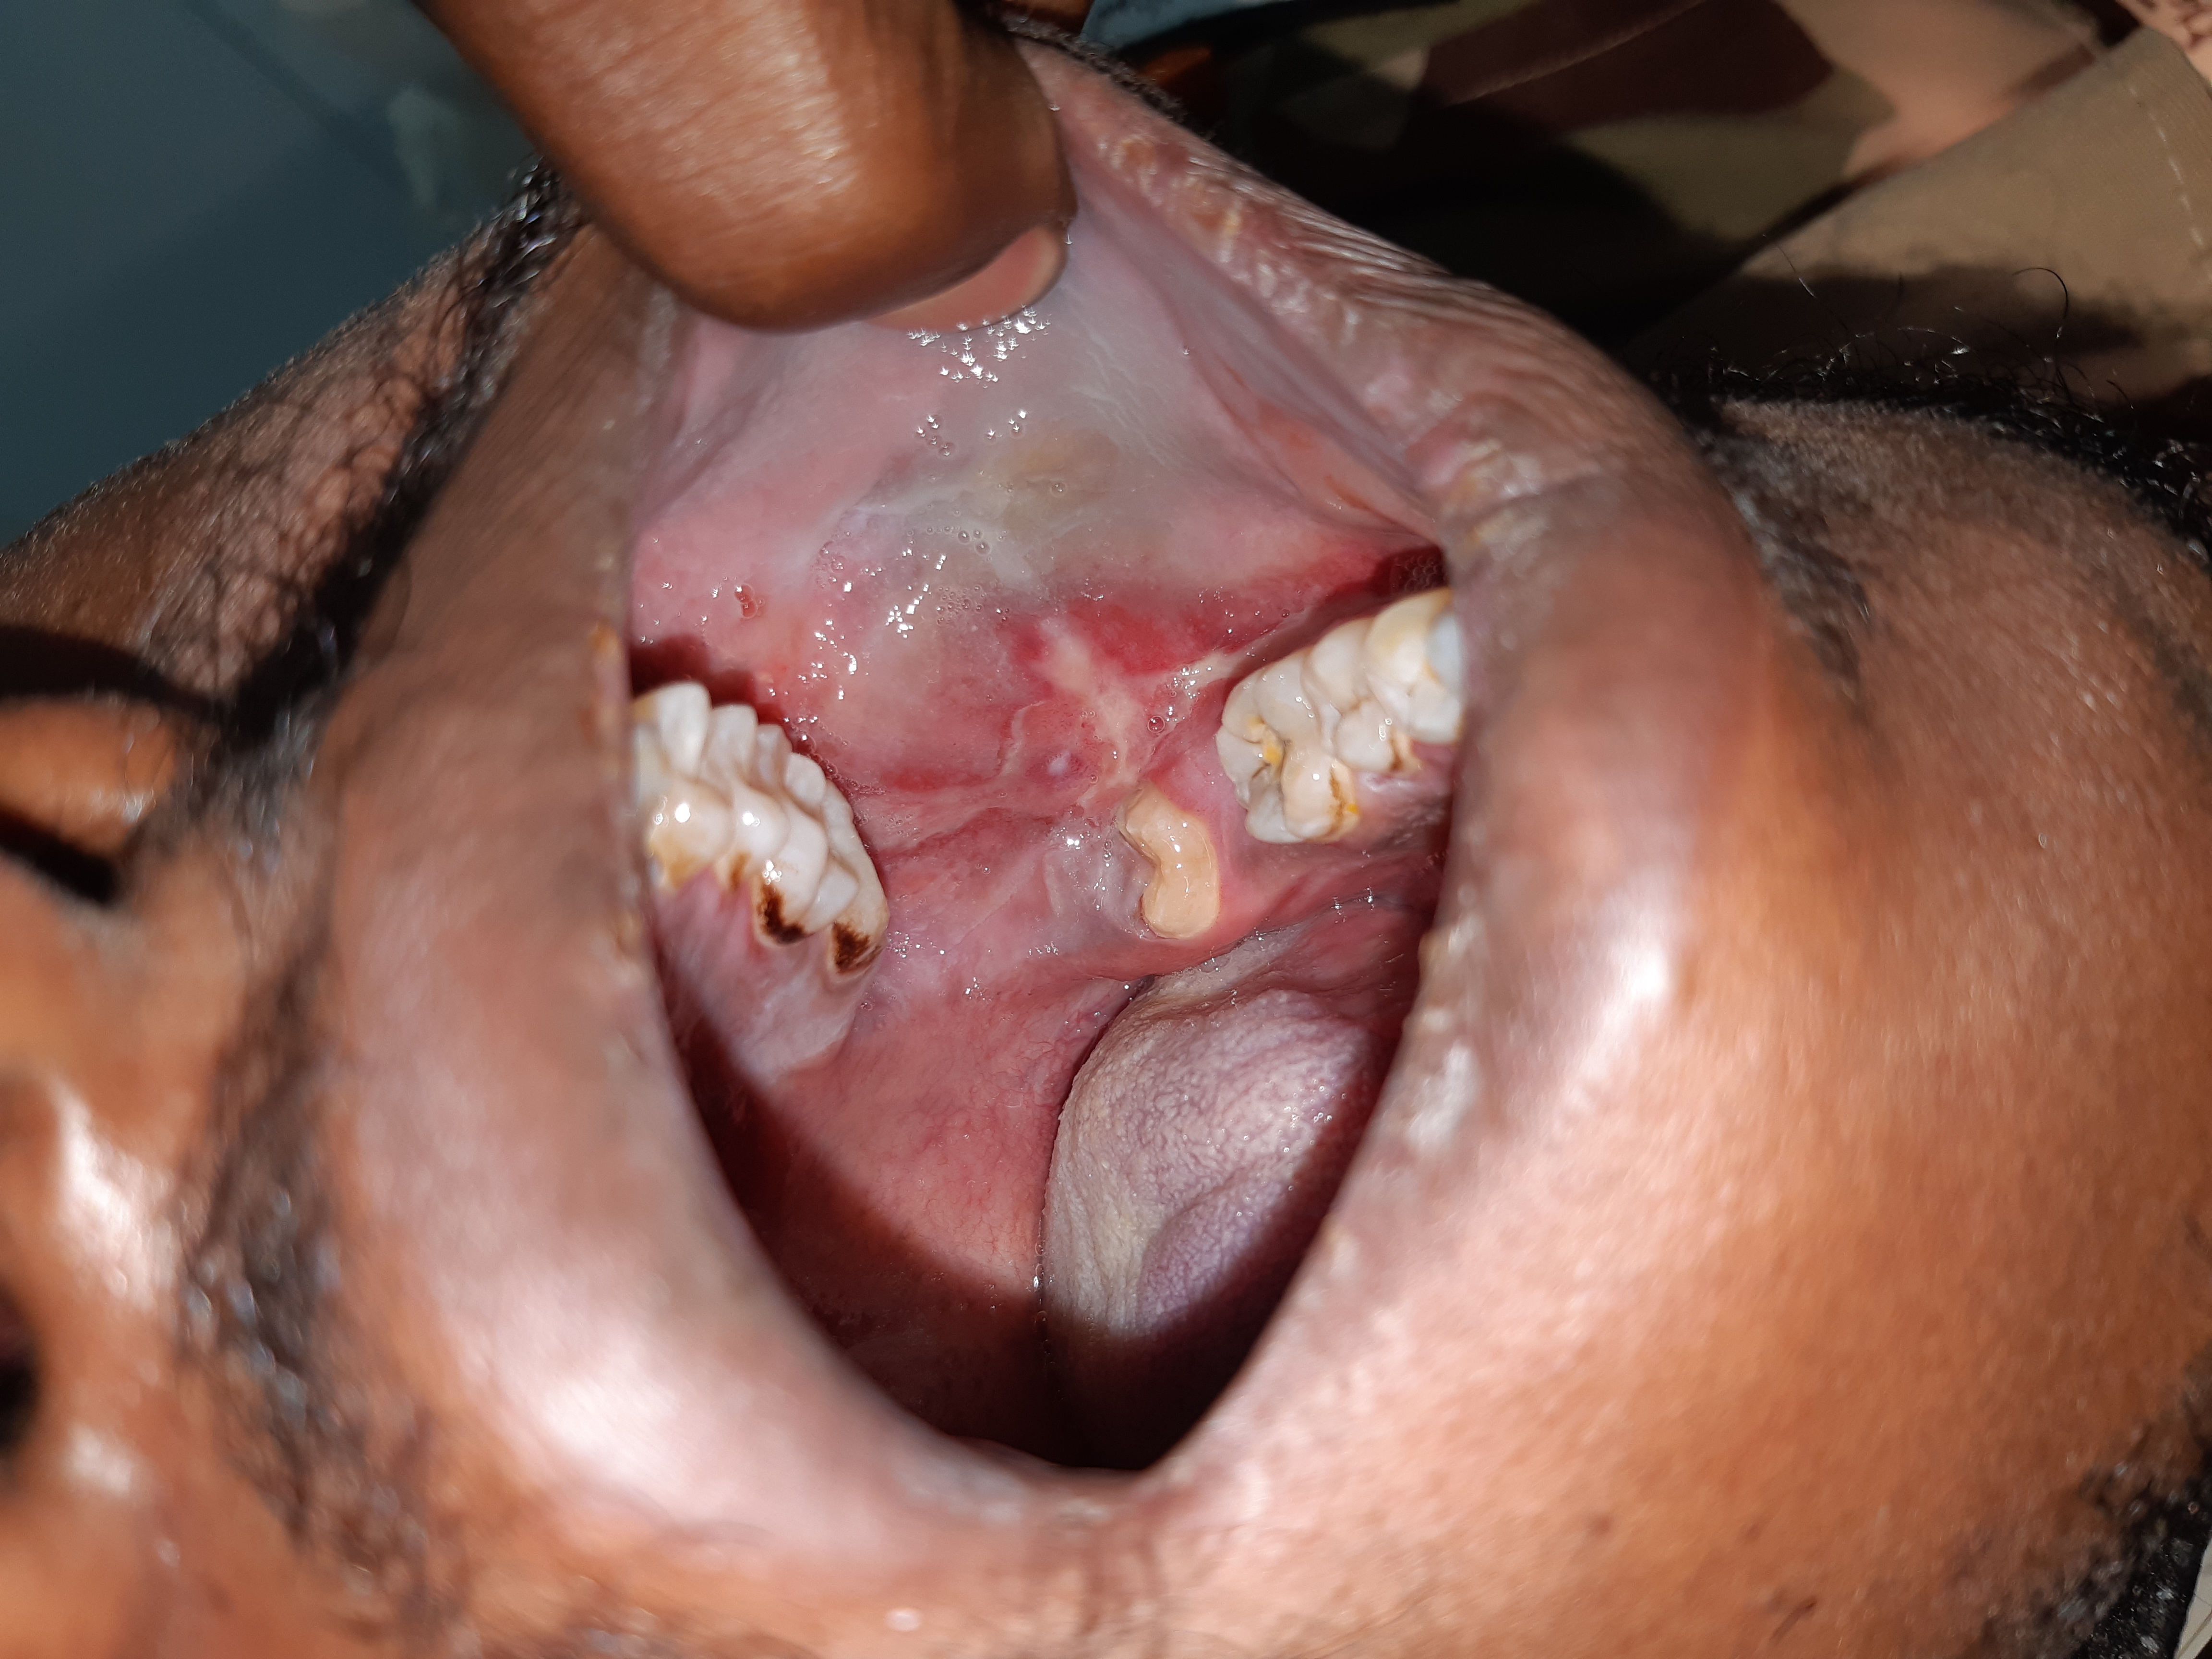
Compare the white striae and thicker white areas with the adjacent erythematous mucosa. The source labels this case oral lichen planus. A red or ulcerated area needs assessment in its own right: symptoms, change, induration and a persistent focal abnormality matter, even when a background lichenoid pattern is familiar.
Lichen_planus-intra_oral_lesion.jpg · Syed Wali Peeran · CC BY-SA 4.0. Source image reproduced without alteration; any arrows or circles are part of the original.
Does recognising a lichenoid pattern explain every red area in the photograph?
No. Describe and assess each significant area. Lichenoid disease, trauma, infection and dysplasia can overlap clinically; a persistent or changing focal lesion may need specialist assessment and biopsy.
Establish the diagnosis and its limits
Examine and map the distribution and identify focal thickening, ulceration or induration. Biopsy is often needed where the diagnosis is uncertain or atypical, and to investigate a changing area. The clinical and histological pattern should agree; lichenoid histology is not a promise that all tissue is free of dysplasia.
Consider candidosis, leukoplakia, lupus-related change and autoimmune blistering disease in the differential according to the findings. Direct immunofluorescence may be required for an appropriate blistering question, with separate sampling and transport. A single familiar-looking white patch should not bypass assessment of persistent focal disease.
Start with local measures and education
Explain the chronic fluctuating course and that it is not a contagious infection. Identify individual food or product irritants without imposing an unnecessary restrictive diet. Support gentle plaque control with suitable aids and a tolerable fluoride toothpaste; gingival soreness can otherwise create a cycle of plaque accumulation and further inflammation.
Address sharp surfaces, denture trauma and other credible irritants. Asymptomatic reticular disease may need explanation and monitoring rather than medication. Treat comfort and function, not the ambition to eliminate every white line. Record baseline symptoms to judge whether treatment provides a meaningful benefit.
Use topical therapy with a review plan
Topical corticosteroid preparations are commonly used for symptomatic inflammatory disease, selected for lesion distribution and patient needs through the appropriate prescribing pathway. A rinse, gel or other delivery system reaches tissues differently; instructions must explain application and avoid confusion about swallowing. Check formulation, licensing and individual contraindications.
Monitor symptoms, oral examination and possible candidosis. Analgesic preparations can help selected patients maintain eating or brushing but do not treat the immune mechanism. Persistent symptoms despite suitable therapy should prompt review of diagnosis, delivery, adherence, infection and triggers before simply increasing treatment.
Recognise when specialist systemic care is needed
Severe, extensive or refractory disease may need systemic treatment or other immune-modifying therapy under specialist care. These choices require discussion of benefit, infection risk, interactions and monitoring. Extraoral disease may need dermatology or another specialty, especially where mucosal function is affected.
If a medicine or contact reaction is suspected, coordinate any change with the prescriber or specialist and assess response. Improvement does not necessarily prove causality, and the systemic indication for a medicine remains important. A patient should not be asked to trade essential medical treatment for an untested oral hypothesis.
Monitor for focal change and explain uncertainty
There is a small long-term malignant transformation risk associated with the lichen planus/lichenoid framework, although estimates depend on definitions and cohorts. Regular review should be risk-based and assess the whole mouth. Avoid guaranteeing safety or presenting one population percentage as an individual prediction.
A new persistent focal ulcer, nodule, induration or changing patch needs independent reassessment and possible biopsy. Do not explain every later lesion as the established inflammatory disease. Provide a route for earlier contact, support risk reduction and ensure that pathology results and surveillance responsibilities are clear.
A distinction to remember
Known lichen planus must not become an explanation for every new ulcer. Focal persistent change needs a fresh assessment even when surrounding striae are familiar.
A patient with established lichen planus develops a firm ulcer at one tongue site that does not heal. What next?
Reveal the reasoning
Assess it as a new persistent focal lesion and arrange appropriate specialist investigation or suspected-cancer referral. Do not assume that it is merely another flare. Document the site, induration, duration and nodes, with representative biopsy when indicated.
Test your recall
Which appearance supports oral lichen planus?
Show answer
Bilateral or multifocal reticular white striae, sometimes combined with erythema or erosions, support the diagnosis. Tongue, buccal and gingival sites can be involved. Distribution and histological correlation matter; an isolated white plaque alone is less specific and may require further assessment.