
Local anaesthetic safety
Understand membrane penetration and sodium-channel block, then use anatomy and technique to explain failure. Adding more drug without identifying the problem increases exposure without guaranteeing success.
Quick revision summary
From solution to conduction block
Local anaesthetics reversibly inhibit voltage-gated sodium channels in nerve axons. The uncharged fraction crosses the membrane; the charged form interacts with the channel from the intracellular side.
Calculate the dose from concentration and volume
A percentage concentration expresses grams per 100 mL. For example, a 2% solution contains 20 mg/mL, so 2.2 mL contains 44 mg of the local anaesthetic.
Assess a reaction from its pattern and timing
Ask what happened during a previous “allergic” episode: pallor, faintness, palpitations, rash, wheeze, swelling, altered consciousness and timing provide different clues. A label without the event history can obscure vasovagal symptoms, an adrenaline effect, toxicity or true hypersensitivity.
Common mistake
Dose arithmetic, product limits and the patient’s clinical suitability are three related but separate checks.
Local anaesthetic science and failed anaesthesia
Understand membrane penetration and sodium-channel block, then use anatomy and technique to explain failure. Adding more drug without identifying the problem increases exposure without guaranteeing success.
From solution to conduction block
Local anaesthetics reversibly inhibit voltage-gated sodium channels in nerve axons. The uncharged fraction crosses the membrane; the charged form interacts with the channel from the intracellular side. Preventing effective depolarisation interrupts propagation. This differs from neuromuscular-junction blockade and from central sedation.
These drugs are weak bases. At lower tissue pH, more drug is ionised outside the nerve, so membrane penetration can be reduced. pKa, lipid solubility, protein binding, vascularity and the formulation influence onset, potency or duration in different ways. A vasoconstrictor can reduce local absorption and prolong effect, but it introduces its own patient-specific considerations.
Stages and threshold of an action potential
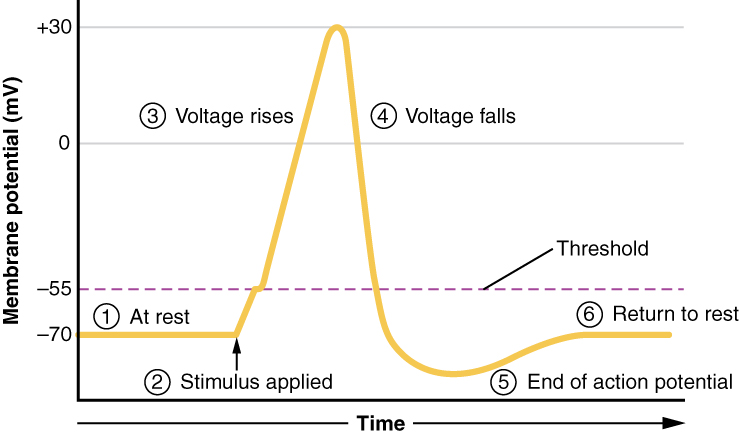
Trace threshold, depolarisation, repolarisation and after-hyperpolarisation. Recall sodium-channel opening during the rising phase and relate sodium-channel blockade to local anaesthesia. The plotted voltages illustrate a representative cell.
Stages and threshold of an action potential · OpenStax (Anatomy and Physiology, 2016 version) · CC BY 4.0. Unchanged published image; displayed responsively. Original publication.
Systematic reasons for failure
| Possible reason | Clue / assessment | Better response than repetition alone |
|---|---|---|
| Incorrect placement / anatomy | Expected territory not numb; landmarks or approach uncertain | Reassess landmarks and appropriate technique. |
| Incomplete soft-tissue coverage | Tooth anaesthetised but buccal / lingual tissues sensitive | Consider the relevant separate nerve supply. |
| Accessory innervation | Partial or unexpected distribution | Choose an appropriate supplementary technique within competence. |
| Inflamed / infected tissue | Altered tissue environment and sensitisation | Address source and use suitable alternative / supplementary anaesthesia. |
| Insufficient onset time | Injection recent; effect still developing | Allow time and test clinically before treatment. |
| Wrong source / pain mechanism | Symptoms do not fit the treated tooth or tissue | Reassess diagnosis rather than assuming more LA will solve it. |
Trigeminal nerve & dental branches
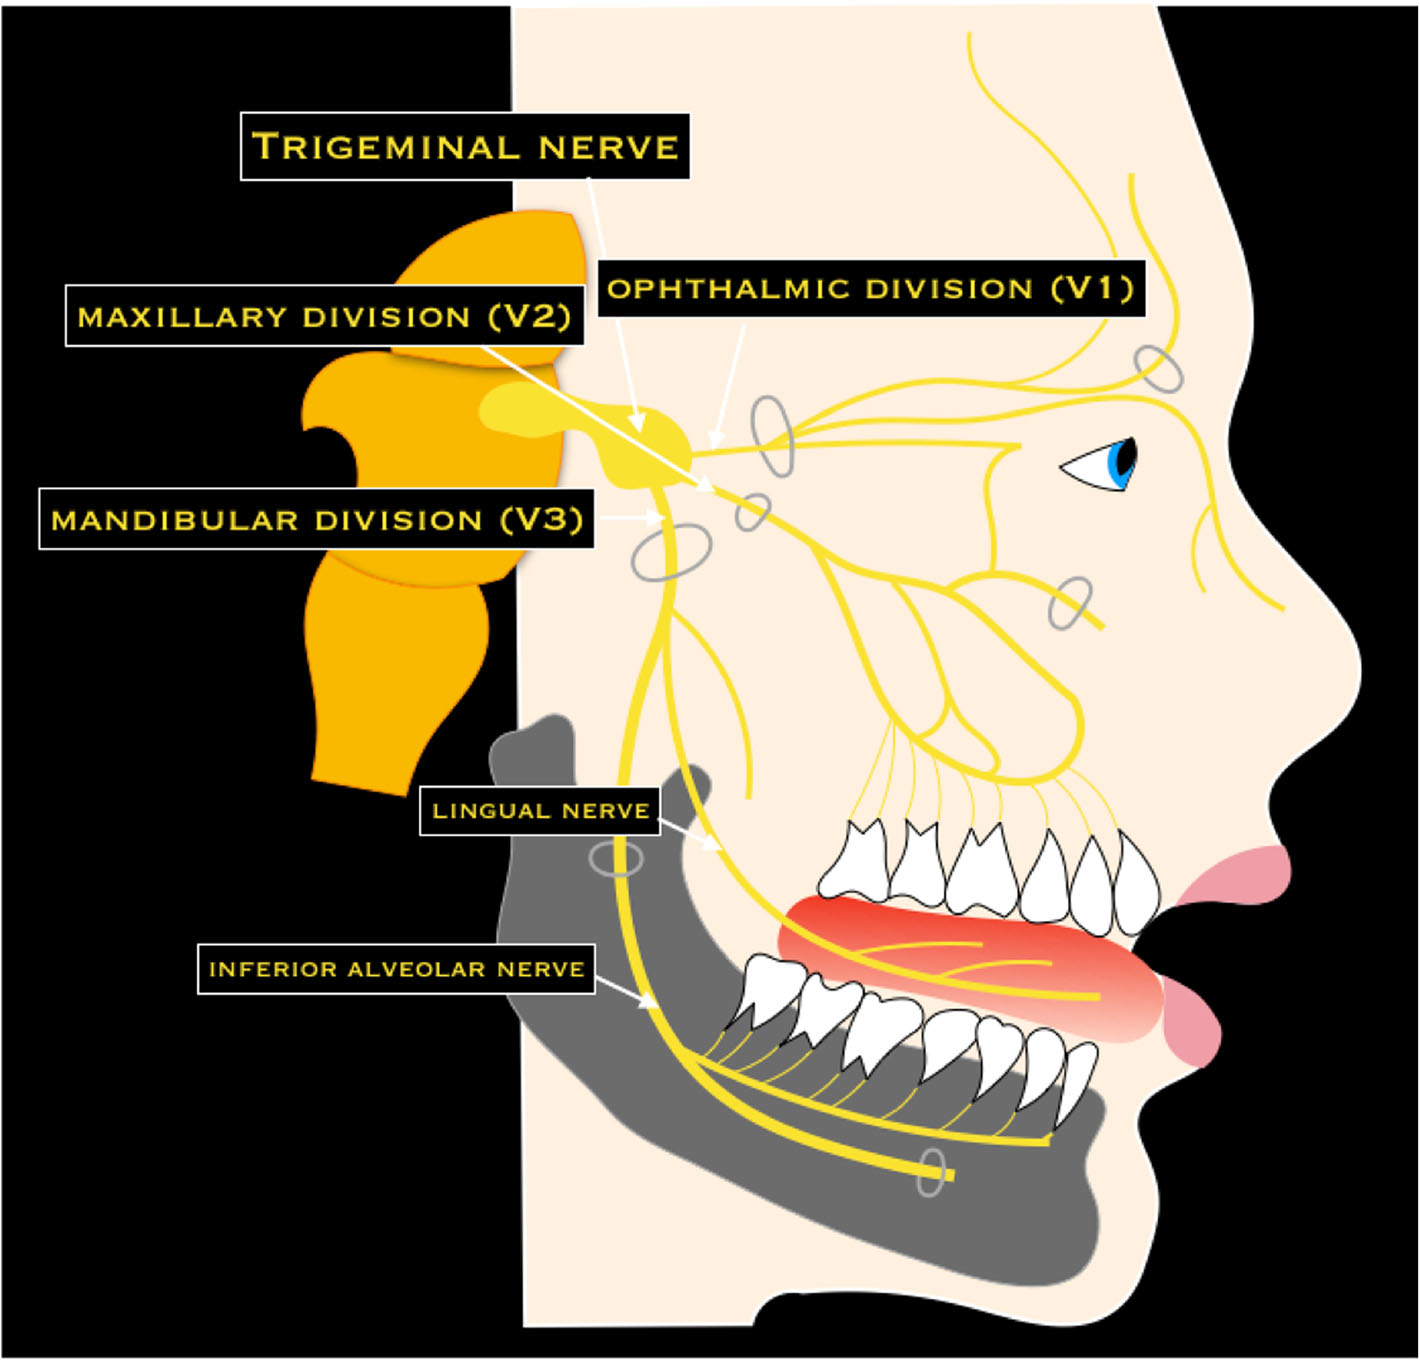
Trace V1, V2 and V3, then the lingual and inferior alveolar nerves. Connect each to the sensory examination after lower third-molar surgery. This is a branch overview, rather than an injection-placement diagram.
Trigeminal nerve & dental branches · Nicola Romano, Margherita Federici and Antonio Castaldi · CC BY 4.0. Original image; displayed at a responsive size. Original publication.
Dose and injection safety
Use the actual concentration and cartridge volume, account for previous doses and apply current product limits to the patient. Aspirate and use careful controlled administration according to the technique; a negative aspiration does not eliminate every intravascular risk. Protect the patient from soft-tissue injury while anaesthetised.
Perioral symptoms, tinnitus, altered conscious state, excitation or seizures can signal systemic toxicity, with potential cardiovascular deterioration. Anxiety, vasovagal symptoms and adrenaline effects can overlap with early presentations, so use the pattern, timing and ABCDE findings. Stop injection and obtain appropriate support when toxicity is suspected.
Trigeminal divisions and facial sensory territories
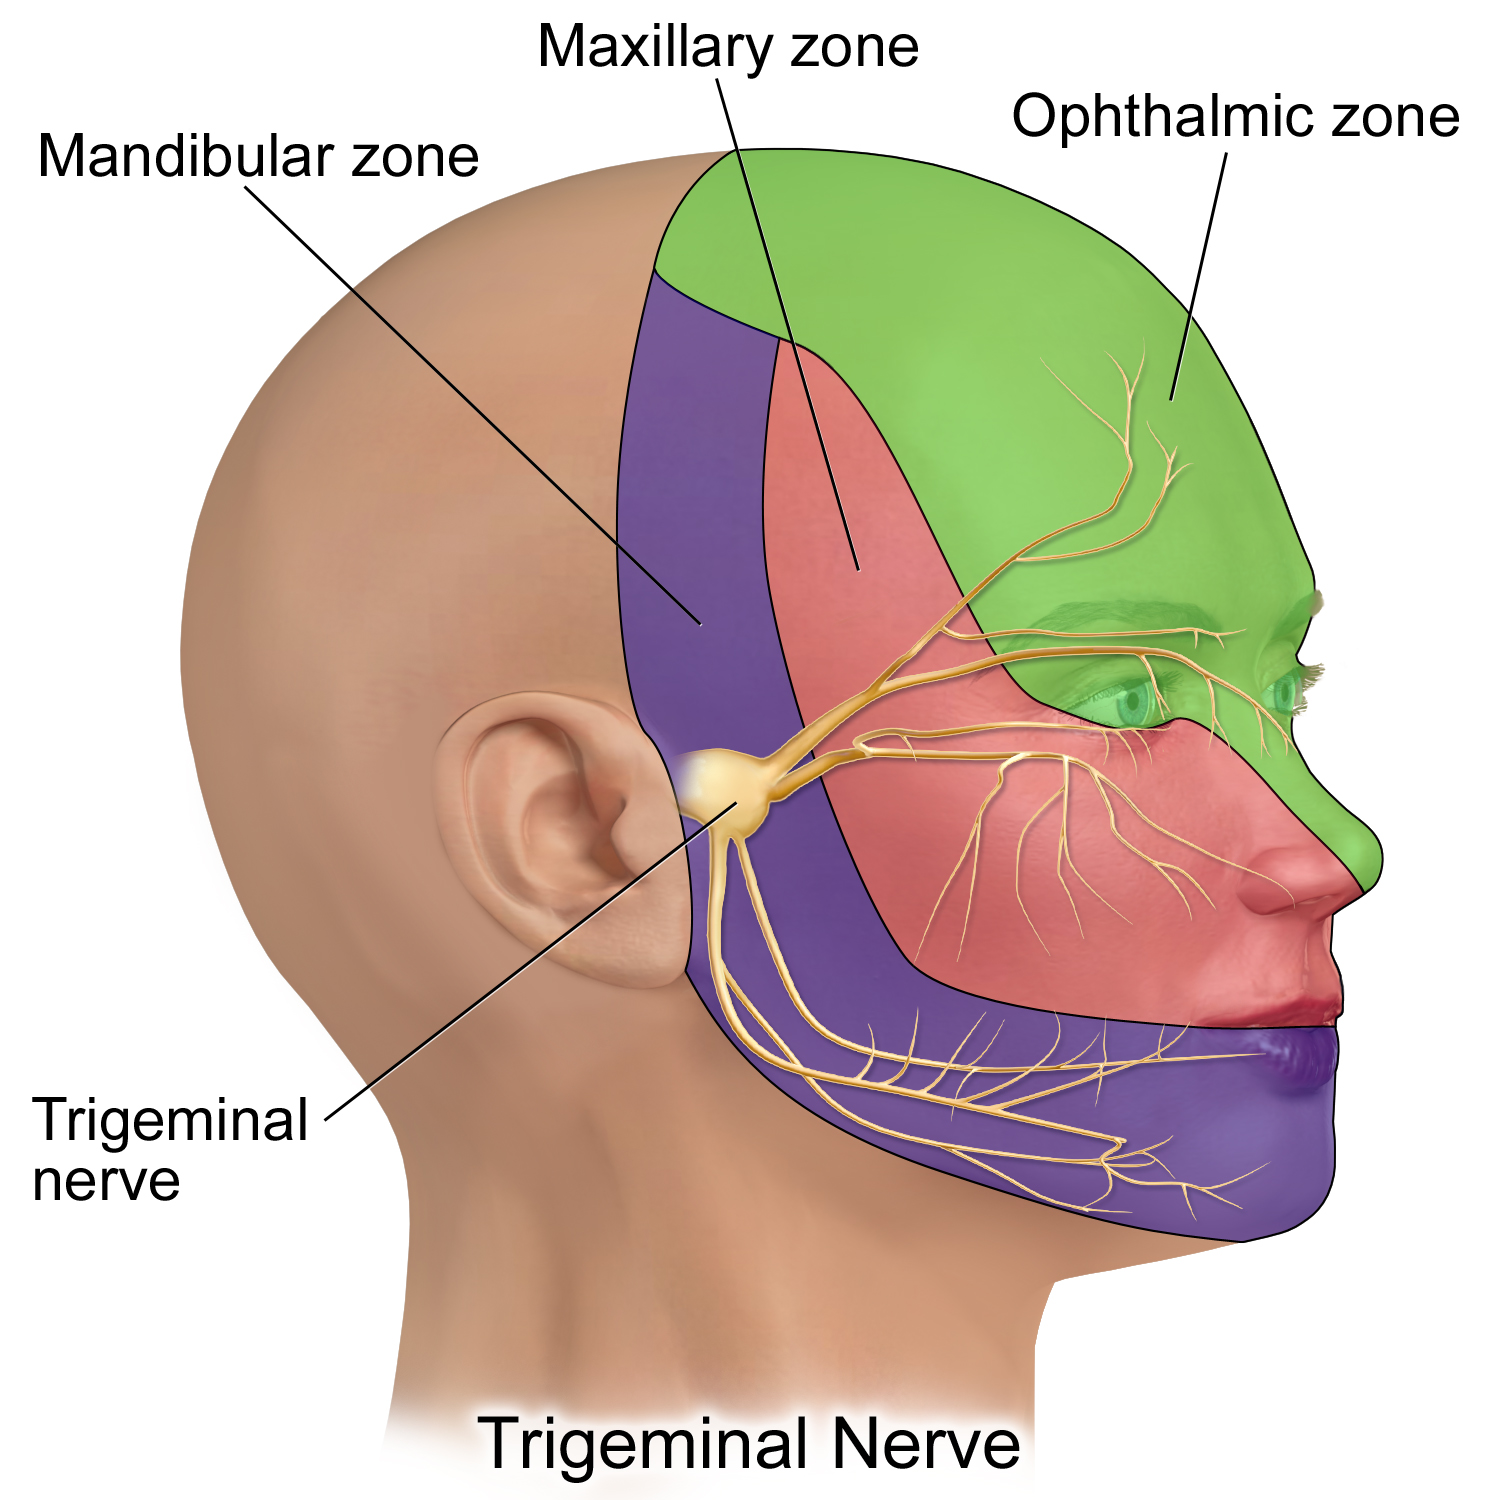
V1 is ophthalmic, V2 maxillary and V3 mandibular. This is a schematic sensory territory map, not a detailed map of every peripheral branch; V3 also carries motor fibres.
Trigeminal Nerve.png · BruceBlaus · CC BY-SA 4.0. None; reproduced without alteration.
Which division gives rise to the inferior alveolar and lingual nerves?
The mandibular division, V3. Distinguish lower lip/chin sensory change from altered tongue sensation.
Calculate the dose from concentration and volume
A percentage concentration expresses grams per 100 mL. For example, a 2% solution contains 20 mg/mL, so 2.2 mL contains 44 mg of the local anaesthetic. This is a calculation example, not a recommended dose. Check the actual cartridge volume, product, vasoconstrictor, prior administrations and the patient’s characteristics against current product guidance.
Do not infer a safe maximum from cartridge count alone. Different formulations and cartridge sizes deliver different amounts, and combined agents require consideration of cumulative toxicity. Record the medicine and total quantity actually given. If a further dose is being considered after ineffective anaesthesia, first reassess technique and diagnosis rather than assuming that more volume is the solution.
Maxillary and mandibular dental nerve branches
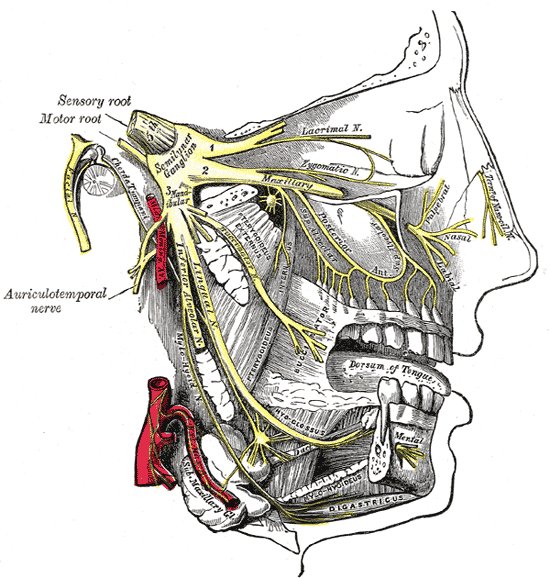
Follow V2 toward the upper teeth and V3 toward the lingual and inferior alveolar nerves. The original terms “inferior dental” and “submaxillary ganglion” correspond to inferior alveolar nerve and submandibular ganglion. This shows anatomy; it does not specify a safe needle trajectory.
Gray778.png · Henry Vandyke Carter; reproduced in Gray’s Anatomy (1918), plate 778 · Public domain. None; original image reproduced without alteration.
Which nerve continues through the mental foramen?
The mental branch of the inferior alveolar nerve, providing sensation to the lower lip and chin. The incisive branch continues within the mandible.
Assess a reaction from its pattern and timing
Ask what happened during a previous “allergic” episode: pallor, faintness, palpitations, rash, wheeze, swelling, altered consciousness and timing provide different clues. A label without the event history can obscure vasovagal symptoms, an adrenaline effect, toxicity or true hypersensitivity. Do not dismiss a serious reaction simply because allergy is uncommon.
Stop administration when an unexpected reaction develops, assess ABCDE and obtain the appropriate help. Suspected local-anaesthetic systemic toxicity can progress from neurological features to cardiovascular collapse and needs an emergency response. Follow current emergency guidance and the service’s trained rescue arrangements. Document the exposure, observations, response and subsequent advice so future clinicians can assess the event accurately.
A distinction to remember
Dose arithmetic, product limits and the patient’s clinical suitability are three related but separate checks.
Why can a numb lower lip coexist with pain during lower-molar treatment?
Reveal the reasoning
Mental-territory numbness shows an effect in part of the IAN distribution, but does not prove complete pulpal or soft-tissue anaesthesia. Reassess technique, onset, supplementary nerve supply, inflammation and the actual pain source.
Guidance to read alongside this chapter
Test your recall
Why ask about prior reactions to local anaesthetic?
Show answer
To distinguish allergy, toxicity, anxiety and other events.