
Facial trauma and mandibular fractures
Assess the whole patient before the fracture pattern.
Clinical images and diagrams
Adult mandible: labelled lateral anatomy
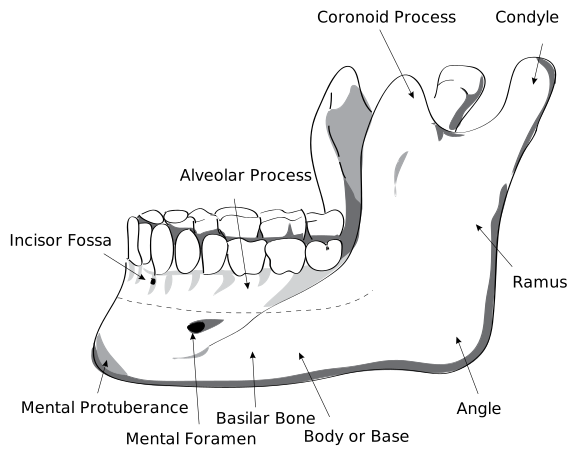
Locate the body, ramus, angle, condylar process, coronoid process and mental foramen. Use the labels to distinguish the two superior processes and the landmarks relevant to local anaesthesia and surgery.
HumanMandibleLeft.svg · Djexplo · CC0. None; reproduced without alteration.
Which nerve emerges through the mental foramen?
The mental nerve, a terminal branch of the inferior alveolar nerve, supplying the lower lip and chin.
Mandibular body fracture: follow the cortex
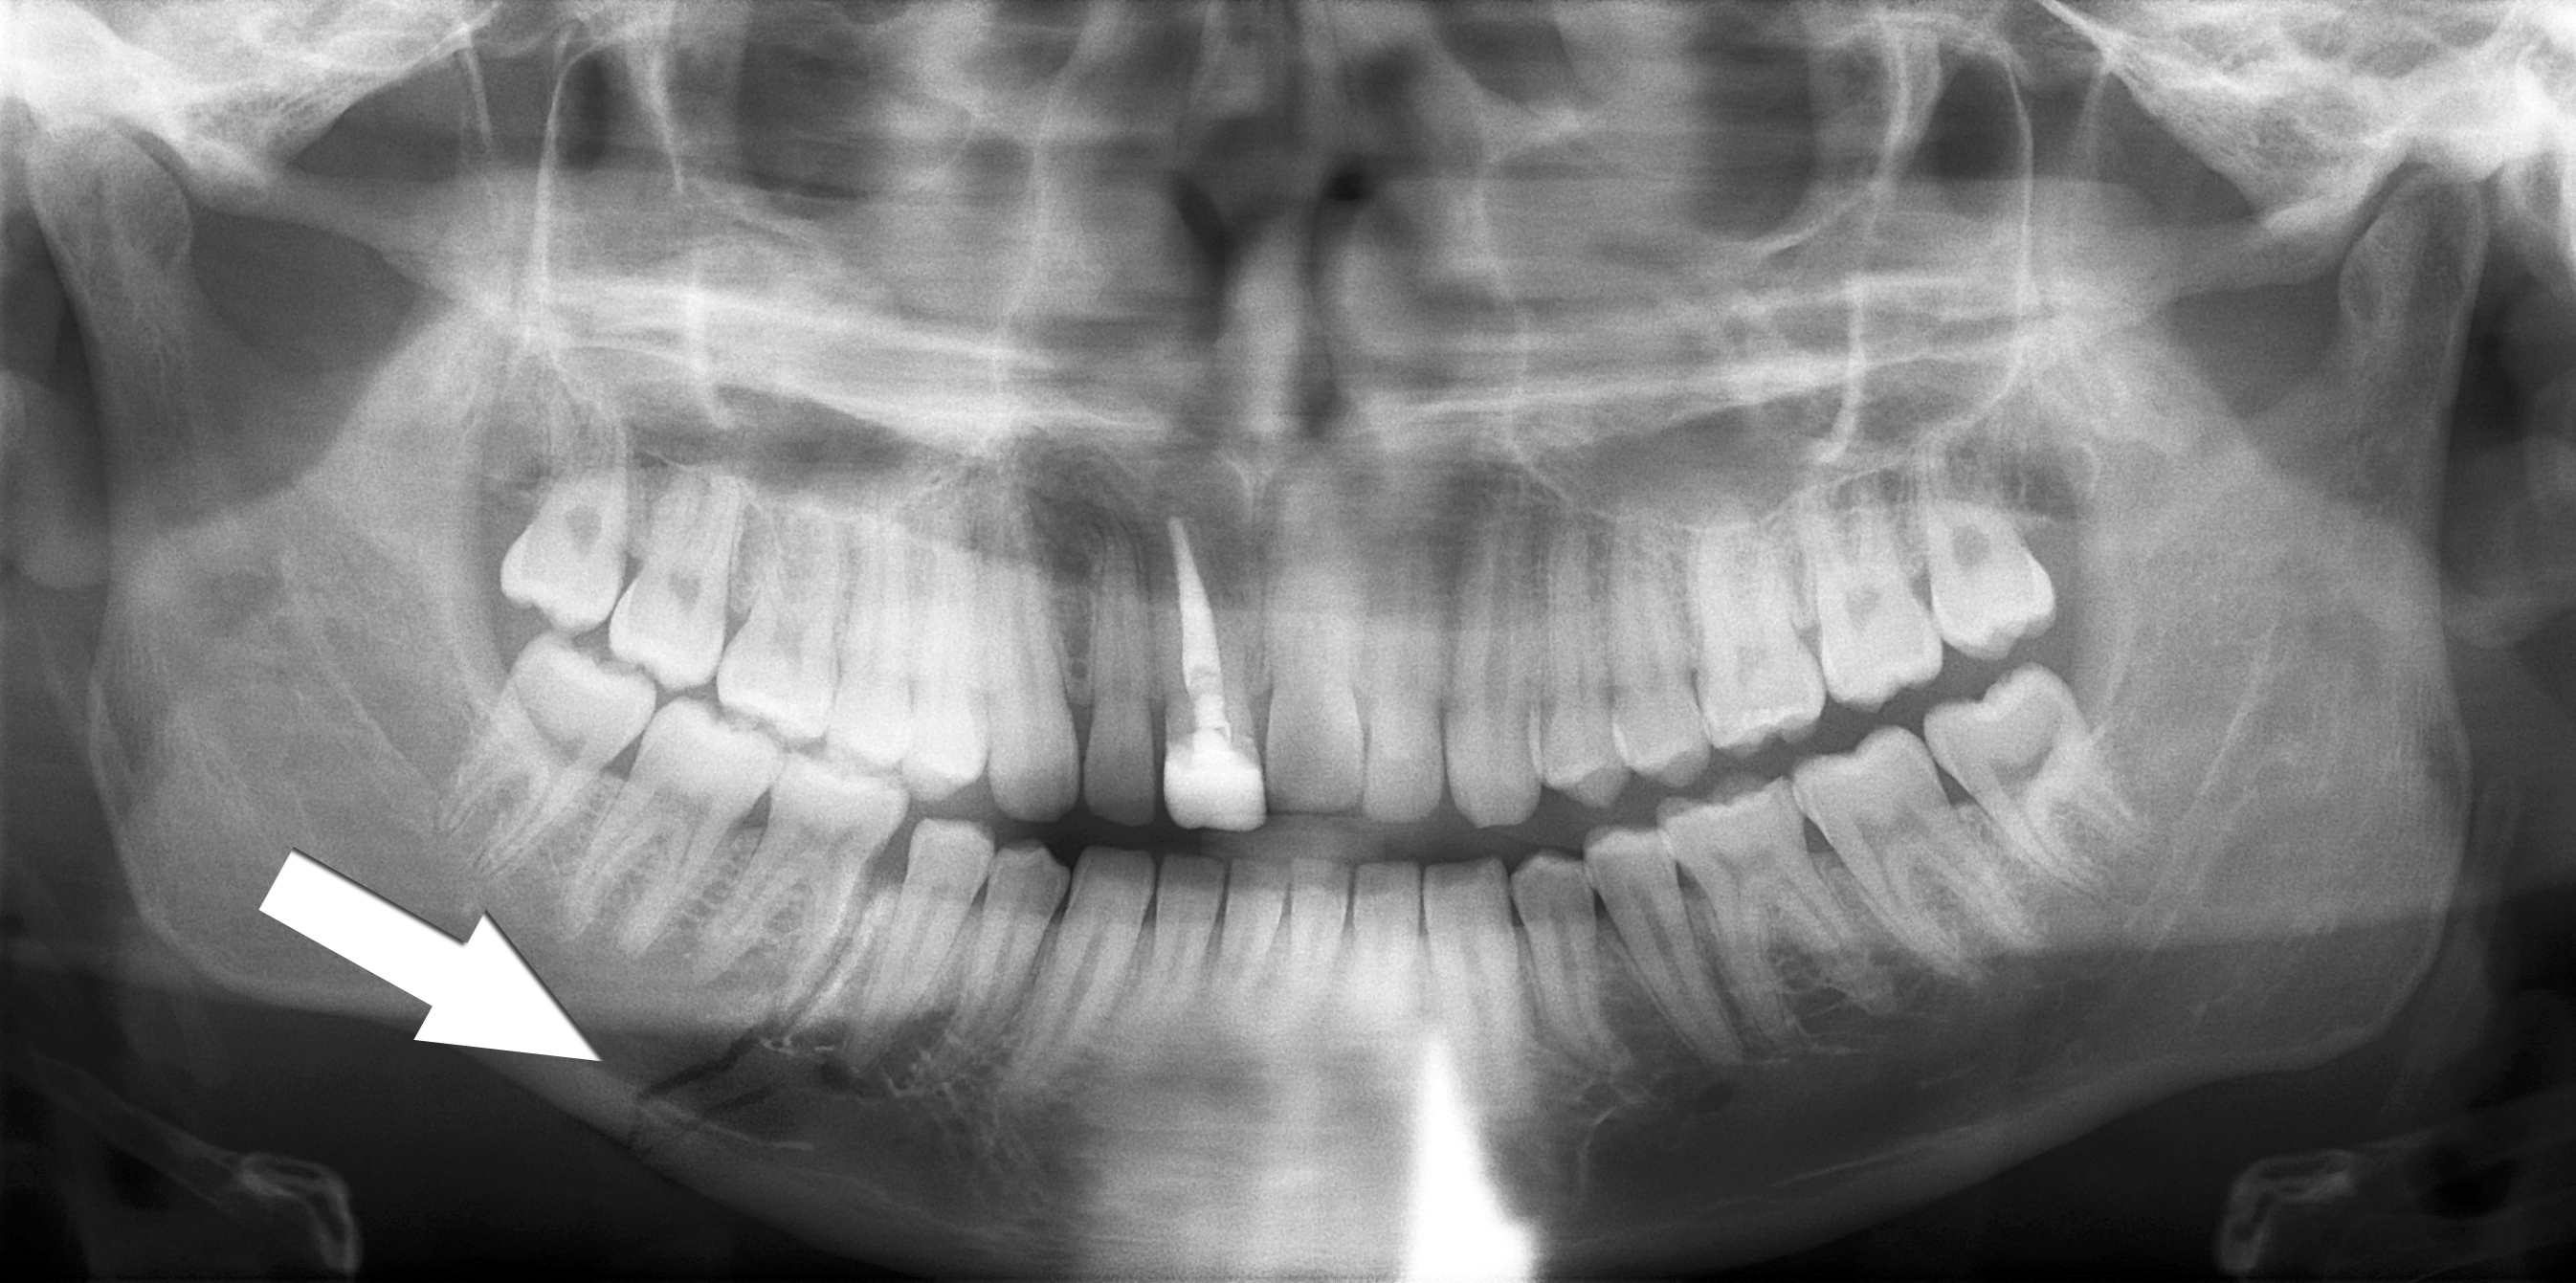
Trace the lower mandibular border through the fracture marked by the source arrow. Inspect the teeth and the remaining mandible as well as the marked site. The source describes a right body fracture. Clinical occlusion, soft tissues, sensation and the mechanism of injury remain part of the trauma assessment.
Simple mandible fracture.jpg · Coronation Dental Specialty Group · CC BY 3.0. Reproduced without alteration. Labels, arrows and circles, where present, belong to the source image.
Why should the search continue after finding the marked fracture?
Another fracture or associated injury may be present. Review the whole image and the patient’s clinical findings rather than stopping at the first abnormality.
Multiple mandibular fractures: inspect every region
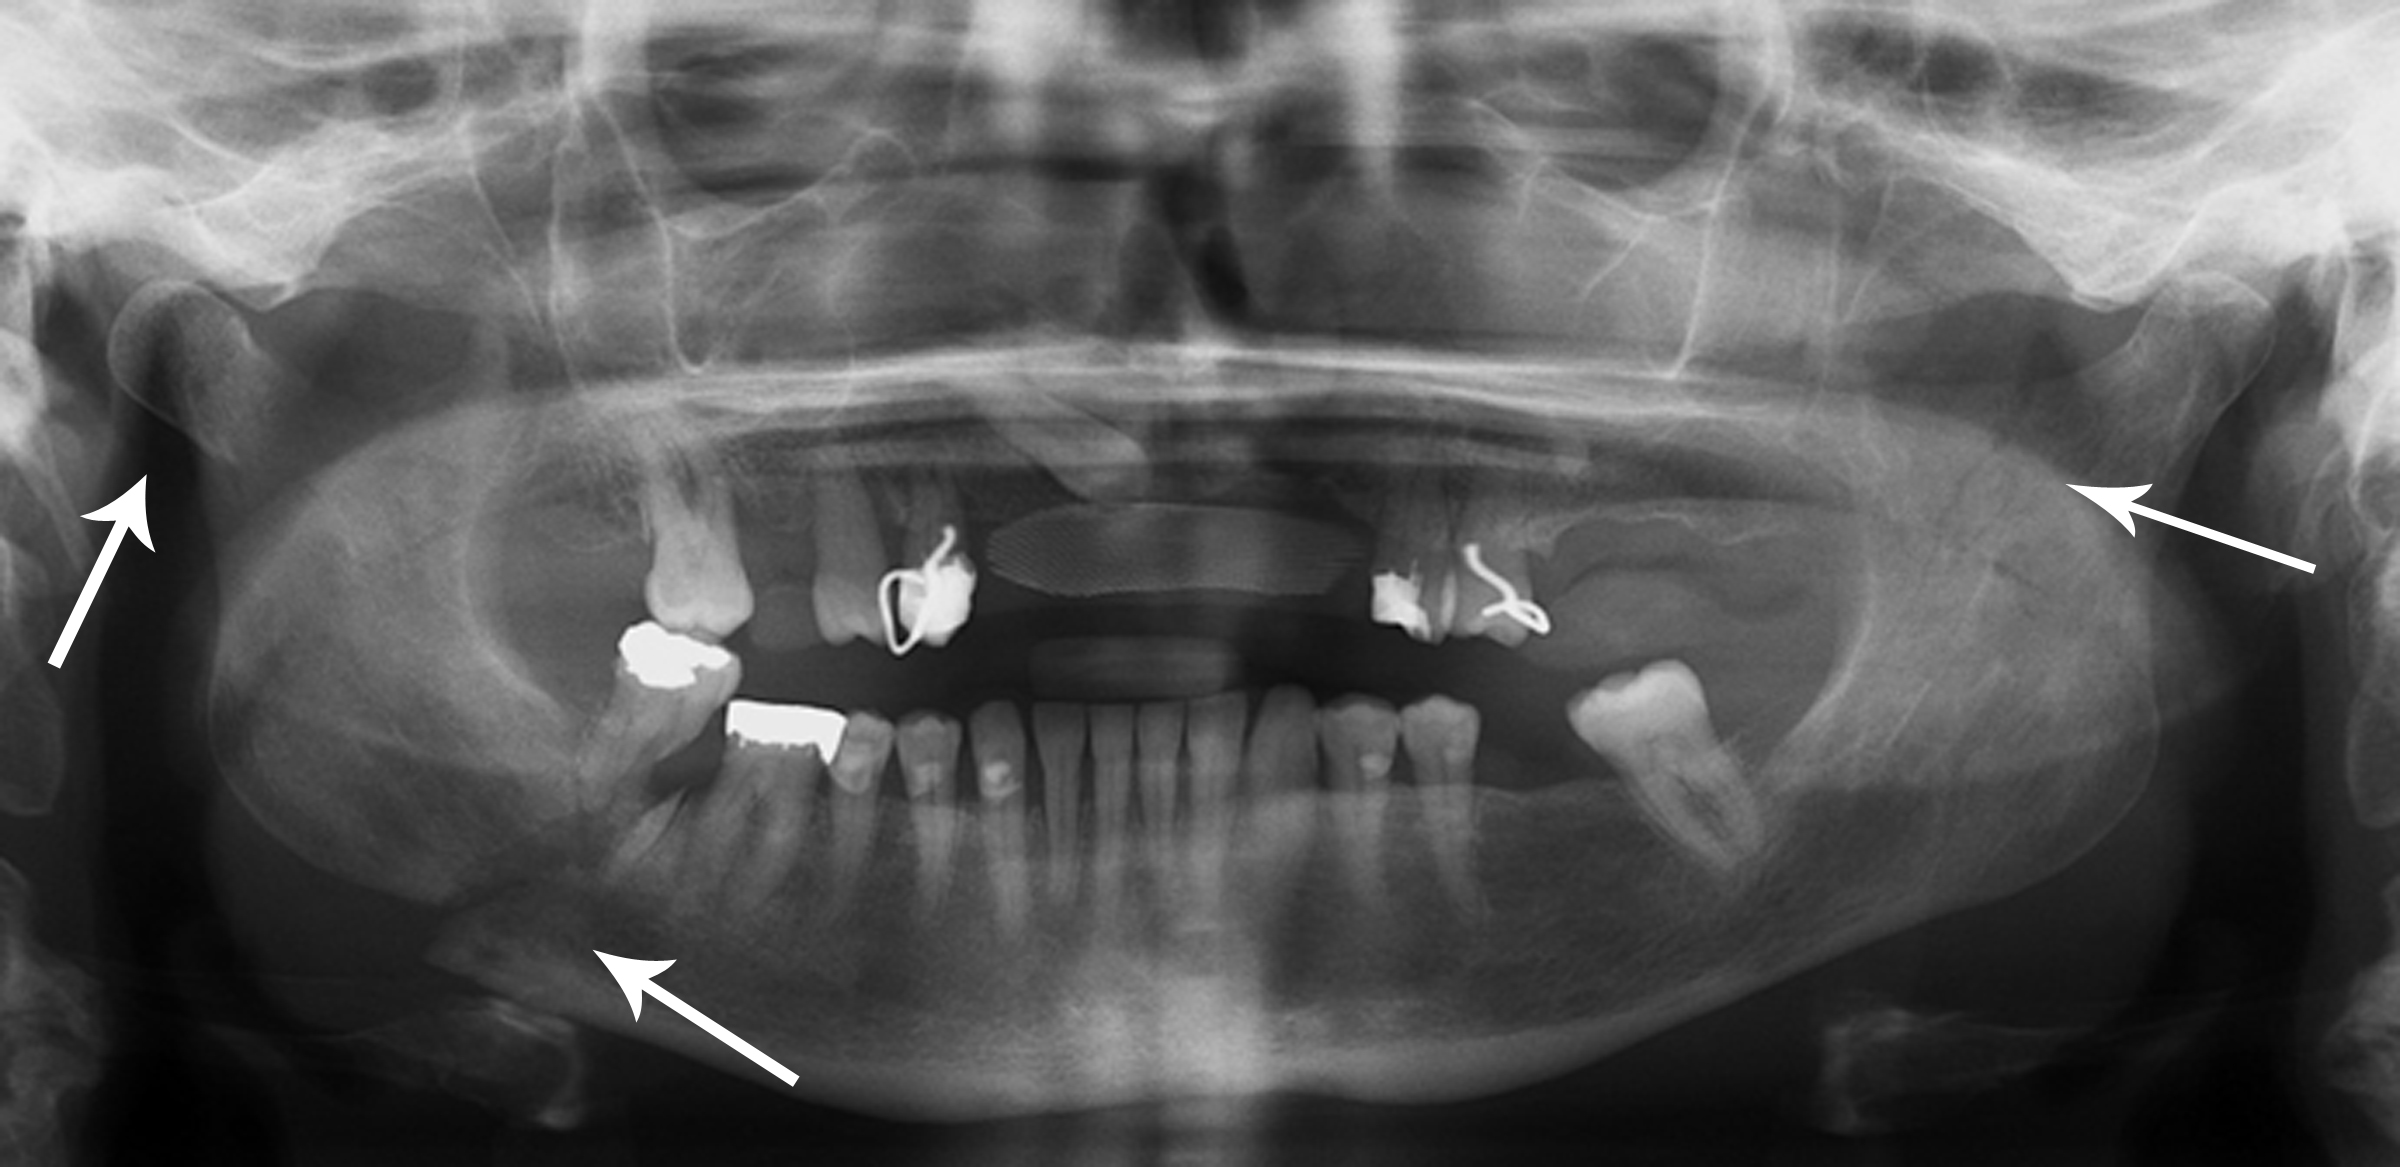
The source records right condylar and body fractures and a left coronoid fracture. Use the original arrows to orient the search, then trace each border systematically. A panoramic projection has overlap and positional limitations; a single teaching image cannot establish the complete injury pattern or its management.
Multiple mandible fractures.jpg · Coronation Dental Specialty Group · CC BY 3.0. Reproduced without alteration. Labels, arrows and circles, where present, belong to the source image.
Which clinical information is needed alongside the fracture pattern?
Airway and wider trauma assessment, occlusion, mouth opening, dental and soft-tissue injury, sensory findings and relevant patient factors, with additional investigations chosen for the clinical question.
What to expect
ED may ask OMFS to assess lacerations, dentoalveolar injuries, suspected mandibular or midface fractures and facial numbness. Major trauma and head injury require the wider trauma team pathway. The DCT’s job is often to establish an accurate baseline and raise the decisions requiring senior review.
What to know
Follow primary survey priorities and consider cervical-spine and intracranial injury. Document mechanism, timing, loss of consciousness, anticoagulants and tetanus status where relevant. Examine vision and eye movements where indicated, occlusion and bite change, mouth opening, jaw deviation, intraoral wounds, mobile segments, teeth, sensory territories and facial nerve function. Review images with the clinical question in mind; do not treat a radiology report as a substitute for examination.
A practical approach
Provide analgesia and appropriate wound care under local policy. Discuss fracture stability, open wounds, dental injury, nutrition, timing and operative options with the registrar. For a fasting patient, record last oral intake, observations, fluid balance and planned theatre coordination; arrange anaesthetic review through the local process. Document preoperative occlusion and nerve function before intervention.
Safety point
Escalate visual change, expanding haematoma, uncontrolled bleeding, airway risk, altered consciousness or other major trauma features without waiting for a routine OMFS review.
Trauma priorities and a reproducible examination
The dental injury may be the most visible problem without being the most urgent. Stabilise the patient and identify associated injuries before concentrating on the tooth.
Mechanism and initial priorities
Assess airway, cervical-spine concerns, breathing, circulation and neurological status according to the trauma pathway. Consider blood, loose teeth, displaced fragments and swelling as airway hazards. Mechanism, loss of consciousness, vomiting, visual symptoms and other injuries can change urgency and the receiving service.
Record the time and mechanism, previous occlusion, relevant medical history, tetanus / wound context and all missing teeth or fragments. An unaccounted-for tooth may have been avulsed, intruded, displaced into soft tissue, swallowed or aspirated. Do not assume it was lost at the scene without considering the mechanism and symptoms.
Mandibular landmarks
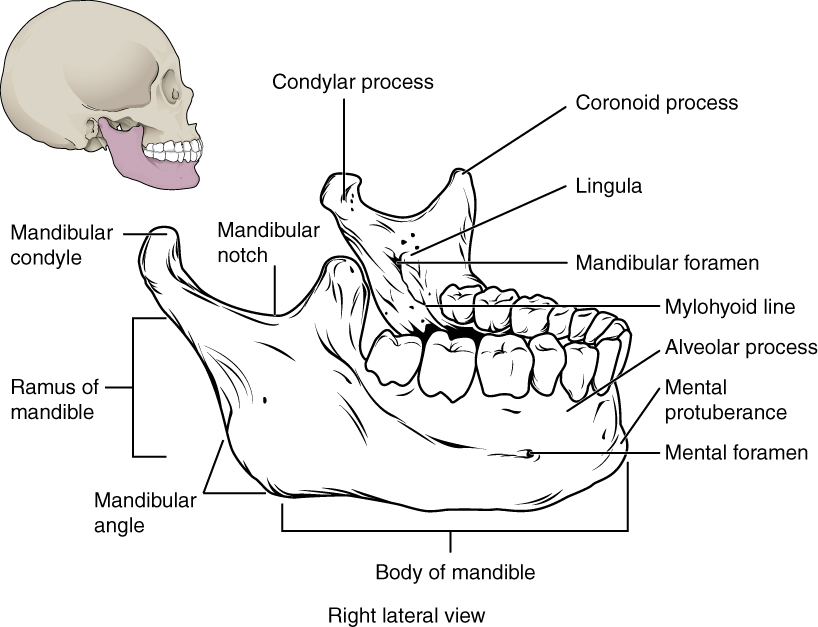
Locate the mental and mandibular foramina, lingula and mylohyoid line. The mandibular foramen, lingula and mylohyoid line are medial landmarks; this schematic brings several surfaces together. Relate the landmarks to nerve risk and fracture assessment.
Mandibular landmarks · OpenStax College · CC BY 3.0. Original image; displayed at a responsive size. Original publication.
Examination domains
| Domain | Look for | Implication |
|---|---|---|
| Occlusion | New open bite, premature contact or a step | Jaw / alveolar injury and later reduction goals. |
| Teeth / alveolus | Mobility, displacement, fracture and a group moving together | Distinguish isolated luxation from an alveolar segment fracture. |
| Function | Opening, excursions, deviation and pain | Condylar, masticator or mechanical restriction. |
| Sensation | IAN / mental or infraorbital distribution change | Baseline and possible nerve / fracture localisation. |
| Eyes / orbit | Vision, pupils, globe injury, diplopia and movement | Urgent eye / specialist assessment where abnormal. |
| Soft tissues | Depth, foreign material and nerve / duct involvement | Repair planning and associated structural injury. |
Images and documentation
Choose imaging for the injury and patient stability. Dental views can assess individual teeth and roots; cross-sectional imaging may be needed for complex facial injuries. A normal limited image does not exclude a fracture outside its field or plane. Describe the injury, not simply “facial trauma”.
Baseline photographs, occlusion and neurological findings help later comparison. Record sensibility testing but recognise its early limitations. Give the patient a follow-up schedule and symptoms that need urgent reassessment. Safeguarding and the explanation of the mechanism should be considered when the history and injury pattern are discordant.
Prioritise the patient, then classify the injury
Whole patient
- Airway and trauma assessment
- Identify head / eye / other urgent injury
- Stabilise and involve the right services
Dental / bony injury
- Record occlusion, mobility and displacement
- Use injury-appropriate imaging
- Plan reduction, stabilisation and review
Missing material
- Account for teeth and fragments
- Consider intrusion, soft-tissue or airway location
- Investigate according to mechanism and symptoms
A distinction to remember
A mobile group of teeth moving as one segment suggests an alveolar fracture rather than several unrelated loose teeth. Missing fragments must be accounted for.
Several incisors move together with a segment of bone after trauma. What changes in the diagnosis?
Reveal the reasoning
Consider an alveolar segment fracture. Assess the segment, occlusion, soft tissues and associated injuries and plan injury-specific reduction and stabilisation.
Guidance to read alongside this chapter
Mandibular, midface and orbital fracture patterns
Describe the fracture and its functional consequences. Occlusion, eye findings, nerve changes and multiple injury sites determine urgency and management.
Common patterns and clues
| Region / pattern | Useful findings | Specific concern |
|---|---|---|
| Mandibular body / angle | Malocclusion, pain, mobility, step, IAN territory change | Look for additional fractures and whether the wound communicates with the mouth. |
| Condylar injury | Preauricular pain, restricted / altered movement, occlusal change | Unilateral and bilateral patterns differ; function and growth considerations matter. |
| Zygomatic complex | Cheek flattening, infraorbital numbness, trismus or orbital symptoms | Assess orbit and vision, not just cosmetic flattening. |
| Le Fort I | Low horizontal maxillary separation pattern | Occlusion and maxillary stability. |
| Le Fort II | Pyramidal midface pattern | Nasal / infraorbital and associated injury assessment. |
| Le Fort III | Craniofacial disjunction pattern | Major trauma and associated cranial / orbital concerns. |
| Orbital wall injury | Diplopia, movement restriction, globe position change | Visual loss, globe injury or concerning entrapment features need urgent specialist assessment. |
Temporomandibular joint
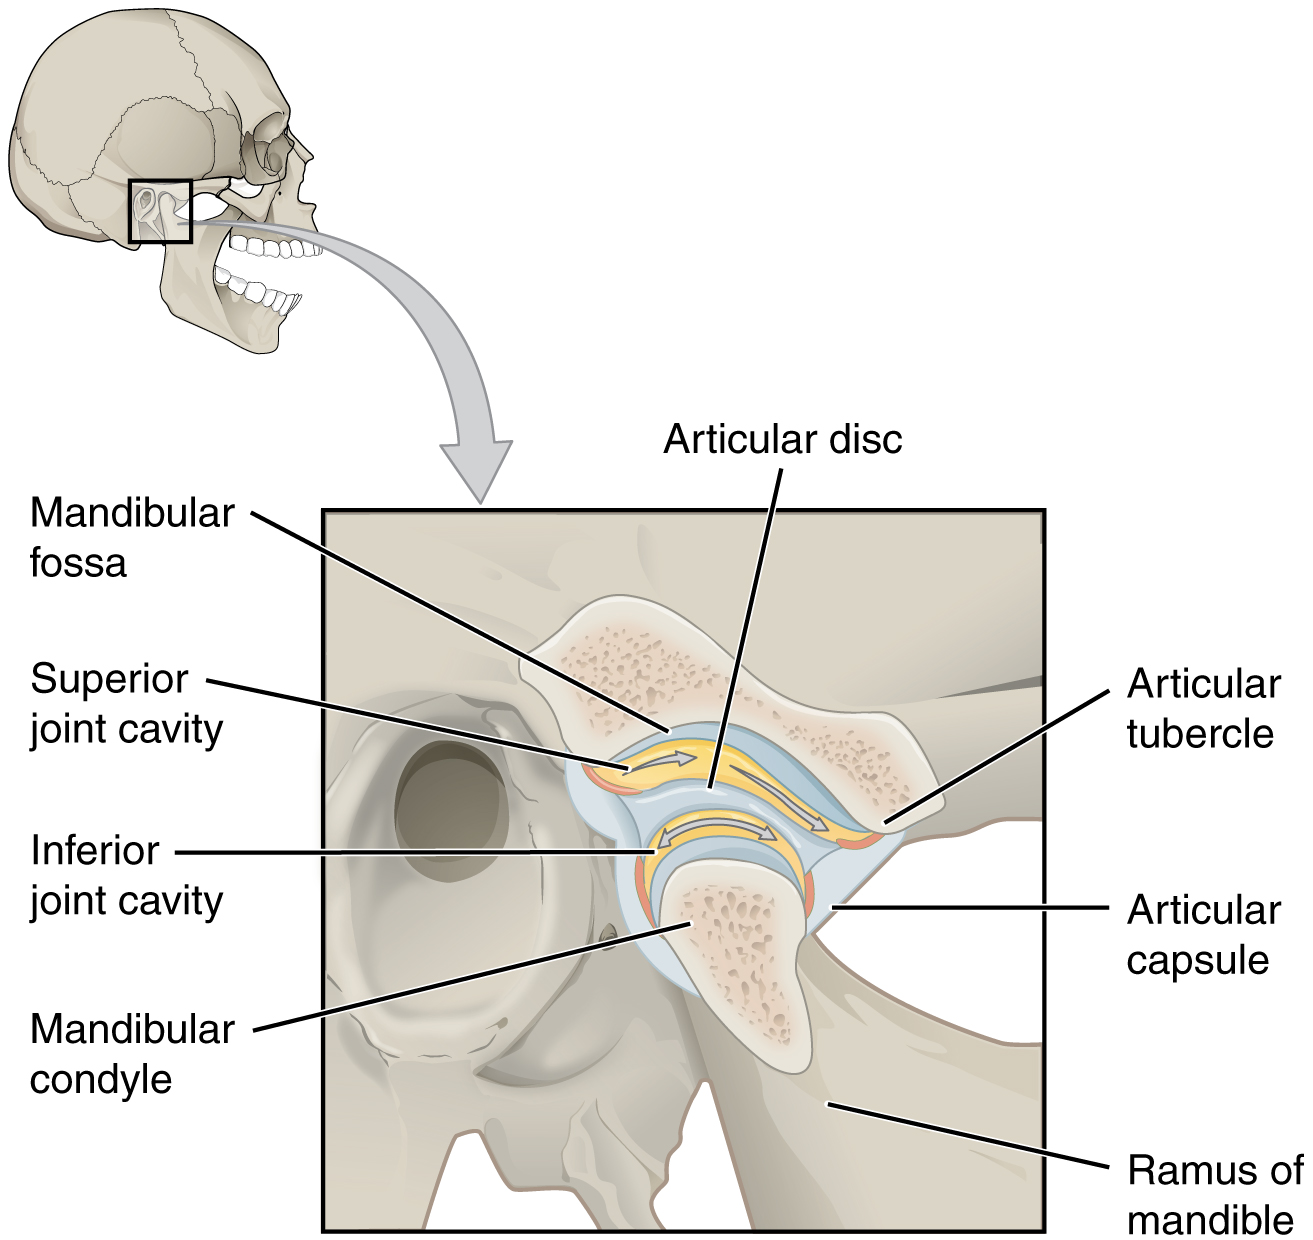
Identify the disc and the two joint compartments. Recall rotation versus translation, then connect the condyle and articular tubercle to dislocation and the disc to TMD assessment.
Temporomandibular joint · OpenStax College · CC BY 3.0. Original image; displayed at a responsive size. Original publication.
Reduction and fixation goals
Management aims to restore occlusion, stability and function while minimising morbidity. Closed and open approaches have different indications and trade-offs. Displacement, comminution, dentition, associated injury, patient factors and the ability to follow a rehabilitation plan influence the choice.
Mandibular fractures can occur at more than one site, particularly after force transmission. A condylar injury can alter bite and movement; bilateral injuries may produce an anterior open bite. Do not assume every radiographic fracture requires the same plate configuration or that every condylar fracture needs open treatment.
Stages of secondary bone healing
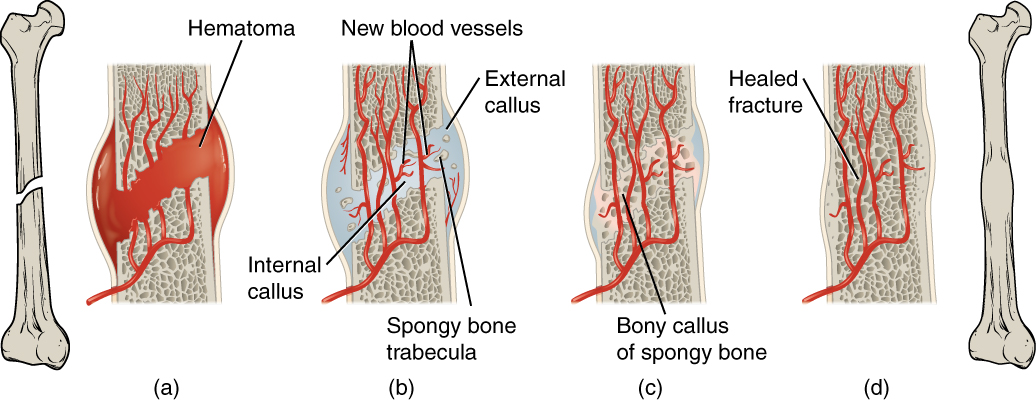
Follow haematoma, callus formation and remodelling. This general secondary-fracture-healing model uses a long bone; it is not an extraction-socket diagram or a depiction of primary healing under rigid fixation.
Stages of secondary bone healing · OpenStax College · CC BY 3.0. Original image; displayed at a responsive size. Original publication.
Healing and complications
Assess infection, stability, perfusion and the mechanical environment. Malunion alters position, while non-union represents failed union; both need cause assessment. Nerve injury, malocclusion, limited opening and hardware problems require targeted review.
Visual or neurological deterioration takes priority over routine fracture follow-up. Provide instructions on function, diet and review appropriate to the treatment. Record occlusion and sensory findings before and after intervention so that a later complaint can be compared meaningfully.
Adult mandible: labelled lateral anatomy
Locate the body, ramus, angle, condylar process, coronoid process and mental foramen. Use the labels to distinguish the two superior processes and the landmarks relevant to local anaesthesia and surgery.
HumanMandibleLeft.svg · Djexplo · CC0. None; reproduced without alteration.
Which nerve emerges through the mental foramen?
The mental nerve, a terminal branch of the inferior alveolar nerve, supplying the lower lip and chin.
Facial-fracture planning has three outcome targets
Safety
- Assess eye, airway and associated injury
- Escalate urgent functional threats
- Stabilise the whole patient
Position
- Record pre-injury / current occlusion
- Reduce and stabilise appropriately
- Check alignment and bite
Recovery
- Support the healing environment
- Restore movement and function
- Review nerve, union and hardware outcomes
A distinction to remember
Le Fort patterns classically involve pterygoid structures, but a pterygoid fracture alone does not establish a complete Le Fort injury. Orbital symptoms must not be ignored while assessing the cheek.
Why should a patient with a zygomatic injury and new visual disturbance be assessed urgently?
Reveal the reasoning
The orbit or globe may be involved, and some visual threats are time-critical. Appropriate eye and maxillofacial assessment takes priority over routine fracture scheduling.
Test your recall
What baseline findings are especially valuable before mandible treatment?
Show answer
Occlusion, mouth opening, dental and intraoral injury, sensory function and relevant imaging findings.